An Approach to a Neck Mass
Doctor, I have a lump in my neck!
Introduction
Differential Diagnosis
Lump In The Neck Algorithm
Context: Outpatients
Introduction
By far the most common cause of a neck mass is lymphadenopathy. Salivary gland pathology presents to ENT clinics, and thyroid enlargements are also common. The neck can be a site of other "benign" swellings, such as lipomas, sebaceous cysts, dermoid inclusion cyst.
The patient's age and clinical context is also obviously very important - a higher proportion of neck masses in children are reflective of congenital lesions (cystic hygroma / branchial cyst / thyroglossal cyst / haemangiomas, etc), whereas in the elderly metastatic lymphadenopathy is much more likely. In adulthood the usual differential is between TB, lymphomas, salivary gland pathology and thyroid enlargement.
Ask the patient to point towards the "lump" early in the consultation - you can easily tell from the other side of the desk if the patient has a thyroid mass or a more lateral mass, and this will guide your history taking further.
Differential Diagnosis
Common | Clues |
Lymphadenopathy | Usually short history, with mild tenderness Common site along jugular chain/ lateral zone of the neck or posterior triangle Does not move on swallowing. Usually more than one node |
Thyroid enlargement | More central location, moves visibly on swallowing, lower 1/3 of the neck just superior to the sternal notch |
Benign skin condition, ie sebaceous cyst (or lipoma/epidermoid inclusion cysts/ dermoids cysts) | Common in hairline areas of the neck Characteristic punctum and sebum on pressure Recurrent infection |
| Salivary gland enlargement | Submandibular gland is typically palpable bimanually Parotid enlargement moves the earlobe forward |
Uncommon and weird | Clues |
Cystic hygroma/ Branchial cyst Haemangioma/vascular anomaly | Commonest in childhood or early adulthood |
Carotid body tumour/ Schwannoma | Feels like an isolated LN in area of carotid bifurcation |
| Sarcoma | Hard mass within sternocleidomastoid muscle |
| Laryngocele | Bulges out on valsalva pressure |
Don't want to miss | Clues |
Malignant lymphadenopathy | Look for occult primary sites in the floor of mouth and in the thyroid |
The key clinical question is: is this a midline neck swelling (thyroid) or a lateral neck swelling (lymphadenopathy)?
Key Factors | Thyroid | Lymph Node |
Duration | Often long-standing | Increasing size |
Pain | Nil | Tender if caused by sepsis |
Predisposing factors | Family history | Reactive to URTI, dental sepsis, pharyngitis Metastatic from local or distant primary carcinomas |
Size | Variable, but can be massive | Usually 1-3cm, often more than one LN enlarged |
Consistency | Firm | Firm |
| Location | Midline lower 1/3 Moves with swallowing | Lateral Does not move on swallowing |
Lump In The Neck Algorithm
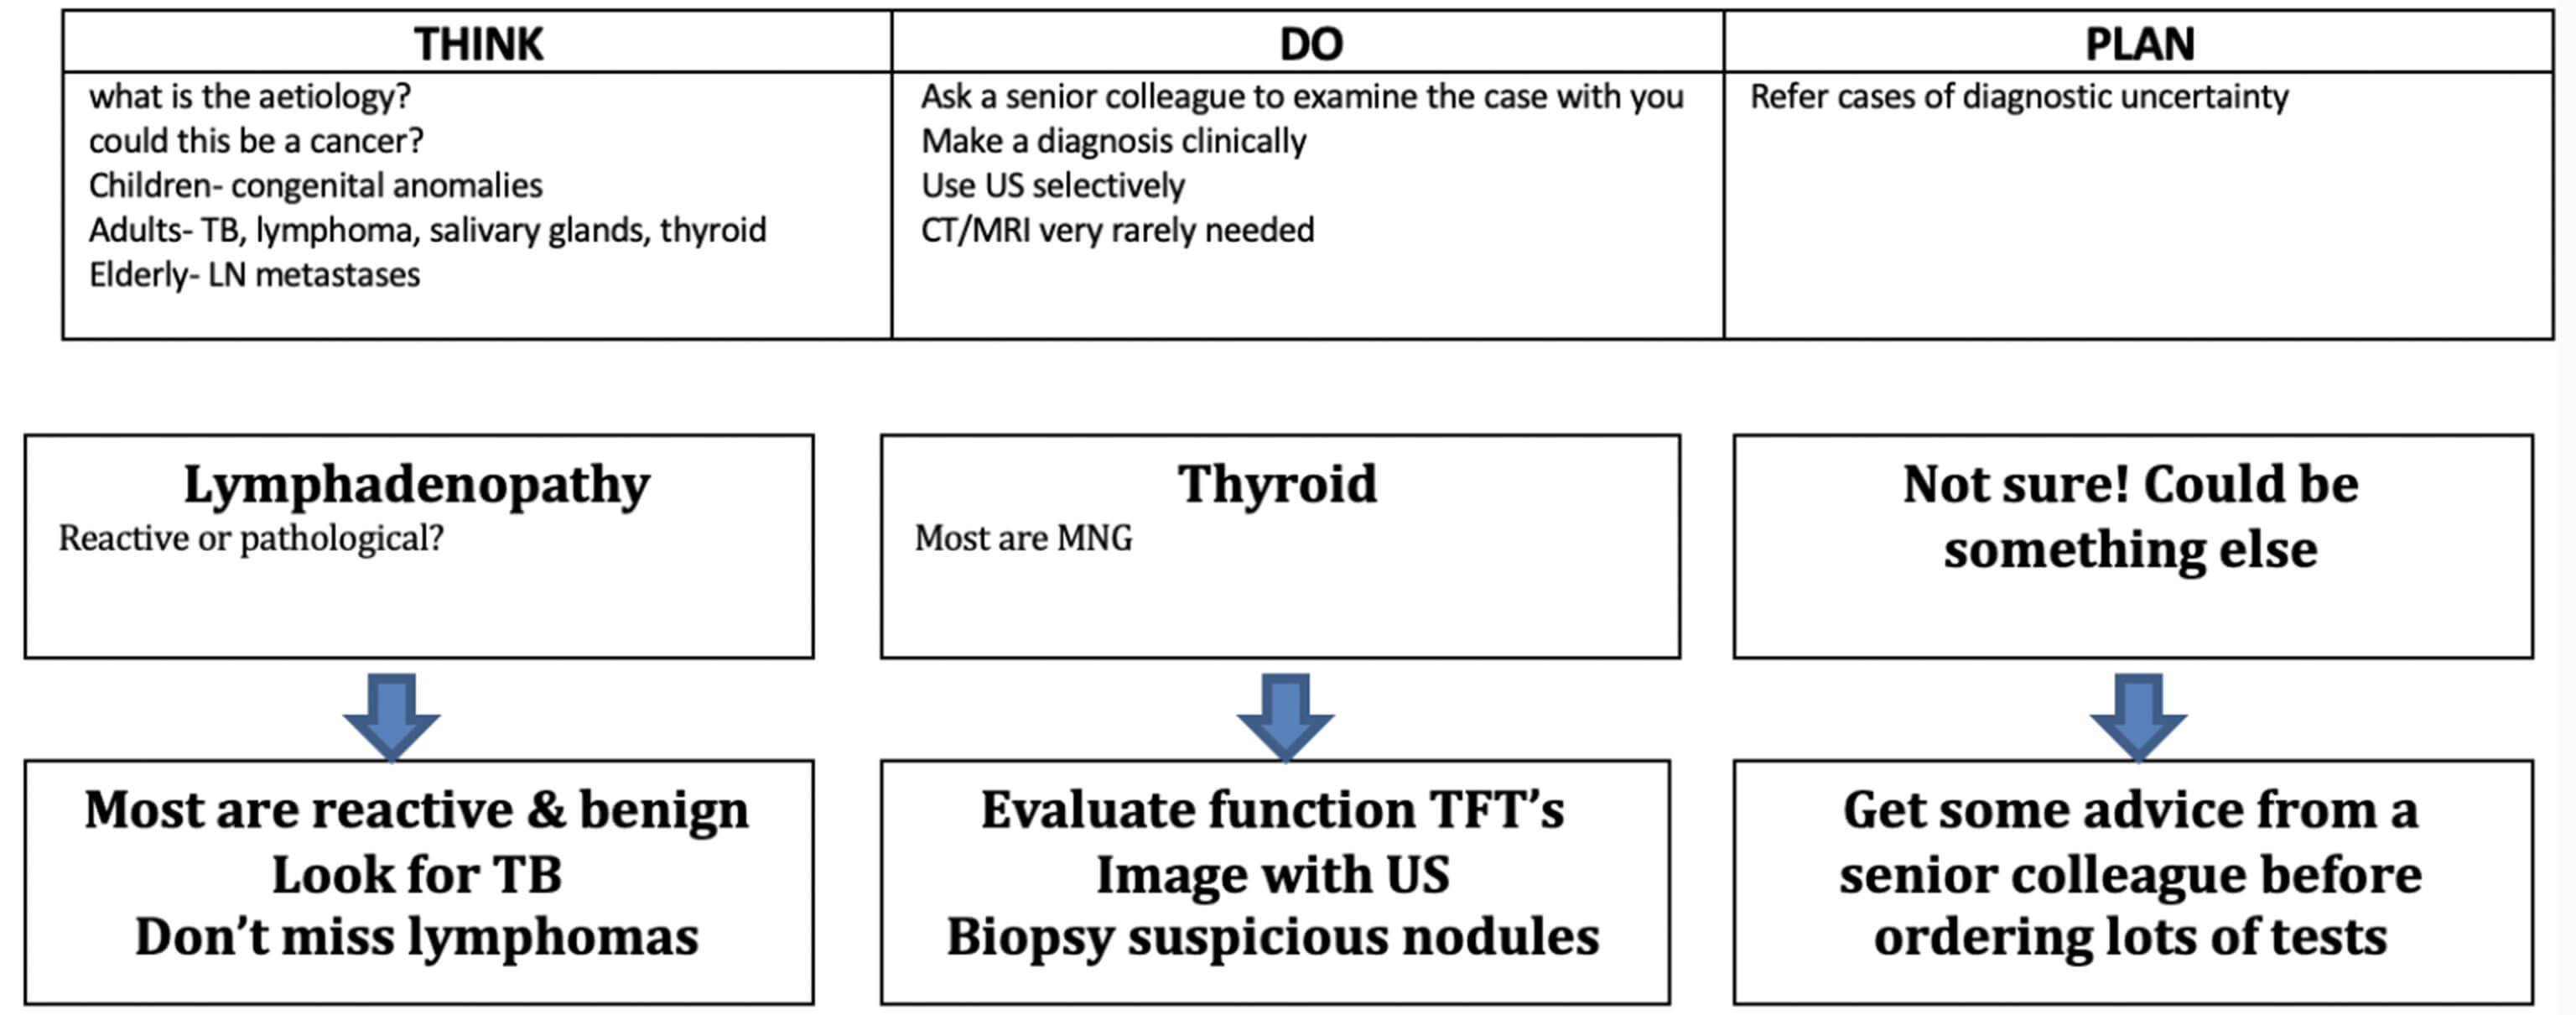
Click on the above image to enlarge