Antiretroviral Therapy
Please click on the link below to access the most up-to-date version of this guideline. The content on this page is currently being updated to align with the latest publication. Always check the version number at the bottom of the screen to confirm which version you are using. Click here to access the Adult Hospital Level Chapter 10: HIV_and_AIDS_with_supporting_NEMLC_Report_Reviews_2025-9-Versio
Please click on the link below to access the most up-to-date version of this guideline. The content on this page is currently being updated to align with the latest publication. Always check the version number at the bottom of the screen to confirm which version you are using.
Eligibility for ART
Psychosocial indicators of readiness for ART
ART regimens
ART: dosing and important adverse effects
ART drug-drug interactions
Monitoring on ART
HIV viral load monitoring schedule
Comprehensive guidelines are available for ART and the care of adults and children with HIV infection in the 2023 ART Clinical Guidelines for the Management of HIV in Adults, Pregnancy and Breastfeeding, Adolescents, Children, Infants and Neonates.i
B24
Antiretroviral therapy (ART) consists of combinations of antiretroviral medicines that are capable of suppressing HIV replication (defined as an undetectable viral load). Continued use of ART with a detectable viral load results in the development of resistance to some or all of the medicines in the regimen. High levels of adherence are essential for long-term success with ART.
The current recommended first-line ART regimen contains two nucleoside reverse transcriptase inhibitors (NRTIs) together with an integrase strand transfer inhibitor (InSTI) dolutegravir. Previously a non-nucleoside reverse transcriptase inhibitor (NNRTI), efavirenz or nevirapine, together with two NRTIs, were recommended for first-line ART. Dolutegravir is better tolerated than the NNRTIs and has a much higher barrier to the development of resistance.
Dolutegravir, together with two NRTIs, is now also recommended in a patient who has failed an NNRTI-based (formerly first-line) regimen. Previously a protease inhibitor (PI), together with two NRTIs, was recommended for secondline ART, but dolutegravir is better tolerated than PIs. Switching people established on ART to the newer dolutegravir-based ART regimens needs to be carefully done to reduce the risk of the emergence of resistance (refer to National Department of Health HIV Guidelines and “Switching existing clients to DTG-containing regimens” see Table 1: ART regimens
ELIGIBILITY FOR ART
Eligibility to start ART:
All adults with confirmed HIV infection, irrespective of CD4 count or WHO clinical stage.
LoE:Iaii
Immediate Initiation:
ART should be initiated immediately in pregnancy and during breastfeeding.
LoE:IIaiii
Timing of ART initiation:
- Where a patient is willing and ready, ART should be initiated on the same day as HIV diagnosis, except in patients with TB or cryptococcal meningitis (see Timing of ART initiation below).
- In TB co-infection, start with TB treatment first, followed by ART initiation according to CD4 count (except TB meningitis – see below):
- CD4 <50 cells/mm3: initiate ART within 2 weeks of starting TB treatment.
- CD4 ≥50 cells/mm3: defer ART until 8 weeks after starting TB treatment, which does not increase the risk of mortality and reduces the risk of deterioration due to IRIS.
LoE:Iaiv
- In patients with TB meningitis (irrespective of CD4 count), defer ART until 8 weeks after initiating TB treatment.
LoE:IIIav
- In patients with cryptococcal meningitis, defer ART until 4–6 weeks after starting antifungal treatment (earlier initiation has been shown to increase the risk of death).
LoE:IIIavi
- In patients with positive cryptococcal antigen and no evidence for meningitis on LP, there is no need to delay. ART can be started immediately.
LoE:IVbvii
PSYCHOSOCIAL INDICATORS OF READINESS FOR ART
It is essential that patients have good insight into the need for long-term therapy and high levels of adherence. Pay careful attention to adherence planning. Encourage patients to disclose their HIV status to somebody to act as a treatment supporter. If this is not possible then the patient should join a support group.
Manage depression.
Active substance abuse/alcoholism is an impediment to adherence and, if possible, should be addressed prior to initiating ART.
LoE:IIIbviii
ART REGIMENS
| INITIATING ART | |
| Treatment-naïve patients |
Individuals ≥30kg: TDF + 3TC + DTG (“TLD”) LoE:IIaix Note: DTG-based regimens are now recommended as first line ART in all women of childbearing potential. OR TDF + 3TC + DTG plus additional dose of DTG 50 mg 12 hours later. LoE:IIIbxi (Also see: HIV in pregnancy) |
| Contraindications/ intolerance to DTG | TDF + 3TC/FTC + EFV |
| Contraindications to EFV and DTG |
Start a protease inhibitor-based regimen: The LPV/r can be switched back to ATV two weeks after completion of TB therapy. |
| Contraindication to TDF - eGFR <50 mL/minute. |
If chronic hepatitis B coinfection and eGFR 30-50 ml/min: Other scenarios: LoE:IIIbxiii |
|
Contraindication to TDF/TAF and ABC intolerance/hypersensitivity |
AZT + 3TC with DTG
|
|
Note: In the unlikely scenario where there is intolerance/contraindication to all currently available NRTIs, the following alternative dual-therapy regimens may be used after consulting a specialist: - DTG + 3TC (if no resistance/intolerance to 3TC and VL <500 000 copies/mL) LoE:IIbxiv |
|
| VIROLOGICAL FAILURE | |
| Management of viraemia on TLD |
If plasma VL >50 copies/mL: - Address adherence, tolerability, medicine interactions & psychosocial factors. If plasma VL remains > 50: - Assess adherence, tolerability, medicine interactions & psychosocial factors again. |
| SWITCHING EXISTING CLIENTS TO DTG-CONTAINING REGIMENS | |
|
Patient on: - TDF/FTC/EFV - ABC/3TC/EFV (or NVP) - AZT/3TC/EFV (or NVP) - AZT/3TC/DTG - Any LPV/r- or ATV/r-containing regimen for <2 years - Any LPV/r- or ATV/r-containing regimen with latest VL <1000 copies/mL |
Switch to DTG-containing regimen regardless of VL result: TDF + 3TC + DTG (“TLD”) If contraindications to DTG or TDF, use alternative regimen as for first line above. LoE:IIbxv |
|
Patient on: - ATV/r or LPV/r regimen for >2 years and ≥2 consecutive viral loads ≥1000 copies/mL |
If adherence >80%, discuss with an HIV expert* to authorise and interpret a resistance test before switching. If adherence < 80%, switch to DTGcontaining regimen: TDF + 3TC + DTG (“TLD”) LoE:IIbxvi |
| CLIENTS WITH DTG RESISTANCE | |
| Any DTG resistance shown on genotype authorised by HIV expert |
Discuss case with an HIV expert*. The regimen will be determined by an Expert Committee based on the pattern of resistant mutations and the prior history of antiretroviral exposure. Application for 3rd line using the standard motivation formmay be required (available from TLART@health.gov.za or from https://www.righttocare.org/) |
| RIFAMPICIN-BASED TB TREATMENT | |
| Rifampicin-based TB treatment |
If on DTG: LoE:IIIbxvii If on ATV/r: Note: There is an increased risk of ALT/AST elevations and gastrointestinal disorders. LPV/r dose should be gradually titrated upward over 1-2 weeks. The LPV/r can be switched back to ATV/r two weeks after completion of TB therapy. |
ABC=Abacavir, ATV/r=Atazanavir/ritonavir, AZT=Zidovudine, 3TC=Lamivudine, DTG= Dolutegravir, EFV=Efavirenz FTC=Emtricitabine, LPV/r=Lopinavir/ritonavir, TDF=Tenofovir disoproxil fumarate TAF= Tenofovir alafenamide
Table 1: ART regimens
*For advice from an HIV expert, approach an HIV Hotline, an infectious disease specialist, or the Third Line ART committee.
HIV Hotlines:
- National HIV & TB Health Care Worker Hotline: 0800 212 506
- Right to Care Paediatric, Adolescent and Adult HIV Helpline: 082 352 6642
- KZN Paediatric Hotline: 0800 006 603
Note:
Always check hepatitis B surface antigen (HBsAg) before stopping TDF
If patient has chronic hepatitis B, stopping TDF may lead to a fatal hepatitis flare.
Continue TDF if HBsAg positive.
Currently available ARV FDC preparations on contract:
• ABC 600 mg + 3TC 300 mg
• TDF 300 mg + FTC 200 mg
• AZT 300 mg + 3TC 150 mg
• LPV 100 mg + ritonavir 25 mg
• LPV 200 mg + ritonavir 50 mg
• TDF 300 mg + FTC 200 mg + EFV 600 mg
• TDF 300mg + DTG 50 mg + 3TC 300 mg
• ATV 300mg + ritonavir 100mg
• ABC 600mg + 3TC 300mg + DTG 50mg
Source: Contract circular HP13-2022ARV http://www.health.gov.za/
RE-INITIATING ART IN PATIENTS WHO HAVE INTERRUPTED TREATMENT:
- Do VL, recommence ART regimen unless there is a clinical indication to defer ART, repeat VL at 3 months. Recommence previous regimen (unless patient would qualify for a switch to TLD anyway as per above, in which case start dolutegravir-based regimen, e.g. TLD).
- If VL does not to decrease to <1000 copies/mL at 3 months, manage as per virological failure above.
LoE:IIIbxviii
ART: DOSING AND IMPORTANT ADVERSE EFFECTS
Class: NRTI
| Generic name and Class | Usual dose | Renal adjusted dose | Important adverse drug reactions (ADRs) and timing |
| Tenofovir disoproxil fumarate (TDF) | 300 mg daily | Avoid in renal impairment (eGFR <50 mL/min) | - Acute kidney injury (rare - weeks to months). - Decline in eGFR (months to years) - Fanconi syndrome (rare – months to years) - Reduced bone mineral density (months to years). |
| Abacavir (ABC) | 600 mg daily | Dose adjustment not required | - Hypersensitivity reaction (1 to 6 weeks) fever, rash, constitutional symptoms, gastrointestinal symptoms and respiratory symptoms. |
| Zidovudine (AZT) | 300 mg 12 hourly | eGFR <10 mL/min: 300 mg daily |
- Anaemia, neutropenia (weeks to months). - Gastro-intestinal upset. - Headache. - Myopathy (rare). - Hyperlactataemia / steatohepatitis (medium risk - months). - Lipoatrophy (months to years). |
| Lamivudine (3TC) | 300 mg daily (or 150 mg 12 hourly) |
eGFR 10-30 mL/min: eGFR <10 mL/min: |
- Anaemia due to pure red cell aplasia (rare). |
| Emtricitabine (FTC) | 200 mg daily |
eGFR 15-29 mL/min: eGFR <15 mL/min: Note: FTC is not available as a singleingredient formulation. |
- Palmar hyperpigmentation. - Anaemia due to pure red cell aplasia (rare). LoE:IVbxix |
| Tenofovir alafenamide (TAF) |
25 mg daily If coformulated with FTC, avoid if eGFR <30 ml/min. If used as a single agent, avoid if eGFR <15 ml/min and not on haemodialysis. |
- Acute kidney injury |
|
Class NNRTI:
| Generic name | Usual dose | Renal adjusted dose | Important adverse drug reactions (ADRs) and timing |
| Efavirenz (EFV) | 600 mg at night | Dose adjustment not required |
- Central nervous system symptoms: vivid dreams, problems with concentration, confusion, mood disturbance, psychosis (days to weeks). - Rash (1 to 6 weeks). |
Class Boosted PI:
| Generic name | Usual dose | Renal adjusted dose | Important adverse drug reactions (ADRs) and timing |
| Lopinavir/ ritonavir (LPV/r | 400/100 mg 12 hourly OR 800/200 mg daily (only if PI-naïve) |
Dose adjustment not required |
- Gastrointestinal upset. |
| Atazanavir/ ritonavir (ATV/r) | ATV 300 mg with ritonavir 100 mg daily | Dose adjustment not required | - Unconjugated hyperbilirubinaemia (common, but benign). - Dyslipidaemia (low risk). - Hepatitis (rare - 1 to 6 weeks). - Renal stones (uncommon). |
Class InSTIs:
| Generic name | Usual dose | Renal adjusted dose | Important adverse drug reactions (ADRs) and timing |
| Dolutegravir (DTG) | 50 mg once daily | Dose adjustment not required |
- Hypersensitivity (rare, weeks) |
Table 2: Dosing and important adverse effects associated with ART
The time-onset information with respect to adverse drug reactions (ADRs) serves as an estimate. Patients may present with ADRs with the onset deviating from that indicated in the table.
LoE:IIIbxxi
ART: DRUG-DRUG INTERACTIONS
Information can be accessed from:
- https://www.hiv-druginteractionslite.org/checker
- http://www.mic.uct.ac.za/ and download the ARV/EML interaction checker.
- Package inserts.
ART INTERACTIONS WITH RIFAMPICIN AND RECOMMENDATIONS FOR ADMINISTRATION
| Class | ARV | Interaction with rifampicin | Dose of ARV with rifampicin |
| NRTI | 3TC/FTC/TDF/ AZT/ABC | No clinically significant pharmacokinetic interactions | No dose adjustment required. |
| NNRTI | EFV | Non-significant change (EFV concentrations may increase in patients who are genetic slow metabolisers of EFV and are on isoniazid which also inhibits EFV metabolism). | No dose adjustment required (600 mg at night). |
| PI | LPV/r | LPV plasma concentrations significantly decreased |
Double the dose of LPV/r to 800/200 mg 12 hourly. Adjusted dose should be continued for 2 weeks after rifampicin is stopped. |
| All other PIs | Marked reduction in PI concentrations | Do not prescribe concomitantly – replace rifampicin with rifabutin 150 mg daily (see monitoring instructions below). | |
| InSTI | DTG | Significant reduction in concentration of DTG | Dose increased to 50 mg 12 hourly.* |
Table 3: ART interactions with rifampicin and dose-adjustment recommendations
LoE:IIIbxxii
In patients on atazanavir or darunavir, or if double dose LPV/r is not tolerated, replace rifampicin with:
-
Rifabutin, oral, 150 mg daily.
- Monitor FBC monthly for anaemia and neutropenia.
- Monitor clinically for symptoms of uveitis (e.g. pain, photophobia, variable loss of vision, circumcilliary injection, a miotic pupil) – immediately stop rifabutin pending ophthalmology opinion.
LoE:IIIbxxiii
| Interacting medicine | Effect of coadministration | Recommendation |
| Preparations containing polyvalent cations (Mg2+ , Ca2+, Fe2+, Al3+, Zn2+) Antacids Sucralfate Mineral supplements |
Significant reduction in concentration of DTG | Magnesium- and aluminum-containing preparations should be taken 6 hours before or 2 hours after DTG. Calcium- and iron- containing preparations can be taken with DTG together with food. Note: Iron and calcium should be taken at least 4 hours apart from one another |
| Anticonvulsants: Carbamazepine Phenobarbital Phenytoin |
Significant reduction in concentration of DTG |
Avoid co-administration if possible. Consider valproate or lamotrigine. For carbamazepine: |
| Metformin | May increase metformin concentration |
Metformin initiation: DTG initiation: Patients with renal impairment: |
| Rifampicin | Significant reduction in concentration of DTG | Double DTG dose to 50 mg 12 hourly. |
Table 4: Drug interactions with DTG
LoE:IIIbxxiv
| Interacting medicine | Effect of coadministration | Recommendation |
| Substrates of cytochrome P450 3A4 (e.g. most statins, calcium channel blockers, most SSRIs, most benzodiazepines) | Significant increase in levels of CYP3A4 substrates | Avoid co-administration or use lower doses of CYP3A4 substrates (always consult interaction resources). |
| Anticonvulsants: Carbamazepine Phenobarbital Phenytoin |
Significant reduction in concentration of PI |
Avoid co-administration. |
| Proton pump inhibitors | Significant reduction in ATV levels | Avoid co-administration. LoE:IIIbxxv |
| Rifampicin | Significant reduction in levels of PI | Double LPV/r dose. Avoid co-administration of other PIs (replace rifampicin with rifabutin) |
Table 5: Drug interactions with boosted PIs
MONITORING ON ART
| Baseline evaluation |
- Confirm HIV positive result with second test. LoE:IVbxxv If CD4 <200 cells/mm3 : - Check cryptococcal antigen (if positive, perform LP regardless of whether symptoms are present or not).
- Screen for pregnancy or ask if planning to conceive. LoE:IIIbxxvi - Haemoglobin *TB-NAAT: TB Nucleic Acid Amplification Tests (e.g. GeneXpert Ultra MTB/RIF) LoE:IIbxxviii |
| On ART | - Monitoring schedule has been adapted to minimise the number of visits required per annum. - VL at 3 and 10 months after initiating ART and every 12 months thereafter, if virologically suppressed. Align timing with client’s scripting cycle. - CD4 at 10 months after initiating ART (align with VL). Stop CD4 count monitoring when >200 cells/mm3 and virologically suppressed. If virological or clinical failure occurs, or if client returns >90 days after missing an appointment, then a CD4 count should be done as cotrimoxazole may need to be commenced/recommenced. Repeat CD4 count every 6 months if VL remains ≥ 1000 copies/mL - If on TDF: creatinine at month 3, month 10, and every 12 months thereafter. Align with VL monitoring schedule. - If on AZT: FBC and differential count at 1 and 3 months after initiating AZT, then only if clinically indicated. - ALT if symptoms of hepatitis develop. - If on a protease inhibitor (PI): cholesterol and triglycerides at 3 months after initiating PI. If above acceptable range, do fasting cholesterol and TGs and if still above acceptable range, obtain expert advice. |
Table 6: Monitoring on ART
HIV VIRAL LOAD MONITORING SCHEDULE
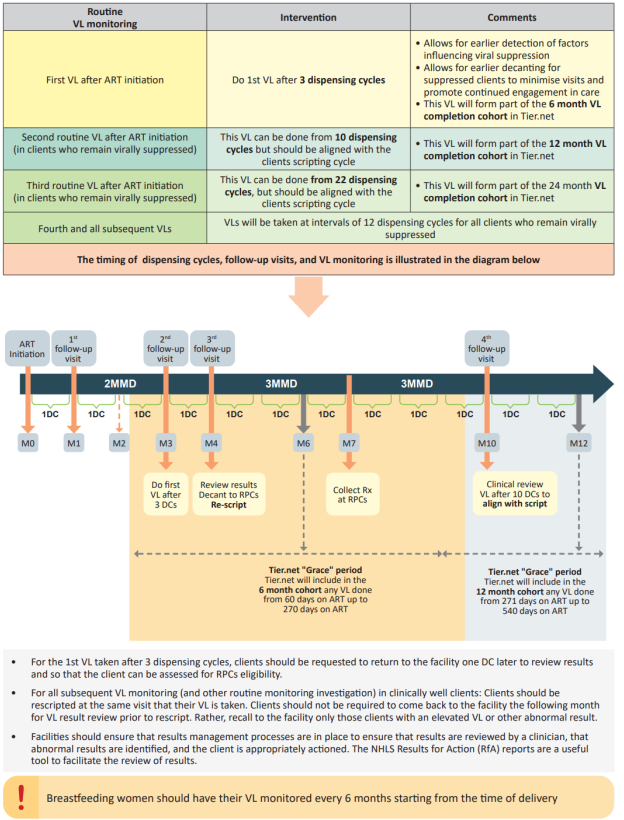
Click on image to enlarge.
DC: Dispensing cycle; MMD: Multi-month dispensing; RPCs: Repeat prescription collection strategies
Figure 1: Incorporated from the NDoH 2023 ART Clinical Guidelines for the Management of HIV in Adults, Pregnancy and Breastfeeding, Adolescents, Children, Infants and Neonates.
See 10.1.1 Management of selected antiretroviral adverse drug reactions
See 10.1.2 Immune reconstitution inflammatory syndrome (IRIS)
Standard Treatment Guidelines and Essential Medicines List for South Africa, Adult Hospital Level, 2020-2024_Version 2.1_09 December 2024
Chapter 10 HIV and AIDS_10.1 Antiretroviral Therapy