GuidelinesOther guideline
Asthma Exacerbation in Children
Guideline on the Treatment of Asthma Exacerbation in Children
Author: Assoc Prof Michael Levin
Section Editor: Dr Baljit Cheema
Acknowledgements: Prof Sharon Kling, Prof Heather Zar
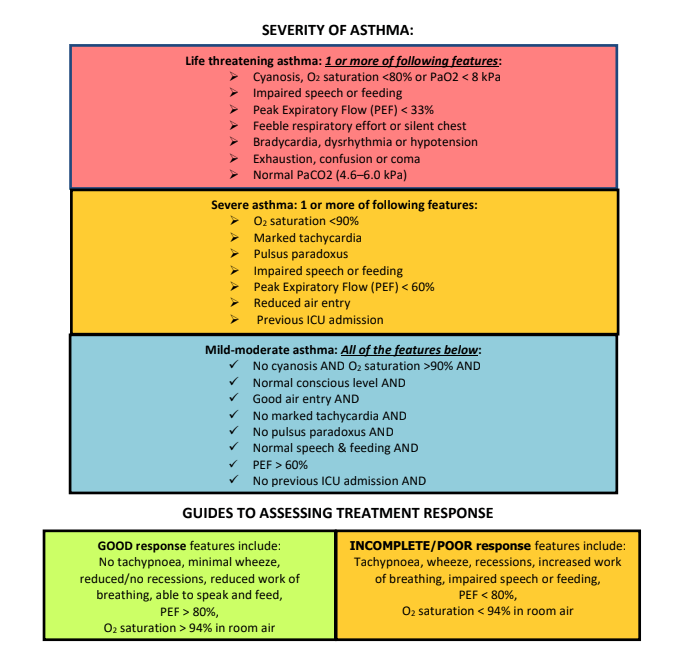
Severity Assessment
Guides to assessing response to treatment
Mild-Moderate Asthma Management
Severe Asthma Management
Additional notes on severe asthma management
Severity Assessment
| Severe asthma (box 1) = 1 or more of following features | Mild-moderate asthma (box2) All of the features below: |
| Cyanosis OR O2 saturation <94% OR Previous ICU admission OR Drowsy or confused OR Silent chest OR Marked tachycardia OR Pulsus paradoxus OR Impaired speech or feeding OR Peak Expiratory Flow (PEF) < 60% | No cyanosis AND O2 saturation >94% AND No previous ICU admission AND Normal conscious level AND Good air entry AND No marked tachycardia AND No pulsus paradoxus AND Normal speech & feeding AND PEF > 60% |
Guides to Assessing Response to Treatment
BOX 3 - GOOD response features include:
- No tachypnoea, minimal wheeze,
- reduced/no recessions, reduced work of breathing, able to speak and feed,
- PEF > 80%,
- O2 saturation > 94% in room air
BOX 4 - INCOMPLETE/POOR response features include:
- Tachypnoea, wheeze, recessions, increased work of breathing, impaired speech or feeding,
- PEF < 80%,
- O2 saturation < 94% in room air
Mild-Moderate Asthma Management
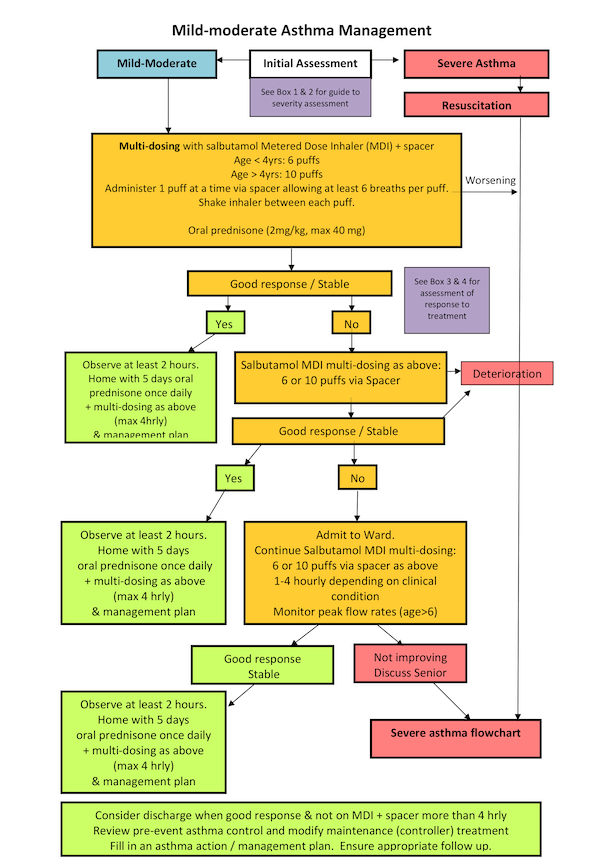
Click on image to enlarge
Severe Asthma Management
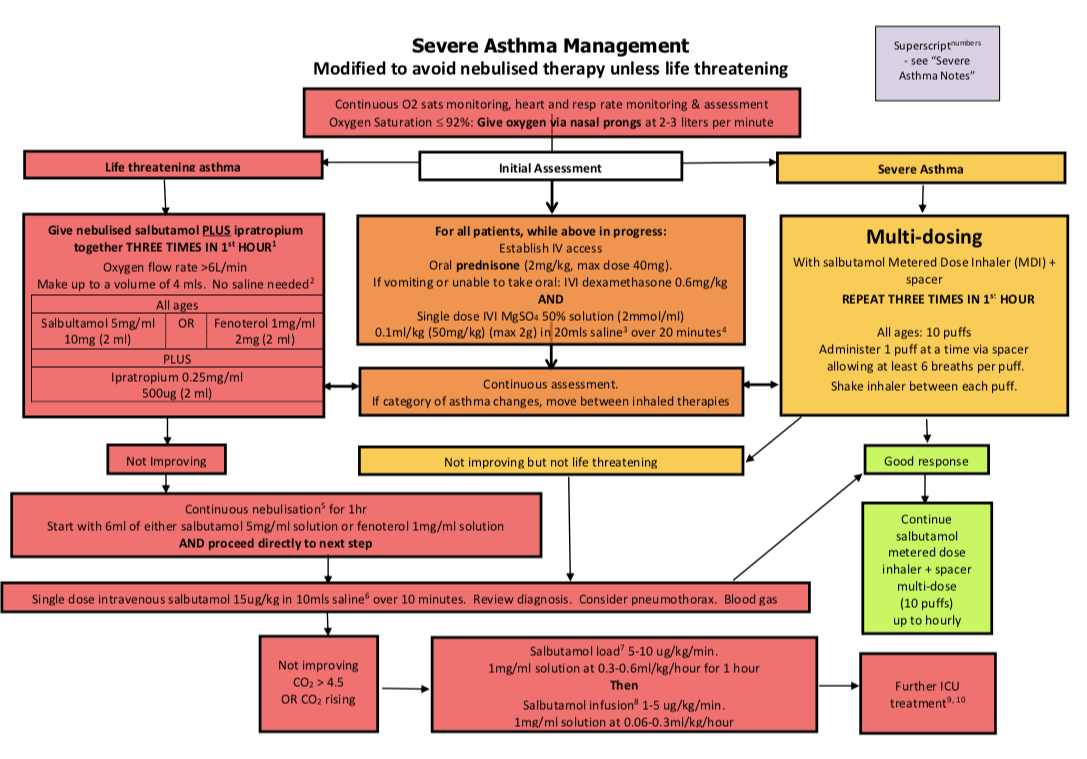
Click on image to enlarge
Additional notes on Severe Asthma Management
- If nebulization is needed this should be done in a single bed cubicle preferably with negative pressure ventilation and with staff wearing appropriate PPE for aerosol generating procedures.
- A higher dose of active nebulisation than usual is possible with minimal air entry, as very little of the medication is reaching the lungs. Use salbutamol 5mg/ml: 10 mg (2ml) (or fenoterol 1mg/ml: 2mg; 2 ml) + Ipratropium 0.25mg/ml: 500ug (2ml) without the addition of any saline.
- Make up to a total volume of 20mls and give through syringe driver at 60 ml/hr.
- If IV magnesium has good effect a continuous infusion can be continued. Use MgSO4 50% solution (2mmol/ml) at 0.06ml/kg/hour (30mg/kg/hour) to keep Mg between 1.5 and 2.3 mmol/L.
- Continuous nebulised salbutamol can be best achieved by refilling the nebuliser well using a cut feeding tube to prevent any disconnection of continuous oxygen delivery. Refill contents up to 6ml when 2ml remains.
- Make up to a total volume of 10mls and give through syringe driver at 60 ml/hr.
- Load children with salbutamol even if they have already received the smaller single dose IV salbutamol over 10 minutes.
- A patient must be closely monitored during salbutamol infusion with K+ and lactic acidosis measured 6 hourly.
- High flow oxygen and CPAP are considered high risk for aerosolization of secretions that may spread SARS-Coronavirus-2 and should be avoided if possible.
- There is no role for aminophylline outside ICU. In ICU it may occasionally have a role to prevent intubation if all other measures have failed.