GuidelinesOther guideline
Common Infusions in Paediatrics
Common infusions in paediatrics
How to mix infusions
- Decide on dose to be given and at what rate: Eg. I want to give 5mcg/kg/min at a rate of 2ml/hr.
- Therefore total dose needed in 1 hour is: 5mcg x WT x 60 (min in an hour) in 2ml
- Decide on the total amount of fluid to be mix: Eg. 50ml N/S
- Therefore the Total dose to be added in 50ml: (Total dose 1 hour) x Total volume / Rate
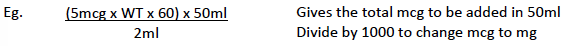
- Therefore the Total dose to be added in 50ml: (Total dose 1 hour) x Total volume / Rate
- Run most infusions at 1-5 mls per hr to avoid fluid overload
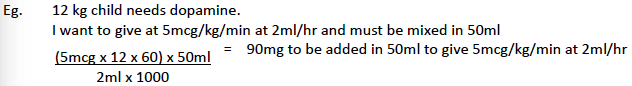
Some general principles
- Run all infusions through a separate line from maintenance.
- No boluses should be given through lines with infusions running especially adrenalin, dopamine, dobutamine and insulin.
- Syringes and lines must be clearly marked with name and concentration of infusions.
- Always check the drugs with another person and double check.
| COMMON INFUSIONS FOR NEONATES | ||||
| Drug | Dose | Mixture | Rate | Notes |
| Doxapram | Start 2.5mg/hr for 1hr then 0.3-1.5mg/hr | 24mg/kg in 24ml 5%DW | Start 2.5ml/hr for 1hr then 0.3-1.5ml/hr(1ml/hr =1mg/kg/hr ) | Note side effects |
| Glucagon | Start at 0.1mcg/kg/min (0.1-1 mcg/kg/min) | 1mg (1ml) up to 15ml in 5%DW (0.1ml/kg/hr = 0.1mcg/kg/min) | Start 0.1ml/kg/hr titrate 0.1- 1ml/kg/hr. | See neonatal hypoglycemia guidelines |
| COMMON INFUSIONS FOR PAEDIATRICS (NOT FOR NEONATES) | ||||
| Drug | Dose | Mixture | Rate | Notes |
| Adrenalin | 0.1-1.0 mcg/kg/min | 0.75mg/kg in 50 ml 5%DW or NS | Start at 1ml/hr = 0.25mcg/kg/min Titrate up in 0.5ml steps (Max 5ml/hr)* | Only give through a central line or UVC. |
| Dopamine and Dobutamine | 5-20 mcg/kg/min | 15 mg/kg in 50ml 5%DW or NS | Start at 1ml/hr = 5mcg/kg/min (Max 4ml/hr)* | Preferably give through a central line or UVC |
| Morphine | 0.1-0.2mg/kg load then 10-30mcg/kg/hr (neonates), 20-80mcg/kg/hr (children) | 1mg/kg in 50ml 5%DW | Start at 1ml/hr = 20mcg/kg/hr (Max 4ml/hr)* | Ventilated patient Start by diluting 10mg (1ml) with 9 ml saline creating a solution 1mg/ml then remix |
| Midazolam | 0.1-0.2 mg/kg bolus Inf: 0.1-4mcg/kg/min | 3mg/kg in 50ml 5%DW or NS | Start at 1ml/hr = 1mcg/kg/min (Max 4ml/hr)* | Ventilated patient |
| Clonazepam (Rivotril) | 0.05mg/kg slow bolus then 0.01-0.1mg/kg/hr | 1mg/kg in 50ml 5%DW | Start at 1ml/hr = 0.02mg/kg/hr (Max 5ml/hr) | Ventilated patient An alternative to midazolam infusion |
| Salbutamol | 5mcg/kg/hr for 1hr then 1-2 mcg/kg/hr | Use neat solution (1mg/ml) | Start at 0.3ml/kg/hr for 1 hr then 0.06-0.12ml/kg/hr | For severe asthma |
| Aminophylline | Load 6 mg/kg in NS 50 ml over 30min, then <10yrs: 1mg/kg/hr >10yrs: 0.8mg/kg/hr | 25mg/kg in 50ml 5%DW or NS | Start at 2ml/hr = 1mg/kg/hr | For severe asthma in extreme cases. If on oral preparation give less. |
| MgSO4 50% (2mmol/ml) | Asthma: 50mg/kg over 20 min (0.1ml=50mg) | Dilute in NS or 5% DW | Give over 20 min | DO NOT GIVE WITH AMINOPHYLLINE/SALBUTAMOL/ KETAMINE |
| Insulin | 0.025-0.1 U/kg/hr | Mix 2.5U/kg in 50ml 4% Albumin (Flush with 20 ml of solution) | Start at 1ml/hr = 0.05u/kg/hr and titrate. (Rate 0.5-2ml/hr) | Changed Infusion every 24hrs. MONITOR HGT HRLY. NO BOLUSES THROUGH THE LINE. Also see DKA and hyperkalaemia protocols. |
| Atropine | 0.05mg/kg every 15 min until atropinised,then maintenance infusion at 0.02-0.05mg/kg/hr | 1mg/kg up to 100ml NS | Start at 5ml/hr =0.05mg/kg/hr and titrate to clinical condition i.e lung oedema, pupil size and agitation. | Organophosphate poisoning. Wean slowly over days. |
*Note: If fluid restricted, increase concentration of mixture to decrease rate per hour