Diabetic Foot Problems
The Prevention and Treatment of Foot Problems in Diabetes
Identifying risk factors for ulceration
Understanding the pathogenesis of foot ulcer development
Prevention of foot ulceration and amputation
Education about foot-care and foot-wear
Regular examination of the feet
Nerves (Neuropathy Assessment)
Risk stratification and follow-up
Specific management of positive findings on the foot examination
Painless neuropathy with loss of protective sensation
Suspected peripheral arterial disease
(See Strength of Recommendations Taxonomy (SORT) for explanation of Grade A-C)
| SEMDSA 2017 Recommendations | |
This section should be read in conjunction with : Diabetes Foot Care Patient Checklist Diabetes Foot Screening Assessment Form Foot Abnormalities and Footwear Illustrations Neuropathy Assessment Care Pathway for People with Diabetic Foot Problems |
|
|
In people with diabetes, foot examinations by healthcare providers must be an integral component of diabetes management to identify persons at risk for ulceration and lower-extremity amputation
|
B |
|
All patients with type 2 diabetes must have their bare feet examined at least annually (more frequently in those with a high risk for ulcers) in an attempt to prevent foot ulceration
|
C |
|
The foot assessment must include a formal assessment for skin, bone and joint, nerve and vascular abnormalities (as outlined in Diabetes Foot Screening Assessment Form)
|
C |
|
Screening for peripheral neuropathy should be conducted by assessing loss of sensitivity to the 10g monofilament or loss of sensitivity to vibration at the dorsum of the great toe
|
B |
|
All patients with type 2 diabetes should receive education on good foot care practices and ulcer prevention
|
C |
|
People at high risk of foot ulceration and amputation should receive more frequent and intensive foot care education, and be referred to healthcare professionals trained in foot care management
|
B |
|
Patients with a plantar foot ulcer, critical limb ischaemia, gangrene or Charcot foot must be referred urgently for specialist care to a centre with multidisciplinary care
|
C |
|
People with diabetes should be treated, whenever possible, with intensified glycaemic control to prevent the onset and progression of neuropathy, for type 1 diabetes and for type 2 diabetes
|
A |
|
The following agents may be used alone or in combination for relief of painful peripheral neuropathy:
tricyclic antidepressants (amitriptyline) serotonin–noradrenaline reuptake inhibitors (duloxetine, venlafaxine) anticonvulsants (pregabalin, and gabapentin) |
A |
INTRODUCTION
This section highlights the morbidity and mortality associated with distal peripheral sensory diabetic neuropathy and other foot problems leading to ulceration and amputation. Ulceration and amputation are preventable complications of diabetes and the health care provider should execute the necessary measures as outlined in this guideline in order to ensure optimal patient outcomes. The annual foot assessment in the asymptomatic patient is an obligatory component of good diabetes care.
This guideline is an update of the 2012 SEMDSA guideline, and expands the practical aspects of foot-care, as well as referral strategies.
DEFINING THE PROBLEM
The term “diabetic foot” is a generic one referring to a variety of pathological conditions that can affect the foot in patients with diabetes. Foot problems are a major cause of morbidity and mortality in people with diabetes, and contribute to increased healthcare costs.1,2,3The sequence of events leading to lower-extremity amputation is well known. In people with neuropathy and/or peripheral artery disease (PAD), minor trauma to the foot leads to skin ulceration, infection and ultimately gangrene, resulting in amputation.4,5,6,7,8,9,10
The lifetime risk for foot ulceration in diabetes patients ranges from 10 to 25%,11 and foot complications are the major reason for admission to hospital for people with diabetes, accounting for approximately 20%-30% of all diabetes-related admissions in the North American population.8,9,12,13,14 Unfortunately no such data exists for the South African population. Ethnic differences noted in western countries suggest that South Asians from the Indian subcontinent have lower rates of foot ulcers and amputations, while African-Americans have higher rates than white Caucasians.
All patients with type 2 diabetes should have an annual foot assessment to determine their ulcer risk.11 A random survey of 18 community health centres in the Western Cape in 2008 found that only 11.3% of patients with diabetes had a recorded foot examination.15 Similarly, a study of 750 diabetes records at a regional hospital in KwaZulu Natal revealed that a foot examination was recorded in only 6% of patients.16 It is well known that after amputation of one limb, the prognosis for the contralateral limb is poor.17,18
What is not often appreciated though, is that the 5-year mortality following a diabetic foot ulcer or an amputation is 50% and 70% respectively, and exceeds that of many malignancies.19 Preventing the first ulcer and amputation is therefore of paramount importance.
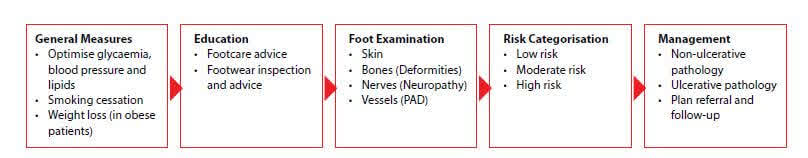
Figure I: The diabetic foot ulcer prevention plan
IDENTIFYING RISK FACTORS FOR ULCERATION 1,20,21
Characteristics that have been shown to confer high risk of
ulceration include:
- Previous ulceration
- Neuropathy
- Structural foot deformity and limited joint mobility
- Peripheral arterial disease (PAD)
- Microvascular complications (i.e. retinopathy, nephropathy). Patients on renal replacement therapy (e.g. dialysis) are at particularly high risk.11 Any foot assessment must therefore, of necessity, include an evaluation for these risk factors.
UNDERSTANDING THE PATHOGENESIS OF FOOT ULCER DEVELOPMENT 22
A crucial component of the pathogenesis of foot ulceration is most often chronic distal sensorimotor neuropathy.23 This is present, to some degree, in more than 50% of people with diabetes who are older than 60 years.24 Peripheral neuropathy must usually be profound before leading to loss of the protective sensation (LOPS) in the absence of which patients become vulnerable to trauma; the consequent vulnerability to physical and thermal trauma increases the risk of foot ulceration sevenfold. 25,26
A second causative factor in foot ulceration is excessive plantar pressure.27 This is related to both limited joint mobility (at the ankle, subtalar and first metatarsophalangeal joints), and foot deformities.28,29,30 Excessive plantar pressure is recognised when seeing callus on the plantar surface of the foot, typically over the metatarsal heads. In one study of patients with peripheral neuropathy, 28% with high plantar pressure developed a foot ulcer during a 2.5-year follow-up, compared with none with normal pressure.31
A third component is trauma, particularly when repetitive. Among 669 people observed with foot ulcers, 21% were attributed to rubbing from footwear, 11% were linked to injuries (mostly falls), 4% to cellulitis complicating tinea pedis, and 4% to self-inflicted trauma (e.g. cutting toenails).32 Those who had had a previous foot ulceration could withstand fewer cycles of stress to their feet before an ulcer recurred.33
Peripheral arterial disease (PAD) with obstruction of the arteries to the lower legs and feet also increases the risk of ulceration, and is a crucial factor in the delayed healing of foot ulcers. People with PAD may present with symptoms of ischaemia, such as claudication, rest pain, ulceration or gangrene. However, it is important to remember that people with diabetes often present without any history of these typical symptoms of ischaemia, because most of have established peripheral neuropathy as well. PAD in people with diabetes also occurs at an earlier age and progresses more rapidly.34,35
PREVENTION OF FOOT ULCERATION AND AMPUTATION
The prevention and management of foot complications can be divided into a convenient 5 step approach (See: Figure I).
A foot examination should form part of the annual review of patients with diabetes in order to detect risk factors for ulceration. This is usually performed by a healthcare professional (HCP) proficient in the assessment of feet, but community health care workers can also be trained to do this in resource poor communities.
GENERAL PREVENTION STRATEGIES
These include optimising treatment of elevated blood glucose, blood pressure (BP) and cholesterol, as well as advice on smoking cessation. This is essential to prevent microvascular and macrovascular complications of diabetes. Weight loss in obese individuals is important to reduce abnormal pressure on the feet.
EDUCATION ABOUT FOOT-CARE AND FOOT-WEAR
(See: Diabetes Foot Care Patient Checklist)
The patient and his/her caregiver should be advised by the healthcare professional on appropriate foot care. Effective foot care involves a partnership between patients, their caregivers and health professionals, and all parties should agree upon all decisions.
Extra vigilance and a routine foot care programme should be employed in the older person with poor vision and mobility, who is possibly socially deprived and lives alone. Different patient education approaches should be applied to promote improved foot care. Structured education programmes should be considered at the time of diagnosis, and should be recommended to the patients as required on an ongoing basis.
The Diabetes Foot Care Patient Checklist outlines some of the aspects that should be covered when educating patients and caregivers about self-care and the choice of footwear. This is conveniently divided into a checklist of things that they should and should not do.
In addition, the healthcare provider should inspect the patient’s footwear at every visit. The patient should wear good shoes that fit well, and the health care provider should check that the shoes:
- Are the correct length and width
- Allow enough room for the toes (high toe box)
- Have a smooth inner lining without seams
- Have a flexible sole that can bend easily and is non-slip
- Have a heel no higher than 4 cm
The use of a foot template to select the length and width of shoes should be encouraged especially in patients with diminished sensation (See: Diabetes Foot Care Patient Checklist). The patient must stand, (the foot widens substantially with weight bearing) on a piece of cardboard while someone traces the outline of the weight bearing foot. This template should fit into the selected shoe without the edges folding.
Patients with sensory loss or a history of foot ulceration should receive intensive and repetitive education on the correct fit of shoes and early signs of ill-fitting shoes. These patients should also be referred to a podiatrist or orthotist for in-shoe pressure analysis and for therapeutic shoes to prevent plantar foot ulceration or reulceration 36
REGULAR EXAMINATION OF THE FEET
(See: Diabetes Foot Screening Assessment Form )
The comprehensive foot examination must be performed at diagnosis of type 2 diabetes, and if normal, repeated annually thereafter.37 It is worth noting that in the UKPDS study, 13% of patients had neuropathy of sufficient severity to put them at risk for foot ulceration at the time of diabetes diagnosis.11 An abnormal foot examination will warrant more frequent foot examinations (See: “Risk categorisation” below).
The foot examination includes an assessment of the skin, bones, nerves and vasculature of the feet by a trained health care professional (See: Diabetes Foot Screening Assessment Form).
SKIN ASSESSMENT
(See: Foot Abnormalities and Footwear Illustrations)
It is important to look for ulcers, scars from previous ulcers, corns, calluses, fissures, fungal infections (particularly between the toes), blisters and signs of trauma. Areas of redness, and imprints of the socks or shoes on the skin may indicate ill-fitting stockings and footwear. Callus on the plantar surface over the metatarsal heads is important, as this indicates high plantar pressure. A dusky discolouration of the foot and diminished hair growth on the lower leg may indicate peripheral arterial disease (PAD).
The foot examination should also include a skin temperature assessment (with the back of hand). Increased warmth is the first indicator of inflammation in an insensate foot. It may also indicate acute Charcot neuroarthropathy, a complication of the loss of protective sensation in the foot.38,39,40 This results in bony changes, and/or fractures, subluxations and dislocations. In addition, an acute Charcot neuroarthropathy foot may be associated with erythema and swelling, with overall clinical characteristics very similar to cellulitis. It may also need to be distinguished from osteomyelitis (especially if a foot ulcer is present).41,42
Some skin abnormalities are illustrated in Foot Abnormalities and Footwear Illustrations.
BONE (DEFORMITY) ASSESSMENT
(See: Foot Abnormalities and Footwear Illustrations)
Foot deformities increase the risk of ulceration. The presence of any of the following must be documented:
- Bunion (hallux valgus)
- Hammer toes
- Arch abnormalities e.g. pes cavus, pes planus
- Limited joint mobility at the ankle or big toe
- Other bony prominences or deformities
- Features of acute or chronic Charcot neuroarthropathy
Refer to: The use of HbA1C for the Diagnosis of Type 2 Diabetes for illustrations.
NERVES (NEUROPATHY ASSESSMENT)
(See: Neuropathy Assessment)
The examiner should test for the loss of protective sensation. Ideally, this should be done using a 10 g Semmes Weinstein monofilament or a 128 Hz tuning fork. The monofilament test is the preferred test.43 Note that the monofilament test as described is aimed at detecting neuropathy, not at identifying sites at risk of ulceration. If neuropathy is detected, plantar sites should be tested (plantar surfaces of first, third and fifth metatarsal and distal plantar surface of first toe as examples). A neurothesiometer can be used in a specialised setting.
Note that the aim of clinical examination is to determine the foot at risk. Unfortunately the monofilament test has not been standardised and testing varies from 1 to 10 sites. The Canadian Guideline uses a single test on the dorsum of the great toe.44
A monofilament test with 7 or 8 correct responses, (out of 8) effectively rules out neuropathy. So any score less than this means the patient must be regarded as “At Risk” as neuropathy cannot be excluded and the patient should be managed as “At Risk”. (If one wants to be certain that there is neuropathy, one needs 5 or more incorrect responses.) The same is true for the test with the tuning fork.45
This guideline retains the agreement with the 2008 Canadian Guideline1 in identifying the possible presence of neuropathy with the tuning fork or monofilament. The 2013 Canadian Guideline uses the same test, but with a scoring system to indicate who would possibly develop neuropathy over the next four years.46 SEMDSA has not adopted this recommendation because complicated scoring systems are not easy to recall in primary care, and the tuning fork test could not predict incident neuropathy over four years.
If a monofilament or tuning fork is not available, a cotton wool ball or the fingertips can be used to test sensation by lightly touching the plantar surfaces of the feet, under the first, third and fifth toes. This is the Ipswich Touch the Toes test ( Refer to: Neuropathy Assessment fro details) and it has been validated against the monofilament. Neuropathy is defined as two or more insensitive sites out of these six.47
VASCULATURE
The dorsalis pedis (on the top of the foot) and tibialis posterior pulses (behind the medial malleolus) should be palpated. If both are absent, the likelihood for PAD increases.
The patient should be asked about pain in the calves when walking. PAD is more likely if intermittent claudication is present and both pulses are absent in the same limb. However, the atypical presentation of “ischaemia without symptoms” can manifest in patients with diabetes.
Table I. Risk categorisation system for diabetic feet.Adapted from 43 and 43
| Category |
Risk profile |
Frequency of foot examinations / level of care |
| Low risk |
People with no risk factors and no previous history of foot ulcer/ amputation |
General foot care and education; annual examination at primary care |
| Moderate risk |
People with one risk factor (neuropathy, peripheral arterial disease or foot deformity) and no previous history of foot ulcer/amputation |
Every visit Secondary level care |
| High risk |
People with two or more risk factors (neuropathy, peripheral arterial disease or foot deformity) and/or a previous history of foot ulcer/ amputation 1 |
Every visit Tertiary level care |
| Active foot problem |
People with ulceration or spreading infection or critical limb ischaemia or gangrene or suspicion of an acute Charcot arthropathy, or an unexplained hot, red, swollen foot with or without pain |
Every visit |
RISK STRATIFICATION AND FOLLOW UP
After examination of the feet, the patient’s risk stratification should be determined, and he or she should be evaluated accordingly (Table I). Care Pathway for People with Diabetic Foot Problems illustrates the comprehensive pathway of care for the different risk categories.
Patients identified as being at intermediate or high risk (category 1 and 2) for ulceration must receive intensive education focusing on prevention, and also routine treatment of non-ulcerative foot pathology by a podiatrist if possible or alternatively by a trained health care worker.
SPECIFIC MANAGEMENT OF POSITIVE FINDINGS ON THE FOOT EXAMINATION
PAINLESS NEUROPATHY WITH LOSS OF PROTECTIVE SENSATION
Note that not all patients have painful neuropathy. When there is loss of protective sensation (painless or painful neuropathy), the patient is regarded as being at risk for ulceration. Patient education, referral as needed (see below) and frequent examination (See: Table I) are crucial in order to avoid foot ulceration.
PAINFUL PERIPHERAL NEUROPATHY
A recent meta-analysis recommends tricyclic antidepressants, serotonin–noradrenaline reuptake inhibitors, pregabalin, and gabapentin as first-line neuropathic pain therapy.49
If the patient still has severe symptoms, in spite of a trial of a minimum of 14 days of any of the above, he or she should be referred to the secondary-care level.
Patients with suspected Charcot foot must be referred to a hospital where orthopaedic surgical and podiatrist services are available.
NON-ULCERATIVE FOOT PATHOLOGY
Pathology requiring podiatric or orthopaedic care.
Depending on the available referral network, all patients with severe non-ulcerative foot pathology (e.g. corns, calluses, nail deformities or hypertrophy, foot deformities) should be seen by a podiatrist and an orthotist. Severe foot deformities could be referred to an orthopaedic surgeon.
SUSPECTED PERIPHERAL ARTERIAL DISEASE
If both pedal pulses are absent in either foot, with or without symptoms of chronic ischemia, the patient should be referred to a centre where vascular surgery is available. Symptoms of ischaemia include intermittent claudication and/or rest pain. Signs of ischaemia include skin thinning, loss of hair growth, nail thickening, pallor on elevation, dependent rubor, ulceration and distal gangrene. If a patient has a foot ulcer with ANY absent foot pulse (dorsalis pedis OR tibialis posterior), they should have a full vascular assessment (Doppler studies).
In the interim, the cardiovascular risk management should be optimised as per the SEMDSA guideline.
ULCERATIVE FOOT PATHOLOGY
These patients should if at all possible be referred to a diabetes clinic or foot clinic at secondary or tertiary care level.
Please refer to the Wound Healing Association of South Africa (WHASA) consensus document of the management of the diabetic foot ulcer,50 and the International Working Group on the Diabetic Foot (IWGDF) guidance on the diagnosis and management of foot infections in persons with diabetes.51
Authors:
Paul Rheeder, Gerda Van Rensburgh, Naomi S Levitt and Aslam Amod
Editors: Joel A Dave
References
1. Canadian Diabetes Association Clinical Practice Guidelines Expert Committee. Canadian Diabetes Association 2008 clinical practice guidelines for the prevention and management of diabetes in Canada. Can J Diabetes. 2008;32(suppl 1): S143-S146.
2. American Diabetes Association: clinical practice recommendations 2004. Diabetes Care. 2004;27(Suppl 1):S63-S64.
3. Reiber GE, Boyko EJ, Smith DG. Lower extremity foot ulcers and amputations in diabetes. In: Diabetes in America. 2nd ed. Bethesda: National Diabetes Data Group, National Institutes of Health, National Institute of Diabetes and Digestive and Kidney Diseases, 1995; NIH Publication No. 95-1468 p. 409-428.
4. Eastman RC. Neuropathy in diabetes. In: Diabetes in America. 2nd ed. Bethesda: National Diabetes Data Group, National Institutes of Health, National Institute of Diabetes and Digestive and Kidney Diseases, 1995; NIH Publication No. 95-1468,p. 339-348.
5. Palumbo PJ, Melton LJ III. Peripheral vascular disease and diabetes. In: Diabetes in America. 2nd ed. Bethesda: National Diabetes Data Group, National Institutes of Health, National Institute of Diabetes and Digestive and Kidney Diseases, 1995; p. 401-408.
6. Boyko EJ, Lipsky BA. Infection and diabetes. In: Diabetes in America. 2nd ed. Bethesda: National Diabetes Data Group, National Institutes of Health, National Institute of Diabetes and Digestive and Kidney Diseases, 1995; p. 485-499.
7. Frykberg RG. Diabetic foot ulcerations. In: Frykberg RG, ed. The high risk foot in diabetes mellitus. New York: ChurchillLivingstone, 1991; p. 151-195.
8. Frykberg RG, Veves A. Diabetic foot infections. Diabetes Metab Rev. 1996;12:255-270.
9. Gibbons GW, Eliopoulos GM, Kozak GP, et al. Infection of the diabetic foot. In: Kozak GP, Campbell DR, Frykberg RG, et al, eds. Management of diabetic foot problems. Philadelphia: W B Saunders, 1995; p. 121.
10. Reiber GE, Pecoraro RE, Koepsell TD. Risk factors for amputation in patients with diabetes mellitus. A case-control study. Ann Intern Med. 1992;117:97-105.
11. Boulton AJM. The Diabetic Foot. [Updated 2016 Oct 26]. In: De Groot LJ, Chrousos G, Dungan K, et al., editors. Endotext [Internet]. South Dartmouth (MA): MDText.com, Inc.; 2000-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK409609/
12. Bild DE, Selby JV, Sinnock P, et al. Lower-extremity amputation in people with diabetes. Epidemiology and prevention. Diabetes Care. 1989;12:24-31.
13. Reiber GE. Epidemiology of the diabetic foot. In: Levin ME, O’Neal LW, Bowker JH, eds. The diabetic foot. 5th ed. St Louis: Mosby, 1993; p. 1-15.
14. Department of Health and Human Services, Centers for Disease Control and Prevention. Number (in Thousands) of Hospital Discharges with a Lower Extremity Condition (LEC) as First-Listed or Secondary Diagnosis and Diabetes as Any Listed Diagnosis, United States, 1988–2007 [cited 1 April 2016]. Available from: http://www.cdc.gov/diabetes/statistics/hosplea/diabetes_complications/fig5.htm
15. Steyn K, Levitt NS, Patel M, Gwebushe N, Lombard C, Everett K. Hypertension and diabetes: Poor care for patients at community health centres. J Endocrinol Metab Diabetes South Africa. 2008;13(2):64-70. doi:10.1080/22201009.2008.10872172.
16. Igbojiaku OJ, Harbor OC, Ross A. Compliance with diabetes guidelines at a regional hospital in KwaZulu-Natal, South Africa. African J Prim Heal Care Fam Med. 2013;5(1):1-5. doi:10.4102/phcfm.v5i1.447.
17. Ebskov B, Josephsen P. Incidence of reamputation and death after gangrene of the lower extremity. Prosthet Orthot Int. 1980;4:77-80.
18. Most RS, Sinnock P. The epidemiology of lower extremity amputations in diabetic individuals. Diabetes Care. 1983;6:87-91.
19. Armstrong, D. G., Wrobel, J. and Robbins, J. M. (2007), Guest Editorial: are diabetes-related wounds and amputations worse than cancer?. International Wound Journal, 4: 286–287.doi:10.1111/j.1742-481X.2007.00392.x
20. Boyko EJ, Ahroni JH, Stensel V, et al. A prospective study of risk factors for diabetic foot ulcer. The Seattle Diabetic Foot Study. Diabetes Care. 1999;22:1036-1042.
21. Fernando DJ, Masson EA, Veves A, et al. Relationship of limited joint mobility to abnormal foot pressures and diabetic foot ulceration. Diabetes Care. 1991;14:8-11.
22. Singh N, Armstrong DG, Lipsky BA. Preventing foot ulcers in patients with diabetes. JAMA. 2005;293:217-2
23. Pecoraro RE, Reiber GE, Burgess EM. Pathways to diabetic limb amputation: basis for prevention. Diabetes Care. 1990;13:513-521.
24. Young MJ, Boulton AJ, MacLeod AF, et al. A multicentre study of the prevalence of diabetic peripheral neuropathy in the United Kingdom hospital clinic population. Diabetologia. 1993;36:150-154.
25. Reiber GE, Vileikyte L, Boyko EJ, et al. Causal path-ways for incident lower-extremity ulcers in patients with diabetes from two settings. Diabetes Care. 1999;22:157-162.
26. Young MJ, Breddy JL, Veves A, Boulton AJ. The prediction of diabetic neuropathic foot ulceration using vibration perception thresholds: a prospective study. Diabetes Care. 1994;17:557-560.
27. Sanders LJ. Diabetes mellitus: prevention of amputation. J Am Podiatr Med Assoc. 1994;84:322-328.
28. Zimny S, Schatz H, Pfohl M. The role of limited joint mobility in diabetic patients with an at-risk foot. Diabetes Care. 2004;27:942-946.
29. Fernando DJ, Masson EA, Veves A, Boulton AJ. Relationship of limited joint mobility to abnormal foot pressures and diabetic foot ulceration. Diabetes Care.1991;14:8-11.
30. Mueller MJ, Hastings M, Commean PK, et al. Forefoot structural predictors of plantar pressures during walking in people with diabetes and peripheral neuropathy. J Biomech. 2003;36:1009-1017.
31. Veves A, Murray HJ, Young MJ, Boulton AJ. The risk of foot ulceration in diabetic patients with high foot pressure: a prospective study. Diabetologia. 1992;35:660-663.
32. Macfarlane RM, Jeffcoate WJ. Factors contributing to the presentation of diabetic foot ulcers. Diabet Med. 1997;14:867-870.
33. Maluf KS, Mueller MJ. Novel Award 2002: Comparison of physical activity and cumulative plantar tissue stress among subjects with and without diabetes mellitus and a history of recurrent plantar ulcers. Clin Biomech (Bristol, Avon).2003;18:567-575.
34. Jude EB. Intermittent claudication in the patient with diabetes. Br J Diabetes Vasc Dis. 2004;4:238-242.
35. Jude EB, Ojibo SO, Chalmers N, Boulton AJ. Peripheral arterial disease in diabetic and nondiabetic patients: a comparison of severity and outcome. Diabetes Care. 2001;24:1433-1437.
36. Sicco A. Bus S.A,R Haspels R,Busch-Westbroek T.E. Evaluation and Optimization of Therapeutic Footwear for Neuropathic Diabetic Foot Patients Using In-Shoe Plantar Pressure Analysis . Diabetes Care. 2011: 34:1595-1600.
37. Boulton AJ, Armstrong DG, Albert SF, et al, American Diabetes Association, American Association of Clinical Endocrinologists. Comprehensive foot examination and risk assessment: a report of the task force of the foot care interest group of the American Diabetes Association, with endorsement by the American Association of Clinical Endocrinologists. Diabetes Care 2008;31:1679e85.
38. Lavery LA, Higgins KR, Lanctot DR, et al. Preventing diabetic foot ulcer recurrence in high-risk patients: use of temperature monitoring as a self-assessment tool. Diabetes Care. 2007;30:14-20.
39. Armstrong DG, Lavery LA. Monitoring healing of acute Charcot’s arthropathy with infrared dermal thermometry. J Rehabil Res Dev. 1997;34:317-321.
40. Yu GV, Hudson JR. Evaluation and treatment of stage 0 Charcot’s neuroarthropathy of the foot and ankle. J Am Podiatr Med Assoc. 2002;92:210-220.
41. Frykberg RG, Zgonis T, Armstrong DG, et al; American College of Foot and Ankle Surgeons. Diabetic foot disorders. A clinical practical guideline (2006 revision). J Foot Ankle Surg. 2006;45(5 suppl):S1-S66.
42. Ledermann HP, Morrison WB. Differential diagnosis of pedalosteomyelitis and diabetic neuroarthropathy: MR imaging. Semin Musculoskelet Radiol. 2005;9:272-283.
43. National Institute for Health and Care Excellence (NICE). Diabetic foot problems: prevention and management. NICE guideline [NG19] Published date: August 2015 Last updated: January 2016 https://www.nice.org.uk/guidance/ng19 [Accessed 30 July 2016]
44. Canadian Diabetes Association Clinical Practice Guidelines Expert Committee, Bril V, Perkins B, Toth C. Neuropathy. Can J Diabetes. 2013 Apr;37 Suppl 1:S142-4.doi:10.1016/j.jcjd.2013.01.039.
45. Perkins BA, Olaleye D, Zinman B, et al. Simple screening tests for peripheral neuropathy in the diabetes clinic. Diabetes Care. 2001;24:250-256.
46. Perkins BA, Orszag A, Ngo M, Ng E, New P, Bril V. Prediction of incident diabetic neuropathy using the monofilament examination: a 4- year prospective study. Diabetes Care. 2010;33:1549-54.
47. Rayman G, Vas PR, Baker N, et al. The Ipswich touch test: a simple and novel method to identify inpatients with diabetes at risk of foot ulceration. Diabetes Care. 2011;34(7):1517-1518.
48. Avaialble from https://www.nhmrc.gov.au/_files_nhmrc/publications/attachments/diabetes_foot_full_guideline_23062011.pdf (cited on 22 Feb 2016)
49. Finnerup NB, Attal N, Haroutounian S, McNicol E, Baron R, Dworkin RH, Gilron I, Haanpää M et al. Pharmacotherapy for neuropathic pain in adults: A systematic review and meta-analysis. Lancet Neurol 2015 Feb; 14:162-173.
50. Available from http://www.woundhealingsa.co.za/index.php/WHSA/article/view/185, (cited on 24 February 2016)
51. Lipsky BA, Aragón-Sánchez J, Diggle M, Embil J, Kono S, Lavery L, Senneville É, Urbančič-Rovan V, Van Asten S; International Working Group on the Diabetic Foot (IWGDF). IWGDF guidance on the diagnosis and management of foot infections in persons with diabetes. Diabetes Metab Res Rev. 2016 Jan;32 Suppl 1:45-74.
52. Crawford F, Inkster M, Kleijnen J, Fahey T. Predicting foot ulcers in patients with diabetes: a systematic review and meta-analysis. QJM 2007;100:65e86.
53. Feng Y, Schlösser FJ, Bauer E, Sumpio BE. The Semmes Weinstein monofilament examination is a significant predictor of the risk of foot ulceration and amputation in patients with diabetes mellitus. J Vasc Surg 2011;53:220e6.
54. Arad Y, Fonseca V, Peters A, Vinik A. Beyond the monofilament for the insensate diabetic foot. Diabetes Care 2011;34:1041e6.
55. Valk GD, Kriegsman DM, Assendelft WJ. Patient education for preventing diabetic foot ulceration: a Systematic review. Endocrinol Metab Clin North Am 2002;31:633e58.
56. McCabe CJ, Stevenson RC, Dolan AM. Evaluation of a diabetic foot screening andprotection programme. Diabet Med 1998;15:80e4.
57. Canadian Diabetes Association Clinical Practice Guidelines Expert Committee, Bowering K, Embil JM. Foot Care. Can J Diabetes. 2013;37 Suppl 1:S145-9.
58. The Diabetes Control and Complications Trial Research Group. The effect of intensive treatment of diabetes on the development and progression of longterm complications in insulin-dependent diabetes mellitus. N Engl J Med 1993;329:977e86.
59. Reichard P, Berglund B, Britz A, et al. Intensified conventional insulin treatment retards the microvascular complications of insulin-dependent diabetes mellitus(IDDM): the Stockholm Diabetes Intervention Study (SDIS) after 5 years. J Intern Med 1991;230:101e8.
60. UK Prospective Diabetes Study (UKPDS) Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). Lancet 1998;352:837e53.
61. Canadian Diabetes Association Clinical Practice Guidelines Expert Committee,
Bril V, Perkins B, Toth C. Neuropathy. Can J Diabetes. 2013;37 Suppl 1:S142-4.