Diabetic Ketoacidosis in Children: Tygerberg Children's Hospital Protocol
Diabetic Ketoacidosis in Children
Bloods and other tests at admission
Make the diagnosis
- Hyperglycaemia (BG > 11 mmol/l)
- Heavy glycosuria (>55mmol/l)
- Blood BOHB >0,6mmol/l or ketonuria
- pH < 7.3
- SB < 15 mmol/l
Clinical
- Polyuria
- polypsia
- ≥5% dehydration
- ± Kussmaul respiration
- ±Vomiting
- ±Abdominal pain
- ± Drowsy
Beware: Euglycaemic DKA
Hyperglycaemic Hyperosmolar-State (HHS):
- BG > 33,3mmol/L
- Ph>7,3
- SB > 15mmol/L
- Absent / Mild BOHB (1mmol/L), Small Ketonuria
- Effective Osmolaility >320 Mmol/L
- Stupor / Coma.
Assess Severity
| Mild | Moderate | Severe | |
| Shock | NO | NO | YES |
| Dehydration | < 5% | ≤ 10% | > 10% |
| LOC | Alert | Drowsy | Depressed |
| Acidosis | pH <7,3 SB <15 | pH < 7,2 SB <10 | pH < 7.1 SB < 5 |
Shock
Tachycardia, ± hypotension, poor pulse volume, delayed capillary refill time
Beware:
Stress response causes tachycardia and hypertension or a SBP in upper normal range.
Refer to ICU
- Requiring ≥40ml/kg of NS to correct shock.
- Anuria – persistent or redeveloping after shock was corrected
- Depressed LOC not associated with initial shock.
Consider ICU admission
- pH <7,1
- Elevated urea
- Children under 2 years.
- Hyperventilate to blow off CO2
Calculate:
Effective Osmolality =2(Na) + BG m0sm/kg (N=280-295)
Anion gap = Na-(Cl+HCO3) (N=8-16)
Bloods and other tests at admission
- Weight: If unknown, measure length & estimate weight from height chart
- Laboratory glucose
- pH, pCO2, SB, base deficit (venous blood gas is acceptable)
- Na, K, CI, U, Cr, (Ca, Mg, Pi and Alb)
- Infection screen if indicated (but no acute phase reactants during DKA)
FLUID THERAPY
- Resuscitation
- Treat shock first
- Stay with the child until shock is corrected
- Aim: N SBP for age and a significant drop (of at least 10%) in HR.
- Proceed to step 2-4 when hypovolaemia corrected.
- Oxygen.
- Start insulin only if shock has been corrected (early use is associated with cerebral oedema)
- Hypotension: NS 0,9% 20ml/kg over 10-30 min
- Compensated shock: NS 0,9% 10ml/kg over 10-30 min
- Reassess. Repeat until aim achieved.
- Consider nasogastric tube (vomiting, depressed LOC)
- Treat shock first
- Maintenance (over 24hrs)
- 0-2 yrs: 80ml/kg/24 hrs
- 3-5 yrs: 70ml/kg/24 hrs
- 6-9 yrs: 60ml/kg/24 hrs
- 10-14 yrs: 50ml/kg/24 hrs
- >15 yrs: 30ml/kg/24 hrs
- Rehydration (over 48 hours)
- 5% dehydrated: 50ml/kg/48hrs
- 10% dehydrated: 100ml/kg/48hrs
- Review at least 6 hourly.
- Ongoing losses
- Replace urine loss in excess of 2ml/kg/hour = urine output in ml/kg/hr – 2 ml/kg/hr
Aims for Fluids for rehydration, maintenance and ongoing losses:
- Effective osmolality at 4 hrs should be the same or up to 4mOsm/kg higher than baseline (an early drop may be associated with cerebral oedema).
- Rehydrate over 48 hours
- NS (0,9%) for first 4-6 hours
- ½ NS (0,45%) after 6 hours (excessive NS has been associated with hyperchloraemic acidosis) unless attenuated rise/drop in serum Na.
- ½ NS (0.45%) saline or NS (0,9%) until BG <15 mmol/l.
- Add 5% dextrose to NS/½ NS (whatever is applicable) to maintain BG between 8 – 12 mmol/l or if BG drops by >5mmol/l/hr (5%DW/NS = rehydration fluid). Should the BG rise again above 15 mmol/l, you may increase the insulin infusion temporarily by 25% (i.e. increase to 2,5ml/hr – see below)
- Change to 10% dextrose if BG <8 mmol/l and ketonaemia persists.
- The insulin infusion rate should only be decreased if the BG remains below 8 mmol/l despite glucose supplementation.
Insulin – soluble (regular) insulin (Actrapid)
- Infusion – 0.1 units/kg/hour (consider 0.05 units/kg/hour in child under 5years)
- Aim: BG should drop at a rate not faster than 2-5 mmol/l/hr
By syringe driver:
- 0.1units x mass = units/kg/hr
- Units/kg/hr x 6hours = units/kg/6hours
- Add units/kg/6hours to 12ml normal saline
- Prime tubing, Run at 2 ml/hour
Alternatives for referring doctor
NB – Insulin should only be started after the resuscitation is complete. If the transfer to TBH is quick, it is not essential to give any insulin at all – please discuss this with the receiving doctor first.
- 25 units in 100ml normal saline, run at (0.4 x weight in kg) ml/hr, remember to prime tubing. This still requires an infusion pump.
- 50 units in 500ml normal saline (1 unit / 10ml), infuse at 0.1 units/kg/hour, change bag every 24 hours.
- Hourly subcut/im insulin 0.1u/kg – this will only work if the patient is not shocked.
- Never give insulin during a transfer. If the transfer is going to be lengthy, consider a bolus dose of soluble insulin 0.1unit/kg iv prior to transfer.
Do not decrease or stop the insulin infusion below 0.05 units/kg/hour until the child is clinically well, and blood BOHB <0,6 mmol/l or ketonuria has resolved, but ensure that the child’s BG is maintained between 8-12 mmol/l as described above.
Potassium
Start as soon as resuscitation is complete
- and The child is passing urine
- The ECG does not show elevated T-waves OR
- serum potassium is 4.5 mmol/l or upper limit for lab
- Give 40mmol KCl/l in iv fluids (40mmol KCl = 20 ml of 15% KCl)
- Increase KCI supplementation if necessary – maximum IV rate 0,5mmol/kg/hr
- Give potassium phosphate only if serum phosphate very low and clinically weak. Usually KCl and KPO4 is added in equal volumes to iv fluids for 6-12 hours of therapy ONLY – monitor serum Ca.
- Give 40mmol KCl/l in iv fluids (40mmol KCl = 20 ml of 15% KCl)
Calculations:
- 1 ml 15% KCl = 2 mmol K+; 1 gram KCl = 13 mmol K+
- 1ml K2PO4 = 2 mmol K+ and 1.4 mmol PO4
Sodium
- If the sodium does not increase, or falls, use normal (0,9%) saline. Beware of cerebral oedema.
- If the initial sodium is >150 mmol/l, use half-normal (0.45%) saline and rehydrate more slowly (>48hrs)
Hyperglycaemia may cause false hyponatraemia:
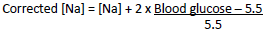
Persistent acidosis results from:
- Inadequate resuscitation.
- Inadequate insulin.
- Sepsis
- Excessive NS admin (hyperchloraemic acidosis)
Sodium bicarbonate therapy
- Contraindicated: Associated with cerebral oedema
- Consult paed endocrinologist on call first if possible, otherwise ICU consultant on call.
- NaBic should not be needed if the patient is not in ICU
- Do not use NaBic in the initial resuscitation.
- Correct by 25% over 4 hours (not a bolus)
- mmol bicarbonate = (base deficit x 0.3 x body weight) ÷ 4
- Stop when pH 7.15 or standard bicarbonate > 8 mmol/l
Oral fluids during recovery
- With severe DKA – oral sips / ice only
- Start oral fluids only after substantial clinical improvement, and when there is no vomiting.
- Remember to subtract from iv input.
Antibiotics – if indicated clinically. Remember usually DKA is precipitated by insulin omission..
Manage stomach and bladder – NG drainage and bladder catheterisation as needed.
Complications
- Cerebral oedema – as the patient is improving. Signs: Headache
- Change in vital signs: ↓HR, ↑BP, ↓O2 saturation, fever Change in CNS signs: ↓LOC, irritability, restlessness, incontinence. CNS signs: cranial n palsies, posturing, seizures (convulsions, papilloedema and respiratory arrest occur late and have a very poor prognosis)
- Treatment:
- Exclude hypoglycaemia
- Mannitol 1g/kg iv immediately, over 20 minutes
- Halve iv fluid rate
- Elevate head
- ICU
- Mannitol 0.25g/kg/hour as infusion or boluses 4-6hrly
- CT head only when stable
- Technical – tissued drips, blocked lines, leaks, uncontrolled infusion etc.
- Recurrence ketoacidosis – from stopping insulin too early.
- Hypoglycaemia
- Hypokalaemia or hyperkalaemia
- Aspiration pneumonia
Mild DKA
- Drink adequate fluids (maintenance + up to 5% rehydration)
- Give extra Actrapid 0,05u/kg if BG >11 mmol/l and 0,1u/kg if BG ≥15 mmol/l
- Monitor BG and blood BOHB/urine ketones 2-4 hourly depending on severity.
- Repeat Actrapid 2-4hrly until ketone free.
Changing to subcutaneous insulin
- Plan to switch at a mealtime – breakfast is most convenient!
- Work out insulin requirements (start at 0.6U/kg/day or less – 2/3 before breakfast, of which 1/3 actrapid, 2/3 protaphane; remaining 1/3 divided into 1/3 and 2/3 or ½ and ½ , actrapid 1/3 0r ½ before supper, protaphane 2/3 or ½ at 21h00)
- Give first subcutaneous dose of insulin.
- Meal 30 minutes thereafter.
- Stop insulin infusion +/- 60 minutes after subcut. Injection.
- Diabetic diet includes breakfast, snack, lunch, snack, supper, snack!
- Insulin requirements frequently remain high for a few days and then drop again – consider extra doses of actrapid (0.05 – 0.1U/kg/dose) if blood glucose is > 15 mmol/l (and beware hypoglycaemia!).