Epilepsy in Adolescents and Adults
Epilepsy in Adolescents and Adults
General and supportive measures
G40.0-9
DESCRIPTION
See Epilepsy.
Diagnostic criteria
- The diagnosis of epilepsy is usually made clinically.
- Take an adequate history and get an accurate witness description of the seizures to define the type of epilepsy.
- Juvenile myoclonic epilepsy and absence seizures specifically should be considered and identified, as some first line medicines may be less efficacious or may even worsen seizure frequency or severity.
- Patients with new onset epilepsy should have a CT scan (this is essential in immunocompromised patients), and other investigations as clinically indicated.
Special considerations
Women and girls of child-bearing potential and pregnancy
- Antiseizure medicines during pregnancy can cause structural or physical malformations and neurodevelopmental harms that may impact learning and education.
- The risk of antiseizure medicine to the unborn child needs to be balanced against the risk of uncontrolled seizures to both the mother and unborn child.
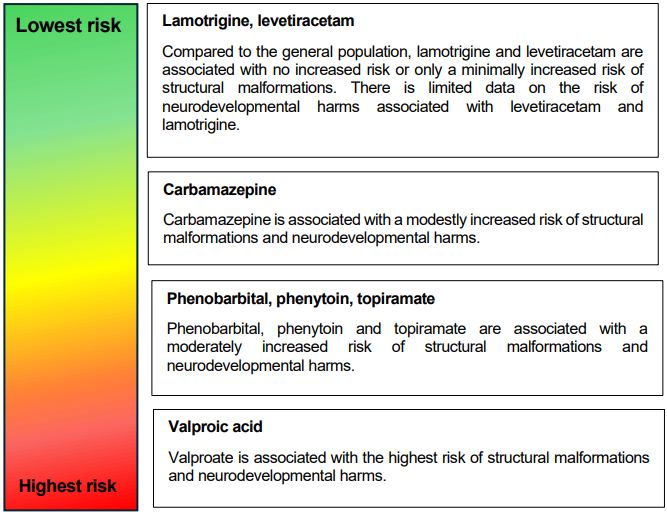
- The risk associated with each antiseizure medicine during pregnancy differs (see Figure 4).
- Women and girls of child-bearing potential with epilepsy should be counselled regarding contraception and the need to plan pregnancy.
− NOTE: There are important drug-drug interactions between hormonal contraceptives (except DMPA) and several anticonvulsant medicines (e.g. carbamazepine, phenobarbital, phenytoin).
− Progestin-only injectable contraceptives or IUCDs are the preferred contraceptive methods for women of child-bearing potential on ASM medication. See Chapter 7: Family planning.
| It is crucial to treat epilepsy during pregnancy to prevent epileptic seizures, which pose significant risks to both the mother and the foetus/infant |
- In pregnant women, women of child-bearing potential (i.e. women < 55 years), and young girls who are likely to need to continue treatment into their child-bearing years, should initiate treatment with a lower risk antiseizure medication.
− Lamotrigine and levetiracetam are safer antiseizure medicines to use.
− Large amounts of data consistently show no increased risk of major congenital malformations associated with the use of lamotrigine or levetiracetam at usual doses.
− Since lamotrigine requires slow dose titration, initiation of lamotrigine is best suited to low-risk patients.
− Levetiracetam may be used if there is a poor response or adverse effects to lamotrigine, or in high-risk patients.
− Seizure risk is based on clinical judgement (discuss with a specialist if unsure). In general, high-risk patients are those with frequent seizures, a previous history of hospitalisation for seizures, or previous history of status epilepticus. Low-risk patients are those with infrequent seizures, no previous hospitalisation for seizures, and no history of status epilepticus. - Valproate must not be used in pregnant women, women of childbearing potential and young girls who are likely to need continued treatment into their child-bearing years.
− In women who take valproate while pregnant, around 1 in 9 babies (11%) will have a major birth defect and about 3–4 children in every 10 may have neurodevelopmental problems and these disorders can be seriously debilitating and permanent (e.g. delayed learning to walk and talk, lower intelligence, poor speech and language skills, memory problems, autism or autism spectrum disorders, attention deficit hyperactivity disorder).
− In situations where valproate is deemed the only option in a female patient after all other treatment options have been ruled out, health professionals (prescribers and dispensers) are required to:- Regularly review treatment.
- Provide counselling on the risks of valproate use in pregnancy.
- Ensure that the woman has completed and signed an acknowledgment of risk form annually:
https://www.sahpra.org.za/wp-content/uploads/2025/05/GLF-CEM-PVS01_v2-Valproate-Annual-Risk-Acknowledgement-Form-ARF.pdf - Provide supplemental folic acid, oral, 5 mg daily.
- Women and girls with epilepsy who discover they are pregnant should not abruptly stop their ASM due to the risk of seizures.
− Women and girls who become pregnant while on valproate should be transitioned off valproate and onto levetiracetam as early as possible during pregnancy to decrease the risk of neurodevelopmental harms, provided their seizures are not refractory to other antiseizure medications. - During pregnancy, women may experience an increased number of seizures.
− This may be due to sleep deprivation, increased emotional stress and changes in antiseizure medicine concentrations.
− Antiseizure medication concentrations may decrease during pregnancy due to decreased absorption from nausea and vomiting, increased volume of distribution and increased clearance of antiseizure medicines.
− There is increased hepatic metabolism of lamotrigine and increased renal clearance of levetiracetam in pregnancy, which returns to normal post-partum. Increase the dose if necessary, according to clinical response.
Click on the image to enlarge.
Figure 1. Risk of congenital structural malformations and neurodevelopment harms associated with various antiseizures medicines.
Increasing risk refers to increasing number of pregnancies or children affected. Adapted from Pennell PB. Neurotherapeutics. 2016 and Medicines & Healthcare products Regulatory Agency safety leaflet.
LoE:IVb31
|
CAUTION – ASM and pregnancy Children born to women taking valproate are at significant risk of birth defects (11%) and persistent developmental disorders (40%). Valproate is contra-indicated and should be avoided in pregnancy and women or adolescents of child-bearing potential. |
LoE:IIIb32
Children and adolescents transitioning to adult care
- Children and adolescents whose seizures are controlled on levetiracetam should be continued on levetiracetam in adulthood.
Adults on ART
- Lamotrigine is the preferred ASM in people on ART because of fewer medicine interactions.
- Phenytoin, phenobarbital and carbamazepin]e are enzyme inducing ASM. Due to potential drug interactions with ARVs, switch these medicines to lamotrigine.
- Where concurrent use of dolutegravir and carbamazepine, phenytoin, or phenobarbital is unavoidable, double dolutegravir dose to 50 mg 12-hourly.
- The metabolism of lamotrigine is induced by lopinavir/ritonavir and atazanavir/ritonavir. The dose of lamotrigine may need to be increased if patients are switched to/initiated on lopinavir/ritonavir or atazanavir/ritonavir.
GENERAL AND SUPPORTIVE MEASURES
- Patients should record dates and, if possible, times of seizures in a seizure diary. Review seizure diary at each consultation for assessment of therapy.
- Patients with epilepsy should be issued a disease identification bracelet, necklace or card.
- Patients with uncontrolled seizures should avoid driving, swimming, working at heights and operating machinery until they have been seizure free for one year. Refer to an occupational therapist for rehabilitation and a workplace assessment. The patient should sign in the medical notes that they have received workplace and lifestyle advice.
- Provide counselling and advice on:
− the adverse effect of alcohol on seizures,
− sleep hygiene,
− the effect of missing a dose of medication,
− discontinuing the medication without advice of a doctor.
MEDICINE TREATMENT
Acute treatment
Manage acute seizure and status epilepticus as per seizures/status epilepticus, see Epileptic seizures, and Status epilepticus.
Maintenance Treatment
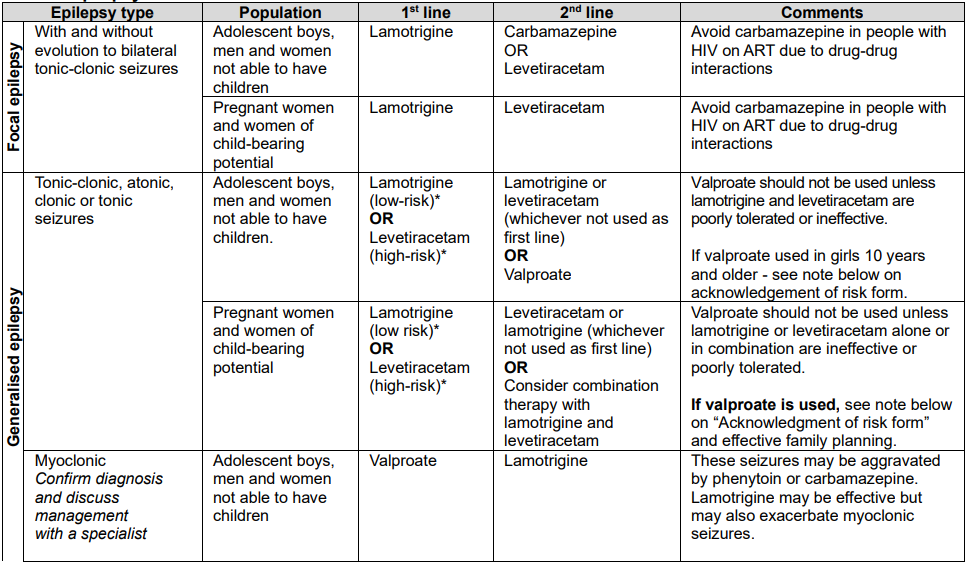
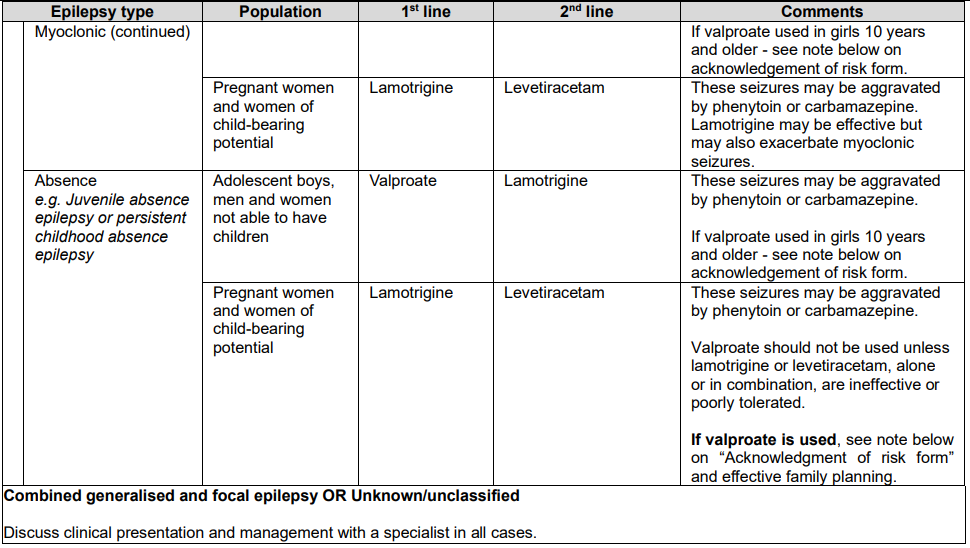
- Refer to the table below for guidance around the choice of medicine by seizure type.
- HIV status, child-bearing potential and pregnancy are important determinants of medicine choice.
- The antiseizure treatment strategy should also be individualised based on use of other medicines, comorbidities, as well as response to medication, and adverse effects.
- The goal of medicine treatment is to prevent recurrent seizures and optimise quality of life.
- As a general rule, a single ASM (monotherapy) is best. Progressively increase the dose of the ASM until the seizures are controlled or clinically important side effects occur.
- Recommended drug doses are general guides and will be effective in most patients. However, some patients may need much higher or lower doses. Doses should be increased at 2-weekly intervals only.
- If the initial ASM fails to achieve satisfactory control (no seizures) at optimal dosages, or causes unacceptable adverse effects, then a trial of a second ASM medicine may be commenced.
- Initiate second medicine, titrate to therapeutic dose, then gradually reduce and stop the first ASM over 6–8 weeks or longer if necessary. (See notes below for individual medicines).
- Failure of second-line monotherapy, after exclusion of alcohol use/misuse and poor adherence, may require add on therapy. Add on therapy may be initiated by a medical practitioner in consultation with a specialist.
- Therapeutic drug monitoring is not necessary in stable patients, but should be performed in the following situations:
− To confirm ASM toxicity in a symptomatic patient,
− In patients with poor seizure control,
− To confirm suspected poor adherence despite self-reported good adherence. - Phenytoin is not recommended in the table below, however, it may be continued in adults whose seizures are well-controlled on phenytoin. Therapeutic drug monitoring should be conducted in patients receiving higher than usual doses of phenytoin.
- Long term use of phenytoin and carbamazepine are associated with potential risks. Continued use of these ASM requires careful consideration of the balance between benefits and risks in individual patients.
|
MEDICINE INTERACTIONS Phenytoin, phenobarbital and carbamazepine are potent enzyme inducing agents and should be used with caution with other medicines metabolised by the liver, especially warfarin, antiretrovirals, progestin subdermal implants and oral contraceptives |
LoE:IVb33
Table 5: Epilepsy treatment in adolescents and adults
Click on the image to enlarge.
Click on the image to enlarge.
NOTE:
Lamotrigine is the preferred first line treatment for all adult patients, including women of child-bearing potential, pregnant women, and people living with HIV.
Lamotrigine requires slow dose up-titration and may not be suitable in people at high-risk of seizures. *High-risk patients are those with frequent seizures, a previous history of hospitalization for seizures, or previous history of status epilepticus. Low-risk patients are those with infrequent seizures, no previous hospitalization for seizures, and no history of status epilepticus.
If valproate is used in girls, an acknowledgment of risk form must be obtained annually, even if not of child-bearing potential. Girls aged 10 years and older should receive effective family planning and consider a long-acting form of contraception. https://www.sahpra.org.za/wp-content/uploads/2025/05/GLF-CEM-PV-S01_v2-Valproate-AnnualRisk-Acknowledgement-Form-ARF.pdf.
LoE:IVb34
*Assess level of risk (high vs low) based on clinical judgement and discuss with a specialist if unsure. In general, high-risk patients are those with frequent seizures, a previous history of hospitalization for seizures, or previous history of status epilepticus. Low-risk patients are those with infrequent seizures, no previous hospitalization for seizures, and no history of status epilepticus.
- Lamotrigine, oral (Doctor initiated).
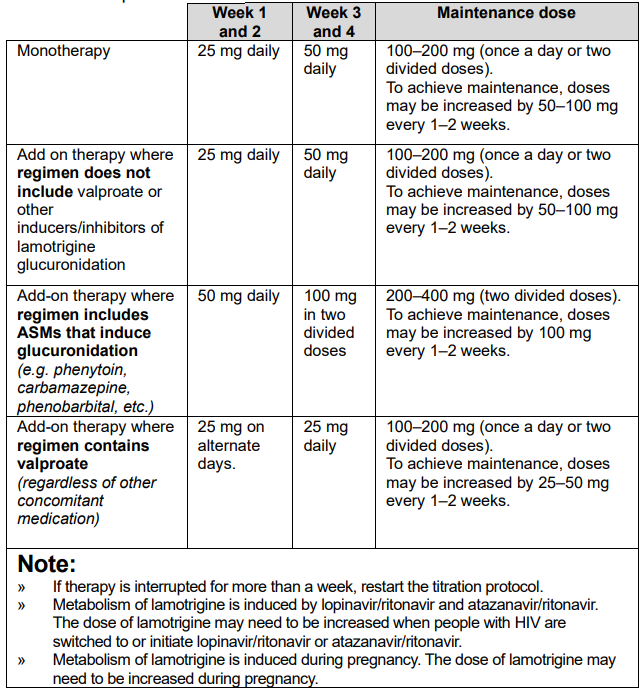
Table 6: Dosing table for lamotrigine as monotherapy or add-on therapy
Dose-titrate as per table below:
LoE:IVb35
|
CAUTION - LAMOTRIGINE Lamotrigine may cause Stevens-Johnson Syndrome. |
LoE:IVb36
- Carbamazepine, oral:
- Start with 100 mg 12 hourly.
- Increase by 100–200 mg/day at weekly intervals according to seizure control and adverse events.
- Usual maximal dose: 600 mg 12 hourly.
LoE:IVb37
- Levetiracetam, oral Initially 250 mg 12 hourly, increasing to a therapeutic dose of 500 mg 12 hourly.
- Dose can be adjusted upwards in increments of 500 mg 12 hourly every 2 to 4 weeks to a maximum of 1500 mg 12 hourly (3000 mg per day).
- Dose can be adjusted upwards in increments of 500 mg 12 hourly every 2 to 4 weeks to a maximum of 1500 mg 12 hourly (3000 mg per day).
- Valproate, oral:
- Usual starting dose: 200–300 mg 12 hourly.
- Increase, as required, every 3 days to 2 weeks (depending on the seizure frequency) to a maximum dose of 1200 mg 12 hourly.
- Phenytoin, oral, 4.5–5 mg/kg (lean body mass) daily, at night.
- Only consider continuing phenytoin in patients already well controlled on phenytoin, and in whom phenytoin is well tolerated.
- Usual starting and maintenance dose in adults: 300 mg once daily.
- Dose increases above 300 mg should be done in no more than 50 mg increments at intervals no shorter than 2 weeks.
- Doses > 300 mg/day of phenytoin are potentially toxic and could lead to permanent cerebellar damage. Caution and frequent monitoring of drug levels are obligatory at doses > 300 mg daily.
LoE:IVb
Poorly controlled epilepsy
- Ensure diagnosis of epilepsy and seizure type is confirmed, and imitators of epileptic seizures excluded.
- Ask the patient, and if possible, a family member or primary care giver, about the following, as these factors can influence decisions regarding medicine therapy:
− Has the patient been adherent in taking the medication regularly for at least 2 weeks or more before the seizure? Ask about medicine dosage and frequency.
- If non-adherence has been established, ask for reasons contributing to non-adherence and offer guidance.
− Has the patient recently used some other medicine and/or herbal remedy (i.e. look for drug interactions, substance use or traditional medicine use). − Is there a chance that alcohol is involved?
− If ≥ 1 of the above are present, address the problem/s but leave ASM unchanged (unless dose adjustment is necessary because of a drug interaction). Reassess the patient within 2 weeks.
REFERRAL
- All patients with new onset epilepsy for further investigations such as neuroimaging.
- Patients with seizures other than generalised tonic-clonic seizures, including absence seizures.
- Patients with an increase in seizure frequency despite attempts to address adherence issues.
- Patients with a change in seizure type.
- Patients who have been seizure free on ASM for 2 years or more, to review medications and to consider cessation of treatment.
- Development of new neurological signs and symptoms.
- Adverse medicine reactions or suspected toxicity in children.
- If uncontrolled on monotherapy, and patient has been shown to be adherent, referral for initiation of a second agent can be made to a medical officer at primary care level and does not require hospital / specialist referral.
Information that should accompany each referral case:
- Number and frequency of seizures per month (or year).
- Date and time of most recent seizures.
- Detailed description of the seizures, including:
− Presence of an aura or warning signs
− what happens during the seizure? (give a step-by-step account)
− is the person conscious during the seizure?
− how long do the seizures last on average?
− what does the patient experience after the seizure?
− how long does this experience last? - Is there a family history of seizures?
- What is the initial date of diagnosis?
- Is there evidence of alcohol use?
- Is there another medical condition, e.g. diabetes, HIV and what medication is used?
- What is the name and dosage of the ASM used to date?
- Does the person return regularly for repeat of medication?
Standard Treatment Guidelines and Essential Medicines List for South Africa, Primary Healthcare, 2020-4_Version 1.0_26 May 2025
Chapter 15: Central Nervous System Conditions_15.7 Epilepsy_15.7.2 Epilepsy in Adolescents and Adults
Drugs mentioned
ICD-10 codes
- G40.0Localization-related (focal)(partial) idiopathic epilepsy and epileptic syndromes with seizures of localized onset
- G40.1Localization-related (focal)(partial) symptomatic epilepsy and epileptic syndromes with simple partial seizures
- G40.2Localization-related (focal)(partial) symptomatic epilepsy and epileptic syndromes with complex partial seizures
- G40.3Generalized idiopathic epilepsy and epileptic syndromes
- G40.4Other generalized epilepsy and epileptic syndromes
- G40.5Special epileptic syndromes
- G40.6Grand mal seizures, unspecified (with or without petit mal)
- G40.7Petit mal, unspecified, without grand mal seizures
- G40.8Other epilepsy
- G40.9Epilepsy, unspecified