Epilepsy in Children <13 Years of Age
Special considerations General and supportive measures Medicine treatment Referral A child may be diagnosed with focal, generalised, combined generalised and focal, or unknown epilepsy types. Special considerations Seizures in neonates Seizures in the neonatal period seldom confer a diagnosis of epilepsy. For management of seizures, see Seizures, neonatal . Underlying conditions and co-morbiditie
General and supportive measures
A child may be diagnosed with focal, generalised, combined generalised and focal, or unknown epilepsy types.
Special considerations
Seizures in neonates
Seizures in the neonatal period seldom confer a diagnosis of epilepsy. For management of seizures, see Seizures, neonatal.
Underlying conditions and co-morbidities
The sequelae of neurocysticercosis and TB meningitis are a common cause of childhood epilepsy in South Africa. See Neurocysticercosis and Meningitis, tuberculosis in children.
Common co-morbidities with epilepsy which need to be managed in conjunction with treatment of the epilepsy include:
- Neurodevelopmental disorders, e.g., autism spectrum disorder, intellectual disability, attention deficit hyperactivity disorder, specific learning disorders.
- Behavioural and psychiatric disorders, e.g., anxiety disorder, depression, oppositional defiant disorder, conduct disorder, sleep disorders.
- Cognitive and academic difficulties.
- Developmental delays, particularly with epilepsies that have their onset in early childhood.
Infantile epileptic spasms
Infantile epileptic spasms (previously called infantile spasms) are a type of seizure that typically occur in infants between 3 and 12 months of age. They involve brief, repetitive stiffening of the body (for 1-2 seconds), typically recurring in clusters, and usually happen when the infant is waking up or falling asleep.
These spasms are often associated with a severe epilepsy syndrome called West syndrome or Infantile Epileptic Spasms Syndrome, which includes:
- Epileptic spasms
- Developmental delay or regression
- A specific abnormal EEG pattern called hypsarrhythmia
Infantile spasms are a medical emergency. Early diagnosis and treatment are crucial to prevent long-term developmental problems. Discuss with a specialist and refer immediately.
See Epilepsy syndromes for additional information.
Children living with HIV on ART
Drug interactions between ASM and ARVs can arise from several mechanisms, including liver metabolism (increased or decreased) and competition for protein binding. There is a lack of strong evidence to guide clinicians at present.
The following points are important to remember when treating epilepsy in patients on ART:
- Carbamazepine, phenobarbital and phenytoin induce the hepatic Cytochrome P450 and glucuronidation hepatic enzyme systems, and may lead to sub-therapeutic ARV plasma levels, especially INSTIs, NNRTIs and PIs. If clinically indicated, monitor ASM levels in patients taking concurrent ART and ASM therapy.
- Consider lamotrigine, levetiracetam or valproate, and avoid prescribing carbamazepine, phenytoin or phenobarbital.
Girls likely to need treatment when of child-bearing potential/ after 10 years of age
- The potential for child-bearing must be considered in all girls requiring treatment for epilepsy.
- Choose the ASM with the least potential for harm in pregnancy (see Figure 1 below).
- Valproate should not be used if the child is likely to require epilepsy treatment as they grow older / develop child-bearing potential, unless other ASMs are not effective or intolerable. Annual acknowledgment of risk must be obtained if valproate is used.
- Girls over the age of 10 years should be counselled regarding sexual activity and contraception needs.
- Refer any girls who may be vulnerable to sexual abuse to a social worker.
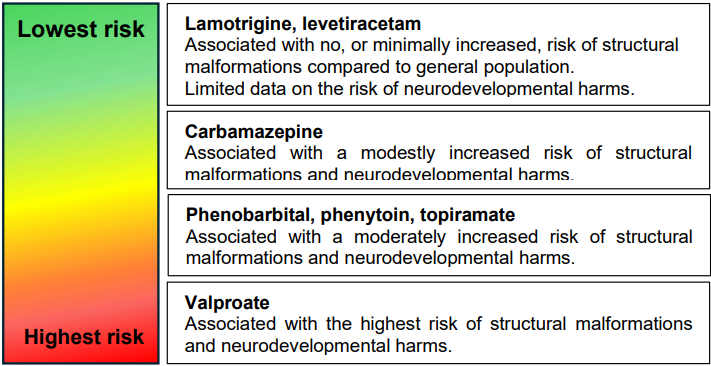
Click on image to enlarge.
Figure 1. Risk of congenital structural malformations and neurodevelopment harms associated with various antiseizure medicines. Increasing risk refers to increasing number of pregnancies or children affected. (Adapted from Pennell PB. Neurotherapeutics. 2016 and Medicines & Healthcare products Regulatory Agency safety leaflet).
LoE:IVb16
GENERAL AND SUPPORTIVE MEASURES
- Offer ongoing counselling to the patient and caregiver about epilepsy, its associated complications and comorbidities, e.g., learning difficulties, ADHD, anxiety, and aggression.
- Encourage participation in activities of daily living and ensure that the patient is not precluded from school and lifestyle activities, unless valid safety concerns are evident.
MEDICINE TREATMENT
The goal of medicine treatment is to prevent recurrent seizures and optimise quality of life balanced against potential adverse effects of ASM. Being seizure-free may not be achievable in all children and may require individualised treatment goals, e.g., severe to profound intellectual disability with intractable seizures that do not interfere with the care of that child. Cautious escalation of treatment should be done with consideration for potential adverse effects. In the setting of apparent drug-resistant epilepsy, revisit the diagnosis, check adherence, consider if the prescribed ASM and dose are correct, and refer to specialist if treatment goals are still not achieved.
Acute therapy
Manage acute seizure and status epilepticus as per seizures/status epilepticus, see Epileptic seizures, and Status epilepticus.
Maintenance therapy
Principles of management
- Monotherapy is preferred.
- Combination therapy, if necessary, should be specialist initiated in the form of add-on management.
- As a general rule, start with low doses according to the lower dose per kilogram for the child and titrate upwards slowly until seizures are controlled. This is often at the low-to-mid-therapeutic dose range.
- If seizures continue, titrate to high therapeutic doses, monitoring for unacceptable adverse effects.
- If the patient experiences unacceptable adverse effects, verify that the ASM is being given correctly and that the epilepsy type has been correctly identified, then consider cross-titrating to another ASM.
- ASMs can interact with other drugs, affecting their effectiveness and safety. These interactions mainly occur through changes in drug metabolism (enzyme induction or inhibition) and protein binding.
- Monitoring of therapeutic ASM levels is only indicated when there is concern about toxicity or adherence. It is not recommended when titrating to establish the appropriate dose.
Continuation and cross-titration of treatment
Cross-titration may be required when changing from one ASM to another if there is poor control or adverse effects. Add on the new medication and uptitrate to a therapeutic dose. When seizures are controlled, slowly reduce and stop the initial medication (doses should only be changed at 2 weekly intervals).
In most children it is appropriate to continue effective ASM therapy as they grow older as indicated by the type of epilepsy. Exceptions are:
- Valproate in girls approaching puberty and child-bearing potential. Valproate should be deprescribed by cross-titration onto another suitable ASM in girls at approximately 10 years of age. Lamotrigine and levetiracetam are the safest ASMs in pregnancy and therefore the first choices in girls and women of child-bearing potential. Carbamazepine and topiramate are both teratogenic and should be avoided.
- Phenobarbital may be initiated in infants under 6 months of age or children with severe or profound intellectual disability, for whom the adverse effects will not interfere with their care or activities of daily living. In children who are established on phenobarbital, cross-titration onto another suitable ASM should be undertaken by 2 years of age.
Table 1: Epilepsy treatment in children 1 month to ≤ 12 years
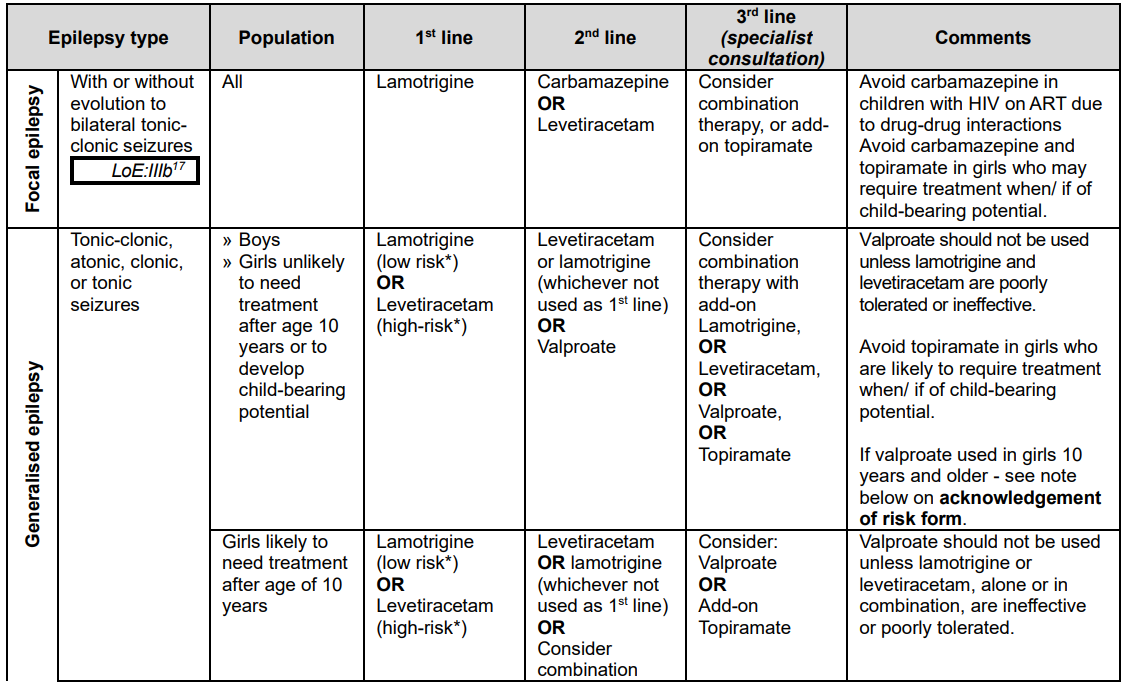
Click on the image to enlarge.
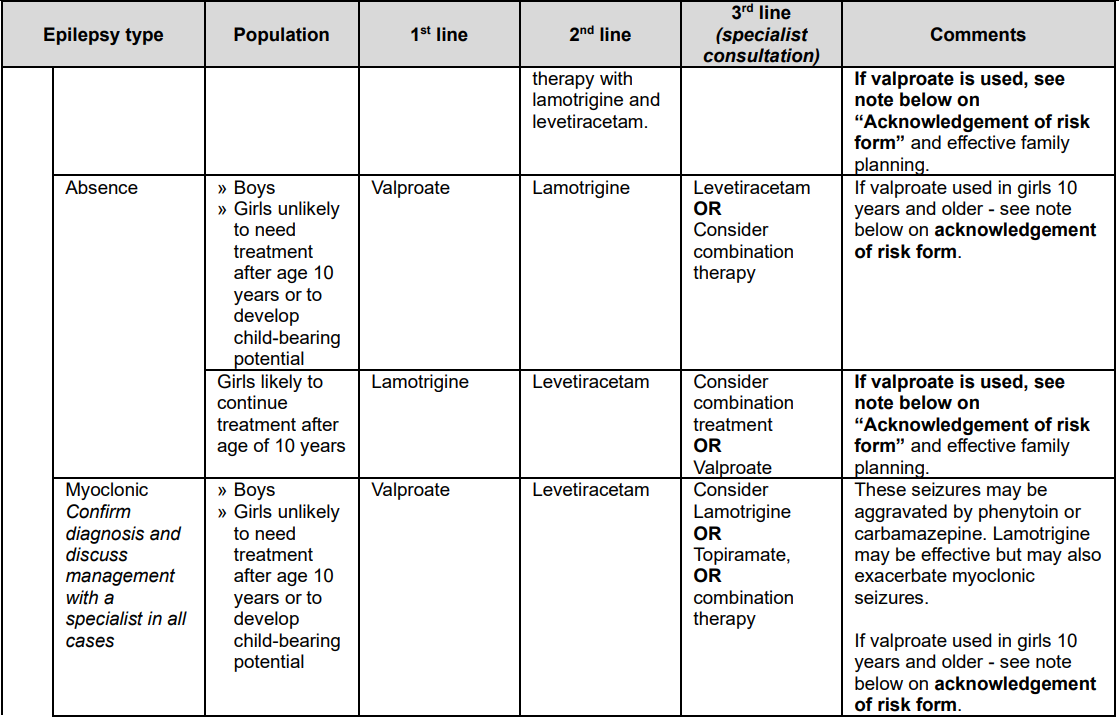
Click on the image to enlarge.
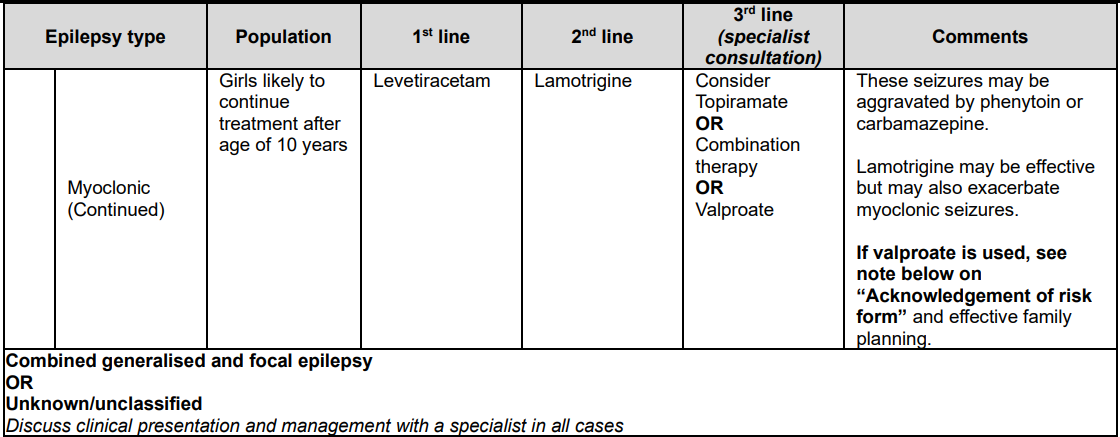
Click on the image to enlarge.
NOTE:
Lamotrigine is the preferred first line treatment for all adult patients, including women of child-bearing potential, pregnant women, and people living with HIV.
Lamotrigine requires slow dose up-titration and may not be suitable in people at high-risk of seizures.
*Assess level of risk (high vs low) based on clinical judgement and discuss with a specialist if unsure. In general, high-risk patients are those with frequent seizures, a previous history of hospitalization for seizures, or previous history of status epilepticus. Low-risk patients are those with infrequent seizures, no previous hospitalization for seizures, and no history of status epilepticus.
If valproate is used, acknowledgment of risk must be obtained annually, even if not of child-bearing potential. https://www.sahpra.org.za/wp-content/uploads/2025/05/GLF-CEM-PV-S01_v2-Valproate-Annual-Risk-AcknowledgementForm-ARF.pdf
Girls aged 10 years and older should receive effective family planning and consider a long-acting form of contraception.
LoE:IVb18
- Lamotrigine, oral
Monotherapy:- Starting daily dose: 0.2 mg/kg/dose.
- Increase slowly at 2 weekly intervals to 1–5 mg/kg/dose 12–24 hourly.
- Rapid escalation is associated with adverse side-effect of skin rash.
Table 2: Dosing regimens when lamotrigine is used as add-on therapy:
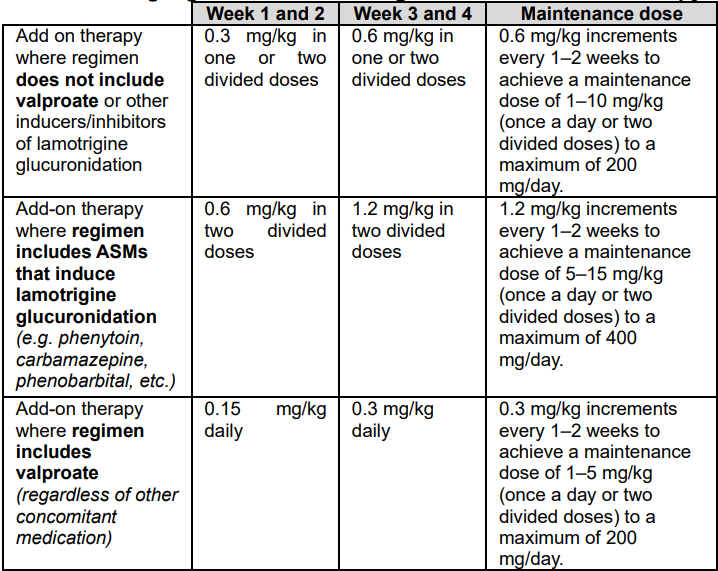
Click on the image to enlarge.
LoE:IVb19
|
CAUTION - LAMOTRIGINE Lamotrigine may cause Stevens-Johnson Syndrome. |
- Levetiracetam, oral,
- Infants 1 to < 6 months:
- Initial dose: 7 mg/kg/dose twice daily.
- Increase dosage every 2 weeks by 7 mg/kg/dose twice daily based on response and tolerability to the recommended dose of 21 mg/kg/dose twice daily. - Infants ≥ 6 months and children < 4 years:
- Initial dose: 10 mg/kg/dose twice daily.
- Increase dosage every 2 weeks by 10 mg/kg/dose twice daily based on response and tolerability to the recommended dose of 25 mg/kg/dose twice daily. - Children ≥ 4 years to 12 years:
- Initial: 10 mg/kg/dose twice daily.
- Increase dosage every 2 weeks by 10 mg/kg/dose twice daily based on response and tolerability to the recommended dose of 30 mg/kg/dose twice daily.
- Infants 1 to < 6 months:
- Carbamazepine, oral, 5 mg/kg/day (starting dose), 8–12 hourly.
- Increase slowly by 2 mg/kg/day at 2 weekly intervals.
- Usual maintenance total daily dose: 10–20 mg/kg/day.
- Maximum total daily dose: 20 mg/kg/day.
- Dosage intervals: syrup 8 hourly, tablets 12 hourly.
- Exacerbates myoclonic seizures and absence seizures.
- Valproate, oral, 5 mg/kg/dose (starting dose), 8–12 hourly.
- Increase by 5 mg/kg weekly to 15–20 mg/kg/day, given 8–12 hourly over 4 weeks.
- Usual maintenance dose: 20-30 mg/kg/day.
- Maximum total daily dose: 40 mg/kg/day.
- Exclude liver dysfunction prior to initiating therapy (at least ALT) in children under 2 years, or if there is clinical suspicion of liver dysfunction or metabolic disease.
- Consider hepatotoxicity if clinical signs such as nausea, vomiting, malaise, jaundice or abdominal pain develop.
- Phenobarbital, oral, 3–5 mg/kg/dose as single dose at night.
- May be used in children under six months of age.
- Not recommended as maintenance therapy for children older than 2 years due to undesirable side-effects such as sedation, behaviour disturbances, hyperkinesia and dependence, except in situations where there is poor adherence to other drugs.
- Exacerbates absence seizures.
REFERRAL
- Seizures suggesting complex or syndromic epilepsy.
- All myoclonic seizures and infantile epileptic spasms at presentation.
- Mixed seizure types in a single patient.
- Focal seizures for neuroimaging if not available at the facility (MRI preferred).
- Neuroregression (loss of previously acquired milestones or skills).
- Seizures persisting despite two appropriate ASMs (drug-resistant epilepsy).
Information that should accompany each referral case.
- Number and frequency of seizures per month (or year).
- Date and time of most recent seizures.
- Detailed description of the seizures, including:
− aura or warning sign
− what happens during the seizure? (give a step-by-step account)
− is the person conscious during the seizure?
− how long do the seizures last on average?
− what does the patient experience after the seizure e.g. weakness, loss of speech?
− how long does this experience last? - Is there a family history of seizures?
- What is the initial date of diagnosis?
- Is there evidence of alcohol use or exposure?
- Are there any comorbid conditions, e.g. diabetes, HIV and what medication is used?
- What is the name and dosage of the ASM used to date?
- Does the person return regularly for repeat of medication?
Click here to access NEMLC Report.
Standard Treatment Guidelines and Essential Medicines List for South Africa, Paediatric Hospital Level_Updated May 2025
Chapter 13: The Nervous System_13.4 Epilepsy_13.4.1 Epilepsy in Children <13 Years of Age