Jaundice and Haematologic Issues
Neonatal jaundice Maternal Rhesus negative Polycythaemia Anaemia Neonatal jaundice 60% of term newborns and approximately 70% of preterm newborns will become jaundiced in their first week of life. It is important to understand that jaundice is not a diagnosis. It is a sign. Every baby with jaundice requires a serum bilirubin. Bilirubin results must be checked on the same
Neonatal jaundice
60% of term newborns and approximately 70% of preterm newborns will become jaundiced in their first week of life. It is important to understand that jaundice is not a diagnosis. It is a sign.
Every baby with jaundice requires a serum bilirubin. Bilirubin results must be checked on the same day that they are taken. The Bilirubinometer in NICU can be used as a screening tool. If the level is within 50 of the phototherapy line (PTL) then do a venous blood gas (because of delays in getting formal results) and serum bilirubin (SBR) at the same time. If above PTL then start phototherapy (PTT). If the SBR is not at phototherapy level then please refer to Appendices 16 (Phototherapy chart) to decide on further management or discuss with a senior.
Patterns of jaundice: Jaundice may be “physiological” (appears on Day 3-4, peaks on day 4-5 in a term infant or day 4-6 in a preterm infant and resolves before 2 weeks).
Jaundice presenting within the first 24 hours of life is always pathological and is most likely due to hemolysis or conjugated hyperbilirubinemia.
Investigation: SBR, Hb/retics on baby with a group & coombs on both baby and mom.
Treatment: Start PTT if SBR above PTL. If SBR is 50 below exchange then start “intensive” phototherapy. Repeat serum bilirubin (SBR) 4–6 hourly. Redflag all results and discuss with the registrar and consultant.
Phototherapy and exchange transfusion guidelines (See Graphs appendix 1 and 2) - Determining which line of the graph to use: “Well term baby” i.e. no evidence of bilirubin induced neurological dysfunction (BIND), haemolysis, or other factors which could compromise the blood-brain barrier e.g. sepsis, acidosis and hypoxia. PTT & exchange transfusion (ET) as per National Guidelines.
Term baby “not well” i.e. with BIND, or haemolysis or other factors which could compromise the blood-brain barrier use the line below for phototherapy and exchange level.
Preterm babies: PTT & ET as per National Guidelines. If gestational age is known to be accurate, rather use that than the weight.
If jaundice near exchange transfusion level, it is considered a medical emergency
- “Intensive” phototherapy indicated
- Elevate baby or lower lights: such that the distance between the baby and the lights is 30cm
- Increase fluids by 20ml/kg only if the baby is behind on fluids e.g. primigravida mother with difficulty breastfeeding
- Continue to give oral feeds as far as possible to reduce enterohepatic circulation of bilirubin (however if exchange transfusion is imminent baby should be kept nil per os 2 hours prior to procedure)
- Ensure as much skin as possible receives phototherapy i.e. remove napkin etc. (only the eyes should be covered)
- Repeat SBR 4–6 hourly
Start photo immediately (i.e. prior to getting SBR result) if:
- Suspect Rh isoimmunization and baby jaundiced
- Pathological jaundice
- Jaundiced VLBW
- Any deeply jaundiced baby with jaundice extending onto limbs
If SBR near exchange transfusion range, please discuss the case with seniors.
Maternal rhesus negative
- All babies to Rh negative mothers must have a blood group and Coombs done on cord blood
- Examine the baby for signs of Rh-sensitization (pallor, HSM)
- SBR should be done within 12 hours of delivery since jaundice is usually not present at birth but may develop rapidly within hours
- The baby may be sensitized without the above signs present
- If cord blood is not sent, do blood group and coombs on mum and baby and Hb, reticulocyte count and SBR on baby
- Check maternal file for maternal Rh antibody titre levels, previous jaundiced babies or history of ectopic or miscarriages in a primigravida mother (indicates sensitization)
- Be sure that all tests are normal before discharging babies to Rh negative mothers
- Check that mom has been given Anti-D to prevent Rh-related disease in subsequent pregnancies
Neonatal follow up
- Any baby who required an exchange therapy, was near exchange or developed BIND needs neurodevelopmental follow up at the neonatal follow up clinic as well as audiology screening for sensorineural deafness
- If ongoing hemolysis is suspected baby may need to be brought back in a week for repeat Hb levels
Polycythaemia
Is defined as haematocrit >0.65. Polycythaemia increases blood viscosity, which reduces circulation and predisposes to sludging of blood in small blood vessels. Babies can be asymptomatic or symptoms may include: poor feeding, lethargy, hypoglycaemia, jaundice, NEC, seizures, acute kidney injury. Babies with a Hct > 0.65 get an extra 20 ml/kg/day of fluid. Treatment may be required for any infant with haematocrit > 0.7, or in symptomatic infants with a haematocrit >0.65. Treatment consists of a “partial exchange transfusion” giving normal saline in exchange for blood to reduce haematocrit to 0.55. The volume of the exchange should be 10-20ml/kg and is calculated by:
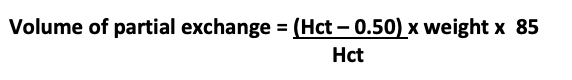
Anaemia
The normal haemoglobin (Hb) at birth is dependent on the gestational age of the infant. Term infants have an Hb of 14-20g/dl, preterms 16-21g/dl.
Physiological anaemia occurs at 6-12 weeks and is usually 10g/dl in a term infant but may be as low as 7g/dl in a VLBW (anaemia of prematurity).
Various factors influence the threshold for blood transfusions and include acute blood loss, gestational age, need for respiratory support or if the infant will undergo major surgery within 72 hours. ALL transfusions should be discussed with the consultant. Investigate for the cause before transfusion.
Transfuse if:
|
|
Criteria
|
Transfusion cut-off
|
|
1.
|
Infant at birth
|
Hb < 10g/dl
|
|
2.
|
Infant requiring respiratory support or any other
symptoms of anaemia
|
Hb < 8g/dl
|
|
3.
|
Asymptomatic infant
|
Hb < 7g/dl
|
Rahima Moosa Mother and Child Hospital - Neonatal Care Handbook 2023; Jaundice and haematologic issues; Neonatal jaundice, Maternal rhesus negative, Polycythaemia, Anaemia
Last checked for updates: January 2024