Medical Management of Etopic Pregnancy
Medical Management of Etopic Pregnancy
General Measures (stable mothers with presumed ectopic pregnancy)
Contraindications for the use of methotrexate
NOTE:
- Ruptured (or suspected ruptured) ectopic pregnancy must be stabilised and operated at the nearest hospital immediately (urgent resuscitation and surgery).
- Unruptured ectopic pregnancies in stable women can be referred to Tygerberg Hospital if they qualify for medical management.
- Medical management can be offered at district hospital level if the skill and infrastructure is available. In this case, after two doses of methotrexate, if the decline in ß-HCG is still <15% on day 14, refer for specialist care.
- Stable women with unruptured ectopic pregnancy that does not qualify for medical management can be referred to Tygerberg for laparoscopic management if the skill is not available at the base hospital, especially in women whose family is not competed yet or where there is a known history of infertility (check availability with registrar on call). Otherwise do laparotomy at district hospital.
General Measures (stable mothers with presumed ectopic pregnancy)
- Ensure there is no viable intra-uterine pregnancy:
- If the initial ß-HCG level is <1500 IU/L and transvaginal ultrasound cannot definitively identify an intrauterine or extrauterine gestation, serial ßHCG measurements are necessary to document either a growing, potentially viable, or a nonviable pregnancy.
- Repeat the ß-HCG in 48 hours.
- If the level has dropped, conservative management may be appropriate.
- The minimum rise in ß-HCG for a potentially viable pregnancy in women who present with symptoms of pain and/or vaginal bleeding is 53% every 2 days.
- If the ß-HCG level has increased by more than 50% or is now >1500 IU/L, a repeat scan should be done to exclude an intra-uterine pregnancy before methotrexate is administered.
Medical Management
Methotrexate should be the first-line management for women who are able to return for follow-up and who have the following characteristics:
- Haemodynamic stability and no significant pain
- An unruptured ectopic pregnancy with a mass smaller than 40 mm with no visible heartbeat
- Low serum ß-HCG, ideally less than 1500 IU/L but can be up to 5000 IU/L
- Certainty that there is no intrauterine pregnancy
- Willingness to attend for follow-up
- Normal baseline liver and renal function test results
- No contra-indication to methotrexate
Contraindications for the use of Methotrexate
- Evidence of immunodeficiency
- Moderate to severe anemia, leukopenia, or thrombocytopenia
- Sensitivity to methotrexate
- Active pulmonary disease
- Active peptic ulcer disease
- Clinically important hepatic dysfunction
- Clinically important renal dysfunction
- Breastfeeding
Protocol:
Day 1: Do urea, creatinine, AST, full blood count.
Administer Methotrexate intramuscular 50 mg/m2 of body surface area (BSA).
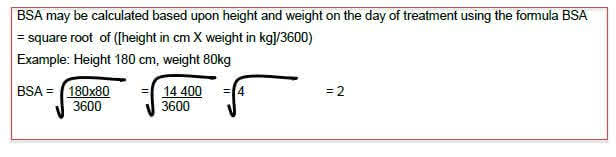
Click on the image to enlarge
Day 4: Repeat ß-HCG
Day 7: Repeat ß-HCG
If the decrease from day 4 to day 7 is ≥15%:
- Continue with weekly ß-HCG until undetectable
If decrease <15% and patient still fulfils the criteria for medical management:
- Give another dose of Methotrexate, IM, 50mg/m2 BSA
Repeat ß-HCG on day 14.
Note:
Folinic acid (Leucovorin) rescue is not needed for the single dose protocol described above, even if more than one dose of methotrexate is given.
Referral
After two doses of methotrexate, if the decline in b-hCG is still <15% on day 14, refer to Tygerberg for specialist care.
Click here to open the above content in the original PDF view
Tygerberg Hospital, Department of Obstetrics and Gynaecology; Medical Managemnet of Ectopic Pregnancy; Version: May 2013; Last checked for updates by EMGuidance: Oct 2023