Neonatal Hypoglycaemia / Hyperglycaemia
Neonatal Hypoglycaemia
Management of hypoglycaemia in labour and the postnatal wards
Insulin sliding scale for hyperglycaemia
Management of hypoglycaemia in labour and the postnatal wards
- Feeds need to be established early, preferably within the first hour.
- Keep warm and encourage KMC for all babies.
- Healthy newborns that are asymptomatic need not have monitoring.
The following babies need to have a glucose level checked for 12 hrs (3hrly).
- Infant of a diabetic mom
- < 2kg or >4kg or <35 weeks gestation
- hypothermic
- lethargic
- poor or delayed feeding
- jittery
- resuscitated infants
- infants that had an assisted delivery
- babies with suspected meconium aspiration
- BBA babies (born before arrival)
- Babies on β-blockers, salbutamol or oral hypoglycaemic agents
HGT 2.6 > 1.5mmol/l and tolerating feeds and asymptomatic:
- Give 10 ml/kg extra milk if already fed or give next feed if it is due.
- Add supplementary feeds to breast feeding if necessary.
- Repeat glucose within 30 min.
- If poor response (i.e. remains below 2.6mmol/l) contact the paediatrician.
- If normal, check the glucose again at 1hr then 3 hrly until stable for 24 hrs.
- If baby is HIV exposed and mom chooses exclusive breastfeeding, discuss with nursery for IVI line and admission. Please do not give formula to these babies.
HGT < 1.5 OR symptomatic OR not taking feeds:
- Call the Paediatrician on call and/or the nursery to arrange urgent transfer to the nursery.
- Give feed as above while waiting or a nasogastric tube may be passed for feeds if not sucking.
- IV access needs to be obtained for emergency management. 2ml/kg of 10% DW can be given as a bolus while awaiting further management. Any HGT’s < 2.6 for three times → consider admission to nursery.
Management in nursery
Arterial values are usually higher than venous values. Lab glucose is usually 10-18% higher than ward Hgt.
Symptoms of hypoglycaemia (non-specific and similar to other disorders in neonates): Apnoea, cyanotic spells, convulsions, irritability, jitteriness, lethargy and tachypnoea. Ensure that other disorders such as sepsis and HIE which have similar presentation is not missed. Symptoms of hypoglycaemia should improve with correction of hypoglycaemia.
Causes
Diminished production/stores eg prem/SGA infant. Increased utilisation eg IDM, post exchange transfusion. Both eg sepsis, asphyxia, hypothermia, IEM, glycogen storage disorders, polycytaemia, adrenal insufficiency.
Management
Calculate glucose delivery
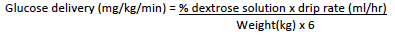
Glucose requirement for term infants is 4-6mg/kg/min and 6-8mg/kg/min for preterm infants.
If glucose is still low after a proper feed in the nursery or the baby is symptomatic/feeds contra-indicated, start an IVI infusion/check that existing IVI infusion is working properly. Give bolus 10%D/W (mix 50% D/W with sterile water in a ratio of 1:4) 2ml/kg. Follow with NNL infusion at rate to deliver 6mg/kg/min to term infant and 8mg/kg/min to preterm infant. If glucose levels do not increase to normal after bolus, send serum glucose to lab for confirmation. If resistant or persistant (>72hrs) episodes of hypoglycaemia (Hgt < 2.2) are present, also send special investigations as per TBH protocol book. Increase glucose delivery by 1-2mg/kg/min every 30 minutes up to a maximum of 15mg/kg/min. At reaching 10mg/kg/min, contact consultant for further advice. Might need Hydrocortisone, glucagon, diazoxide/octreotide as per TBH booklet protocol.
Insulin Sliding Scale for hyperglycaemia
Indicated for HGT persistently >14 despite changing to 5% glucose containing IVI fluids.
Infusion preparation
Use Actrapid/Humulin R (or equivalent short-acting Insulin) which contains 100IU Insulin per ml
Step 1: Take 0.1ml of above insulin and mix with 10ml 0.45% Saline. 1ml of this solution contains 1 IU of Insulin
Step 2: Take 1 ml of this solution and further dilute in 10ml 0.45% saline. 0.1ml of this solution contains 0.01IU of Insulin
Sliding scale to run as continuous intravenous infusion. Reconstitute a new solution every 6 hours if still required.
Dosage: 0.01IU/kg/hr = 0.1ml/kg/hr
| Insulin Sliding Scale: Infusion preparation as above | ||
| Hgt/blood glucose | Insulin usual rate | High rate |
| > 19 mmol/l | 0.4 ml/kg/hr | 1 ml/kg/hr |
| > 13.8 - 19 mmol/l | 0.2 ml/kg/hr | 0.5 ml/kg/hr |
| > 11 – 13.8 mmol/l | 0.1 ml/kg/hr | 0.2 ml/kg/hr |
| > 6.6 – 11 mmol/l | 0.1 ml/kg/hr | 0.1 ml/kg/hr |
| < 6.6 mmol/l | Stop insulin infusion and start Neonatalyte | Stop insulin infusion and start Neonatalyte |
Note
Monitor glucose hourly while on insulin therapy.
Alternatively subcutaneous bolus insulin can be used.
Actrapid/Humulin R 1ml=100IU Dose: 0.1-0.2 U/kg every 6-12 hours subcutaneously as required.