Not growing well (including failure to thrive/growth faltering) *New*
ICD-10 codes: R62.0 / R62.8 / R62.9 Description General measures Conditions which justify recommending that mothers do not breastfeed Medicine treatment Referral DESCRIPTION Children and infants who have either: Unsatisfactory weight gain (growth curve flattening or weight loss) on the Road to Health chart/ booklet. OR Low weight for age (but WHZ > -2) Note: Babies who were premature and
ICD-10 codes: R62.0/R62.8/R62.9
Description
General measures
Conditions which justify recommending that mothers do not breastfeed
Medicine treatment
Referral
DESCRIPTION
Children and infants who have either:
- Unsatisfactory weight gain (growth curve flattening or weight loss) on the Road to Health chart/ booklet.
OR
- Low weight for age (but WHZ > -2)
Note: Babies who were premature and are growing parallel to or better than the z-score line, should not be classified as having failure to thrive or not growing well.
Not growing well may be due to:
- Insufficient food intake due to anorexia and illness or poor availability of food.
- Insufficient uptake of nutrients, e.g. malabsorption.
- Insufficient use of nutrients for growth due to chronic disease.
- Increased demand for nutrients due to illness such as TB and HIV/ AIDS.
Conduct a feeding and clinical assessment to determine the cause. Exclude anaemia.
GENERAL MEASURES
- Counselling on nutrition (see below).
- Nutritional supplementation should be supplied unless there is a correctable cause.
- Assess the general condition of the child.
- Assess the child for possible HIV and TB, and manage appropriately.
- Assess for other long-term health conditions, and manage appropriately.
- Assess the child’s feeding and recommend actions as outlined below.
- Provide supplements according to child’s age to meet specific nutritional needs.
- Provide adequate micronutrients.
- Ensure that immunisations are up to date. Record the dose given on the Road to Health chart/booklet.
- Follow up monthly. If responding, review the child every two months.
- Refer for social assistance if needed.
Feeding recommendations for all children:
0 - 6 months of age
Breastfeed exclusively- feed at least 8 times in 24 hours.
If formula is medically indicated (refer below) or if the mother has chosen to formula-feed the child, discuss safe preparation and use with the mother.
6 - 12 months of age
Continue breastfeeding (breastfeed before giving foods).
Introduce complementary foods at six months of age. Start by giving 2-3 teaspoons of iron-rich food such as mashed vegetables or cooked dried beans.
Children 6 - 8 months should be given two meals daily, gradually increasing the number of meals so that at 12 months the child is receiving 5 small meals.
For children who are not growing well, mix margarine, fat, or oil with their porridge.
12 months to 2 years of age
Continue breastfeeding. If the child is not breastfed, give 2 cups of full cream cow’s milk every day. Make starchy foods the basis of the child’s meal. Give locally available protein at least once a day, and fresh fruit or vegetables twice every day.
2 - 5 years of age
Give the child his/her own serving of family foods 3 times a day. In addition, give 2 nutritious snacks e.g. bread with peanut butter, full cream milk or fresh fruit between meals.
CONDITIONS WHICH JUSTIFY RECOMMENDING THAT MOTHERS DO NOT BREASTFEED
Infants with a small number of metabolic diseases qualify to receive specialised infant formula. These infants should be managed in tertiary centres.
Maternal medical condition that may justify temporary or permanent avoidance of breastfeeding:
- Severe illness that prevents a mother from caring for her infant, e.g.: sepsis, renal failure.
- Herpes simplex virus type 1 (HSV-1): direct contact between lesions on the mother’s breasts and the infant’s mouth should be avoided until all active lesions have resolved.
- Maternal medications: sedating psychotherapeutic medicines, anti-epileptic medicines and opioids (may cause drowsiness and respiratory depression in the infant), radioactive iodine-131, excessive use of topical iodine or iodophors (especially on open wounds or mucous membranes), cytotoxic chemotherapy.
Infants who qualify to receive infant formula as part of the supplementation scheme:
- The mother has died or infant has been abandoned.
- Other individual circumstances deemed necessary by a multidisciplinary team.
- Infants of mothers who are failing second or third line ARV treatment (VL >1000 copies/mL) should be advised not to breastfeed.
MEDICINE TREATMENT
- Multivitamin, oral, daily.
Empiric treatment for worms (this will not treat tapeworm):
- Mebendazole, oral.
- Children 1 - 2 years: 100 mg 12 hourly for 3 days.
- Children > 2 - 5 years: 500 mg as a single dose.
OR
- Albendazole, oral, single dose.
- Children 1 - 2 years: 200 mg as a single dose.
- Children ≥ 2 years and adults: 400 mg as a single dose.
- Vitamin A (retinol), oral, 6 monthly.
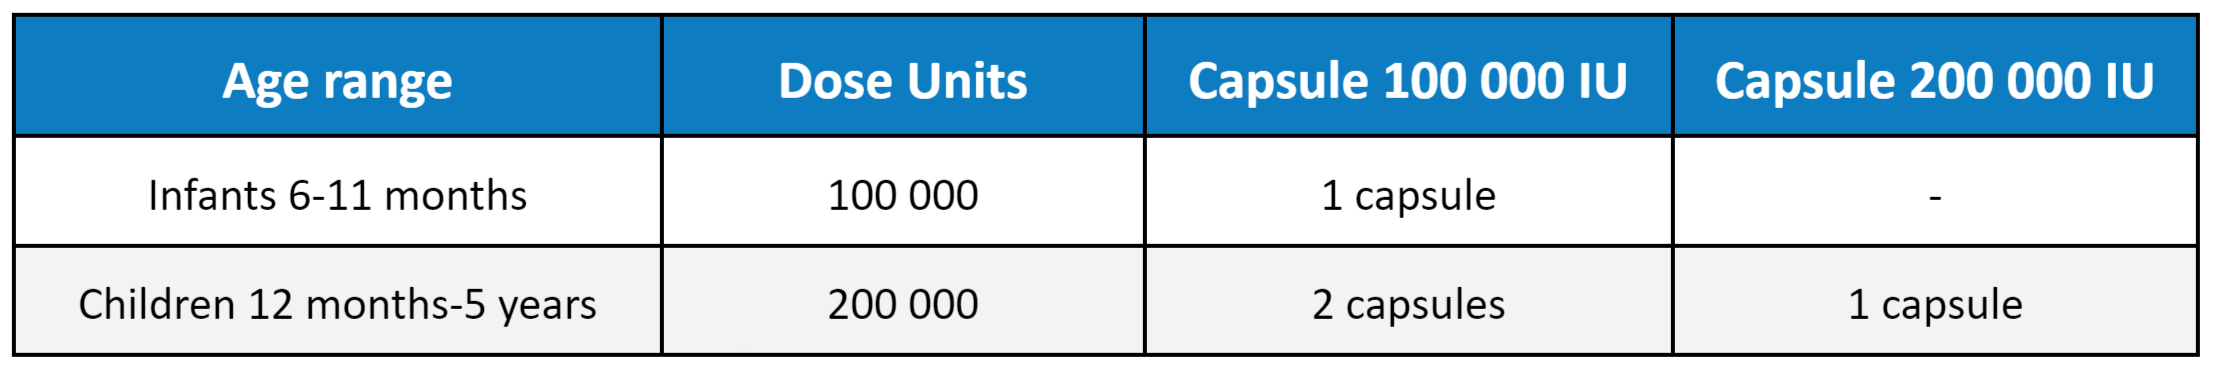
Click on table to enlarge
Anaemia:
See Anaemia.
REFERRAL
- No response to treatment.
- All children other than those with insufficient food intake (If there is inadequate food intake, refer to a social worker, if available).
- Severe malnutrition.
Standard Treatment Guidelines and Essential Medicines List for South Africa, Primary Healthcare Level, Updated for the 2023 Edition