Palliative Care
Palliative care
WHO definition of palliative care
Essential steps for Identifying and discharging a palliative care patient
Step 1: On admission
Step 2: Early in admit
Step 3: Pain Management Principles
Step 4: Discharge Planning
GSH Chronic pain service
WHO definition of palliative care
Palliative care is an approach that improves the quality of life of patients and their families facing the problem associated with life-threatening illness, through the prevention and relief of suffering by means of early identification and impeccable assessment and treatment of pain and other problems, physical, psychological and spiritual.
Essential steps for identifying and discharging a palliative care patient
Step 1: On admission : Use the spict tool to identify patients requiring palliative care
(Insert SPICT model as you have done)
Step 2: Early in admit : Practical steps to prepare for palliative care patient discharge
| Steps | Tasks | Examples |
| Diagnosis | Ensure patient and family have received language appropriate and compassionate information | “What have you been told about your diagnosis?” Provide brief, clear clarification as indicated |
| Prognosis | Ensure done at patient’s pace. Can be done over time. Never give false hope. Ensure adequate opportunities provided for questions and reflections. | “How much do you want to know about prognosis?” “Your disease is serious. We share in your hopes but also want to help prepare you for what might occur.” What questions do you have now?” (re-query as needed) |
| Advance care planning | MD initiates in hospital | Referral to MDT |
| Multidisciplinary team referral | MD identifies services needed to improve Quality of Life at discharge | OT for wheelchair SW for financial matters Spiritual care for total pain |
| Symptom management | Ensure pain and non-pain symptoms addressed | Counsel patients on pain management principles Dispel morphine myths |
Step 3: Pain Management Principles
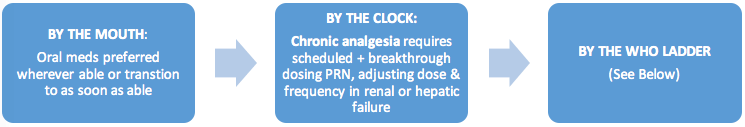
| WHO Pain Ladder | ||
| STEP 1 | PARACETAMOL and/or NSAIDS | |
| STEP 2 | TRAMADOL + PARACETAMOL OR LOW DOSE MORPHINE (2.5-5mg Q4 hourly) | Tramadol dosing is Q6 hourly DC tramadol if starting morphine Renal impairment, decrease frequency to Q6 or Q8 hourly |
| STEP 3 | STRONG OPIOID (Morphine best due to cost, availability, familiarity) | Opioid Naïve: Mist morphine 2.5-5mg Q4 hourly + same dose for breakthrough pain PRN Previously on Tramadol: DC tramadol. Mist morphine 5-10mg Q4 hourly + same dose for breakthrough pain PRN |
Morphine up-titration:
- Calculate total morphine used in last 24 hours (scheduled + breakthrough), divide into 4 hourly dosing
- e.g. Patient used Mist morphine 10mg Q4 hourly + 3 breakthrough doses of 10mg in last 24 hours. This totals 90mg. The new dose is Mist morphine 15mg Q4 hourly + 15mg for breakthrough pain PRN.
Other considerations:
- All patient on opioids (including tramadol) MUST have a bowel regimen
- e.g. senna 2 tabs + lactulose 15ml nocte, titrate to routine bowel movements
- Consider anti-emetic with opioid
- ex: metoclopramide 10mg Q8 hours PRN
- It is essential to proactively dispel the many myths about opioids in the South African society
- e.g. addiction, respiratory depression, hastened death
- Non-Pain Symptoms: Palliative care patients have high symptom burden. Individualised plans can be discussed with the Palliative Care Team at Groote Schuur Hospital
Step 4: Discharge planning : Ensure continuity of care
- Refer patient to hospice services if the patient qualifies
- Provide a comprehensive discharge letter
- Inclusive: discharge diagnosis, intended care, next appointment date, where to return if emergency, what actions have been taken by MDT, whom the patient is referred to, how much information the patient has received about the diagnosis
Ensure full awareness by patient and family
GSH Chronic pain service
Administered: Dept Anaesthetics
Referrals via clerk at E26 021 404 6114
Referral form on UCT Dept anaesthetics website
Contact: Dr Janieke van Nugteren
- Not diagnostic
- 3/12 waiting list
- Mostly:
- Chronic refractory back pain
- Chronic visceral pain
- Whiplash
- Trigeminal neuralgia
- Not generally for Oncology-related pain
- NOT for palliative care patients