People Living with HIV (PLHIV): Adults, Adolescents, and Children Irrespective of Age
Who TPT should be offered to TPT should be deferred or not offered if the individual living with HIV Management of TPT for PLHIV All immunocompromised people have a significant risk for developing TB disease and require an initial TPT course, regardless of significant exposure, once TB disease has been excluded. This includes people of all ages living with HIV (adults, pregnant and breastfeeding
TPT should be deferred or not offered if the individual living with HIV
All immunocompromised people have a significant risk for developing TB disease and require an initial TPT course, regardless of significant exposure, once TB disease has been excluded. This includes people of all ages living with HIV (adults, pregnant and breastfeeding women, adolescents, and children including infants older than 14 weeks of age).
See Section 6 (TPT in Pregnant and breastfeeding women with TB exposure or living with HIV) for pregnant women living with HIV and Section 5 (Child Contacts: Children weighing less than 25 kilograms and infants) for children living with HIV. After any new TB exposure, TB evaluation is again required along with a decision to start either TPT or TB treatment, i.e., the TB test and treat approach (see Section 4 - Adult, Adolescent and Older Child Contacts).
Who TPT should be offered to
TPT should be offered to all people on ART and people newly diagnosed with HIV (adults, pregnant and breastfeeding women, adolescents, and children of all weights) should be evaluated for TB disease and offered TPT, regardless of a TB exposure, once TB disease has been excluded.
Prior completion of either TB treatment or TPT do not exclude being offered TPT again if there is a new significant TB exposure.
TPT should be deferred or not offered if the individual living with HIV:
- is diagnosed with TB disease
- has active liver disease (acute or chronic)
- has symptoms and signs of severe peripheral neuropathy (could consider rifampicin only regimen)
- has a history of adverse reactions to any of the drugs used for TPT
- Uses alcohol excessively (and is unwilling or unable to scale down), defined as:
- for men: Five or more standard drinks on any day or 15 or more per week
- for women: Four or more standard drinks on any day or eight or more per week
For individuals with abnormal baseline liver function test results, sound clinical judgement is required to ensure that the benefit of TB preventive treatment outweighs the risks, and they should be tested routinely at subsequent visits.
Management of TPT for PLHIV
If PLHIV (or their caregivers in the case of children) decline TPT (despite counselling) then they should be counselled further regarding TB symptoms and should be offered TPT again at the next opportunity. If they develop symptoms suggestive of TB, they should be evaluated for TB disease and be offered either TB treatment, or be offered TPT again if TB disease has been excluded.
Evaluation for TB disease amongst PLHIV
Evaluation for TB disease includes symptom screening, physical examination, and diagnostic testing (regardless of symptoms). TB can either be bacteriologically confirmed or clinically diagnosed.
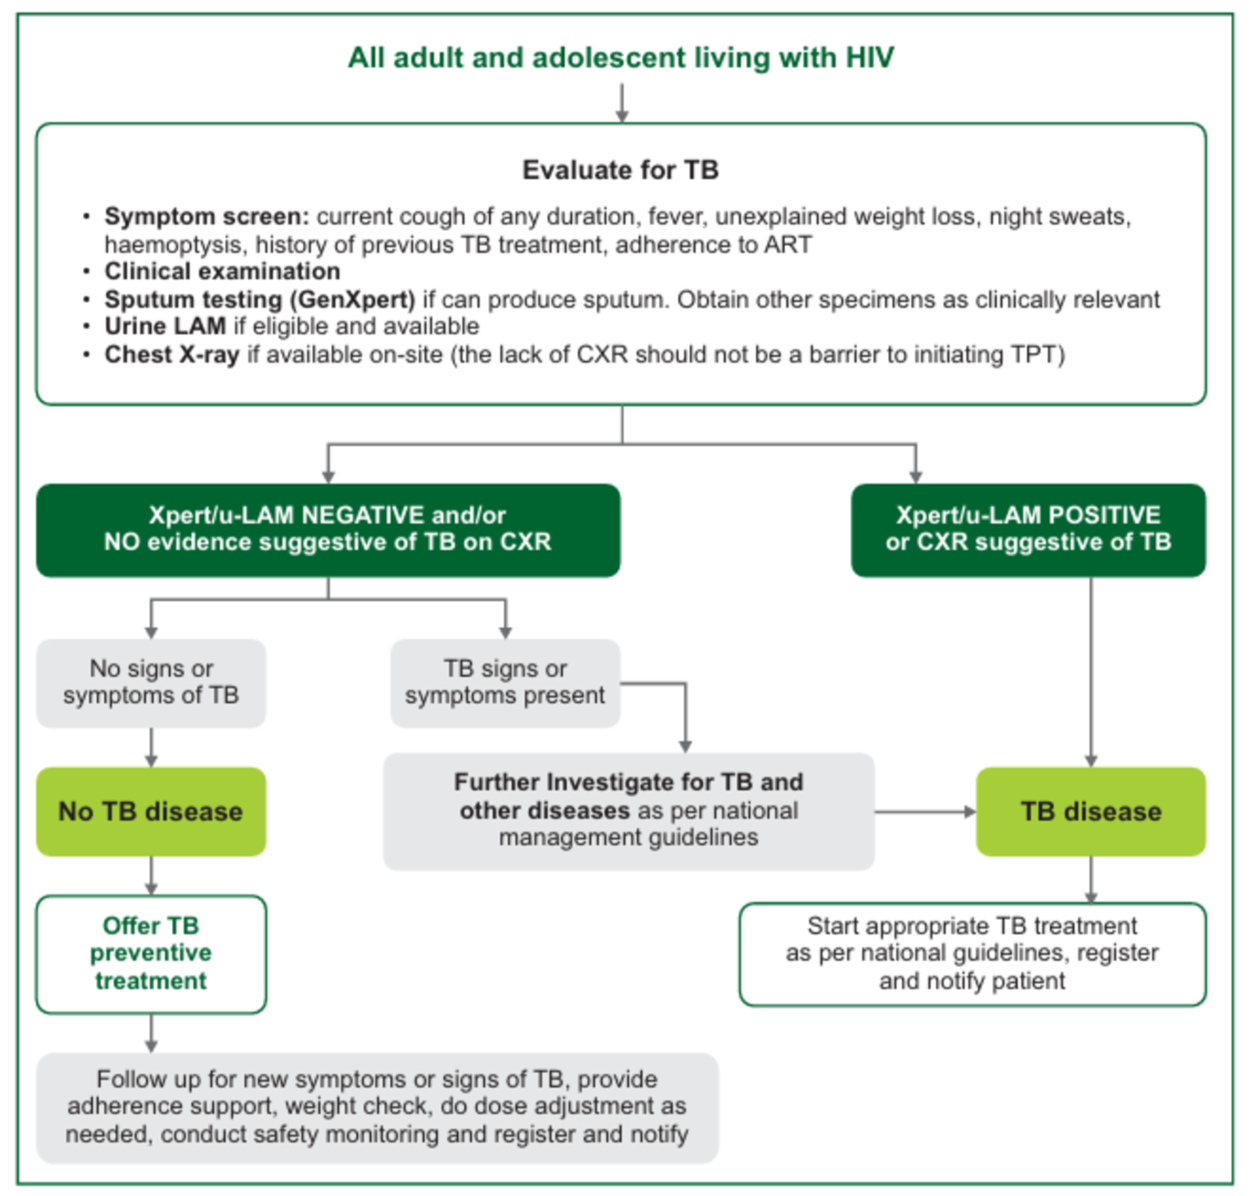
Amongst PLHIV adults (including pregnant and breastfeeding women), adolescents and older children, a Xpert sputum test is required irrespective of symptoms prior to initiating either TB treatment or TPT, i.e., the TB test and treat approach. PLHIV already in care should be screened for TB symptoms at each visit, with those symptomatic being tested for TB disease again (Figure 5).
PLHIV who complete TB treatment and have bacteriological proof of cure should be screened for TB symptoms and assessed for TPT eligibility if there is repeated exposure to TB or they have not taken TPT before. If bacteriological cure is not demonstrated after treatment completion, reassess for TPT eligibility three months after completion of TB treatment.
After completing a TPT course, PLHIV are eligible for TPT again after a significant TB exposure (see Section 4 - Adult, Adolescent and Older Child Contacts).
Symptom screening for TB disease amongst PLHIV (adults, adolescents, and children ≥25kg):
- current cough
- weight loss
- fever
- night sweats
- haemoptysis
Symptom screening for TB disease amongst PLHIV (children <25kg):
- current cough
- poor weight gain or failure to thrive or documented weight loss
- fever or night sweats
- lethargy/fatigue (decreased playfulness)
- visible neck mass/swelling
Diagnostic tests for TB disease amongst PLHIV (adults, adolescents, and children ≥25kg):
- a sputum sample should be obtained and tested using Xpert
- if no sputum sample can be obtained, then a chest radiograph should be obtained to rule out TB disease
- a urine sample can also be obtained from those who are eligible and tested using LF-LAM
- test of TB infection (TST/IGRA) are not a requirement to initiating TPT
Diagnostic tests for TB disease amongst children weighing less than 25 kilograms living with HIV
Refer to Section 5 (Child Contacts: Children weighing less than 25 kilograms and infants).
TPT regimens for PLHIV (adults, pregnant and breastfeeding women, adolescents, and children 25 kilograms or more)
For adults, adolescents and children ≥25kg living with HIV and initiating dolutegravir-containing ART, 12H is the preferred regimen. For those taking ART that are already virally suppressed (VL<50 copies/mL in the last six months) or those starting ART not containing Dolutegravir, 3HP is preferred.
Recommended daily dosages for 12H in adults, pregnant and breastfeeding women, adolescents and children weighing 25 kilograms or more living with HIV
| Drug | Isoniazid (H)* |
| Dose | 5mg/kg |
| Maximum Dose/day | 300mg |
| Duration | 12 months |
| Interval | Daily |
* If 300mg tablets are not available, use 100mg
Recommended weekly dosages for the 3HP regimen amongst adults, adolescents, and children weighing 25 kilograms or more living with HIV not on Dolutegravir or with supressed viral load.
| Body weight (kg) | Rifapentine | Isoniazid | Duration |
| 150mg tablets (weekly) | 300mg tablets (weekly) | ||
| 25-29.9 | 4 | 2 | 12 weeks (3 months) |
| 30 – 49.9 | 6 | 3 | 12 weeks (3 months) |
| >50 | 6 | 3 | 12 weeks (3 months) |
TPT regimens for children weighing less than 25 kilograms living with HIV
In children living with HIV initiating a dolutegravir-containing ART regimen, 6H is the preferred regimen.
Recommended daily dosages for 6H regimen amongst children living with HIV weighing less than 25 kilograms
| Drug | Isoniazid (H)* |
| Dose | 5mg/kg |
| Maximum Dose/day | 300mg |
| Duration | 6 months |
| Interval | Daily |
* If 300mg tablets are not available, use 100mg
For managing the TB-exposed infant, please refer to Section 5 (Child Contacts: Children weighing less than 25 kilograms and infants).
Figure 5. Algorithm for provision of TB preventive treatment for adults and adolescents living with HIV
Click on the image to enlarge.
- Tests of TB infection (tuberculin skin test/TST or IGRA) not required to initiate TPT in adults or adolescents with known TB exposure
- For management of DR-TB exposure, refer to the latest National DR-TB Guidelines
National Guidelines on the Treatment of Tuberculosis Infection, February 2023
People Living with HIV (PLHIV): Adults, Adolescents, and Children Irrespective of Age