Prelabour Rupture of the Membranes
The guidelines recommend management of common obstetric conditions at primary and referral level, based on local experience and evidence-based practice. They are not intended as strict protocols nor as standard operating procedures, but rather as a guide to safe effective management of common obstetric problems. The guidelines should be most useful to interns, medical officers and registrars.
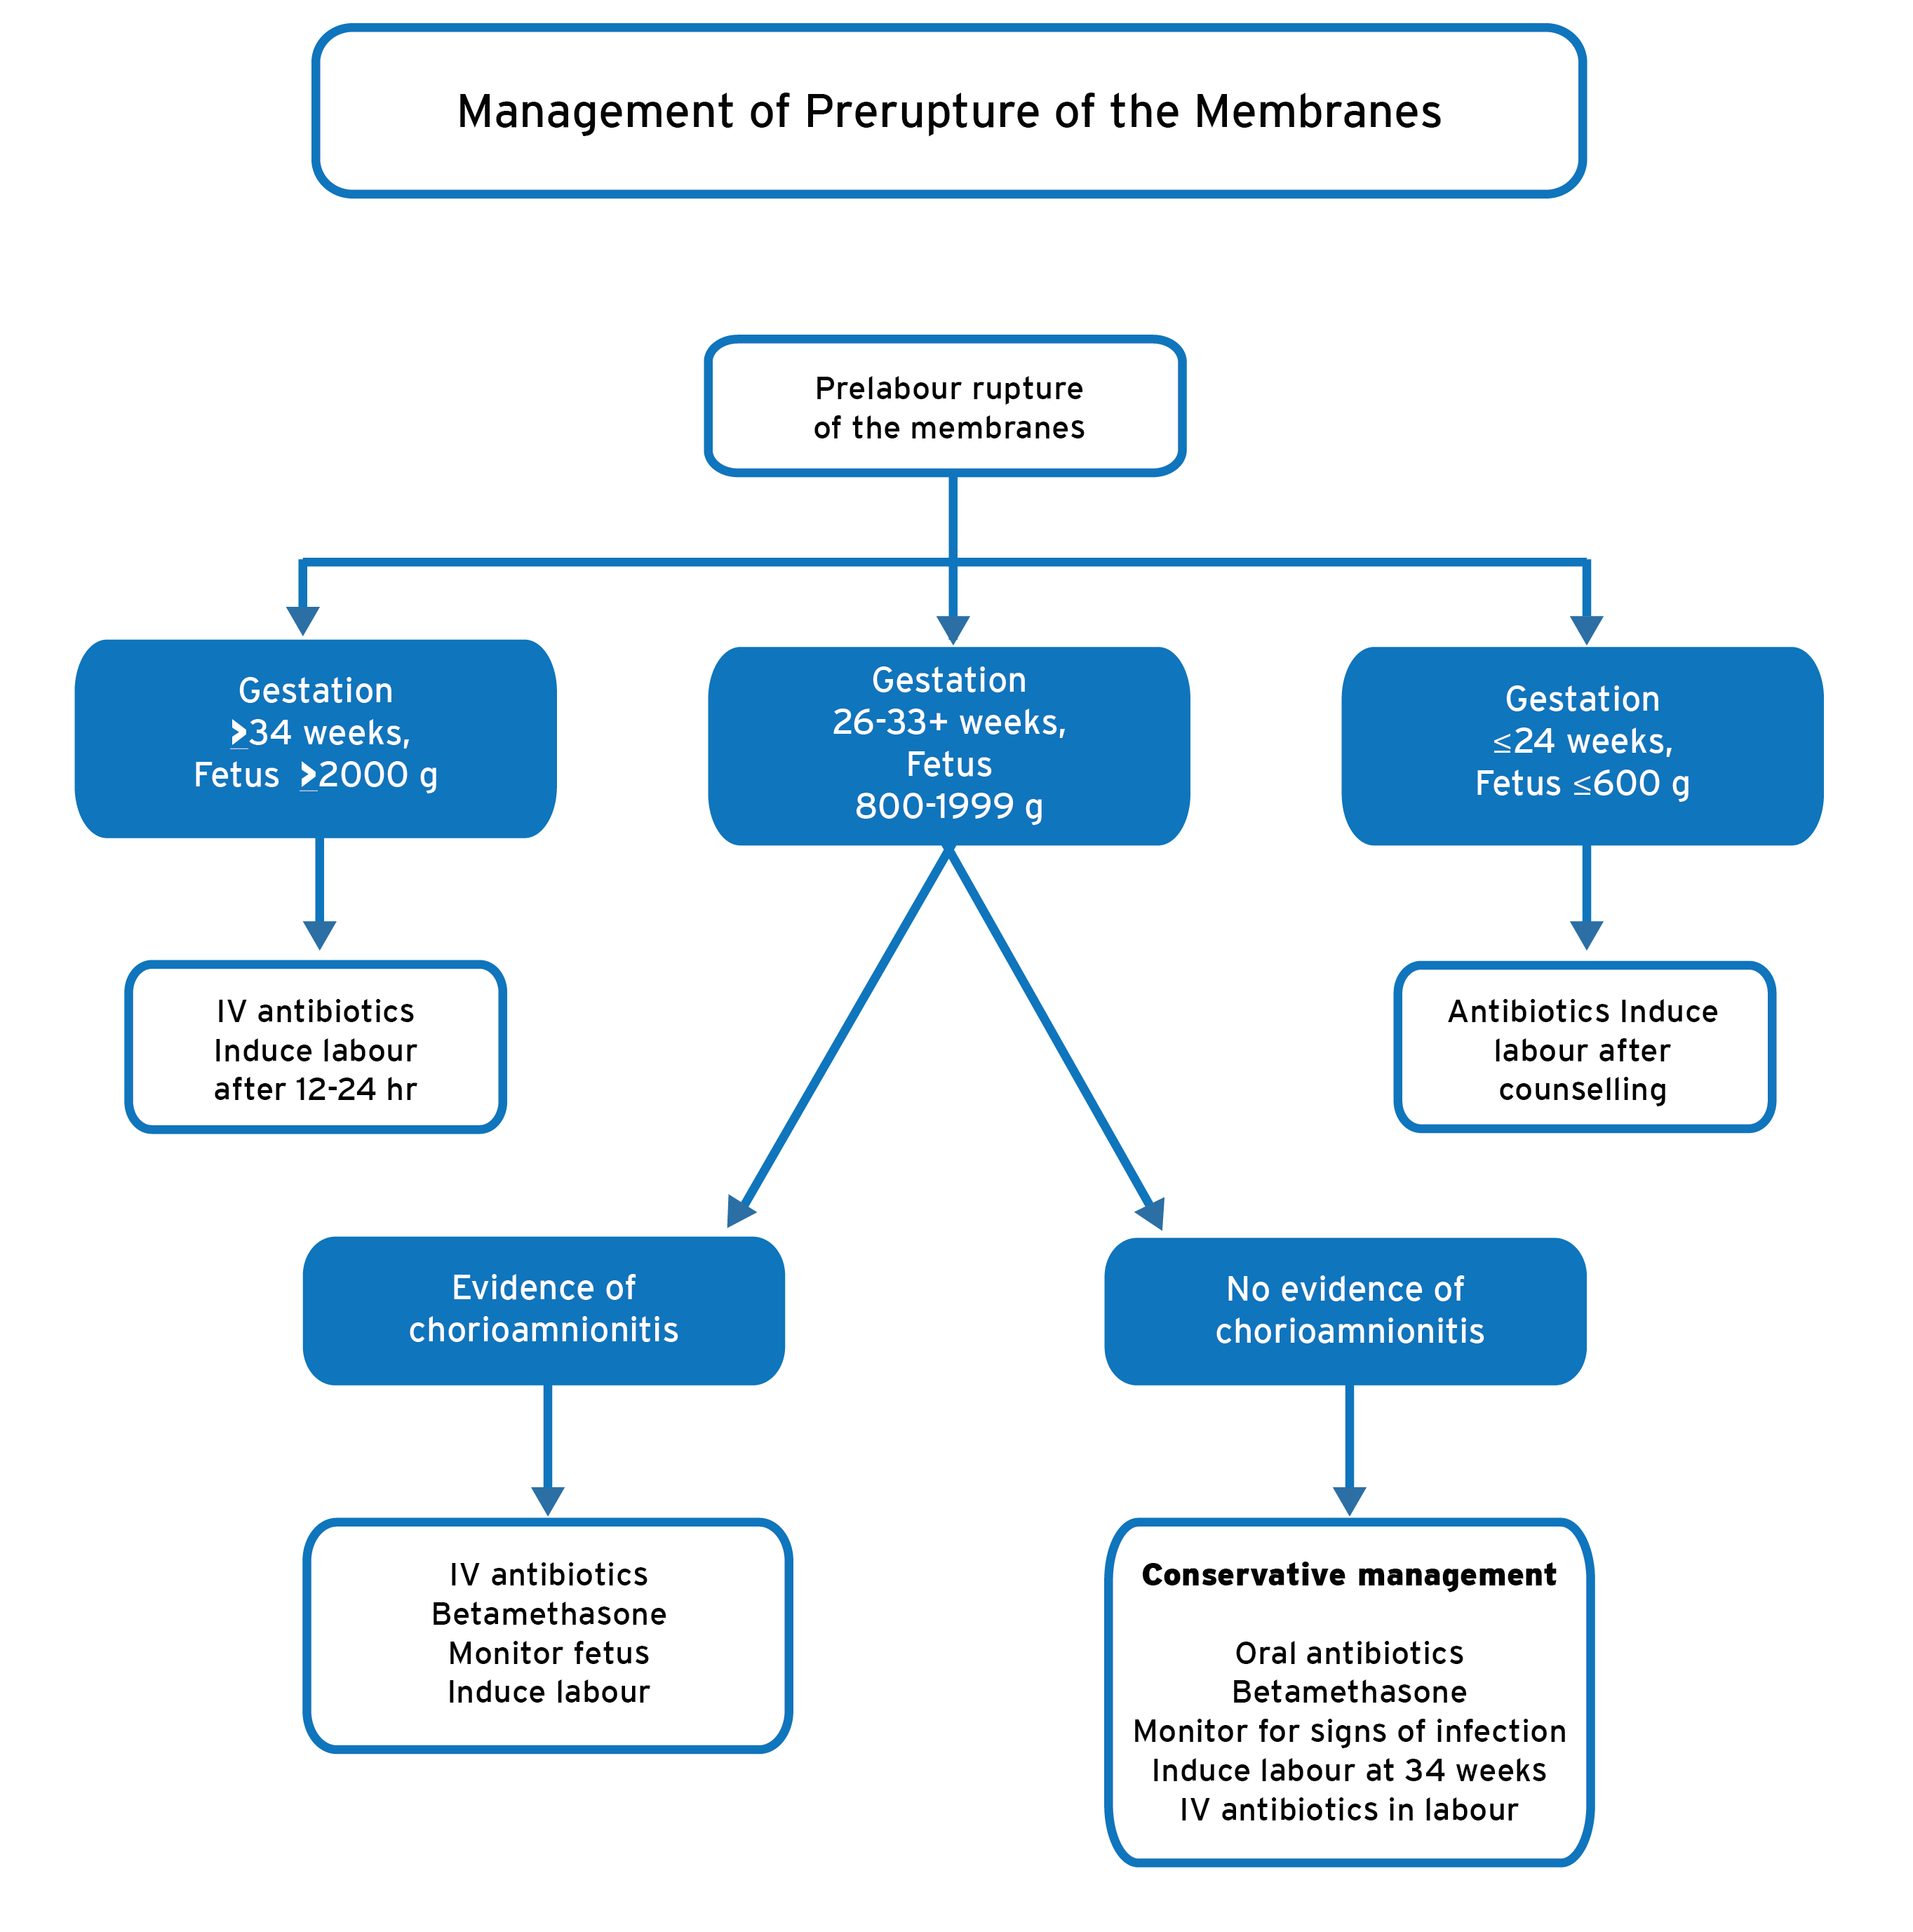
This is rupture of the membranes before the onset of labour. The diagnosis must be confirmed by visual inspection, speculum examination, pH testing of vaginal fluid or, if necessary, by liquor volume assessment on ultrasound. Management depends on gestational age and/or estimated fetal weight (by palpation or ultrasound).
Gestational age ≥34 weeks or estimated fetal weight ≥2 kg:
- Give ampicillin 2 g IV stat then 1 g IV 4 hourly & metronidazole 400 mg orally 8 hourly
- If in labour, allow labour to proceed
- If the woman is not in labour within 12-24 hours, induce labour with oxytocin or oral misoprostol, pending her Bishop score (page 95)
Gestational age 26-33+ weeks or estimated fetal weight 800 g – 1999 g:
- Admit to hospital
- Do not do digital vaginal examination if not in labour, as this may introduce pathogenic bacteria & cause chorioamnionitis
- Give azithromycin 500 mg orally daily (or amoxicillin 500 mg 8 hourly) AND metronidazole 400 mg orally 8 hourly for 5 days
- Give betamethasone 12 mg IM 12 hourly for 2 doses
- Do not tocolyse if labour starts, irrespective of doses of betamethasone given
- Observe temperature, heart rate, fetal heart rate, & pad checks 4 hourly
- Palpate daily for evidence of chorio-amnionitis (irritable or tender uterus)
- Do not measure white cell count or CRP (not sensitive or specific)
- Do CTG daily
- Induce labour at 34 weeks or at ≥2 kg, or if there are signs of chorioamnionitis
- During labour, give ampicillin 2 g IV stat, then 1 g IV 4 hourly
Gestational age ≤24 weeks or estimated fetal weight ≤600 g:
- Ensure that the membranes have definitely ruptured (reduced liquor volume on ultrasound). If in doubt, admit to hospital to observe for liquor drainage
- If rupture of membranes has been confirmed (inevitable miscarriage), induce labour with oxytocin 10-20 units in 1 L Ringer-lactate at 120 mL/hr, after full discussion of the problem with the woman
- In exceptional cases, e.g. poor obstetric history, pregnancy prolongation may be attempted in hospital under consultant supervision
MANAGEMENT OF PRELABOUR RUPTURE OF THE MEMBRANES