Preterm Labour
The guidelines recommend management of common obstetric conditions at primary and referral level, based on local experience and evidence-based practice. They are not intended as strict protocols nor as standard operating procedures, but rather as a guide to safe effective management of common obstetric problems. The guidelines should be most useful to interns, medical officers and registrars.
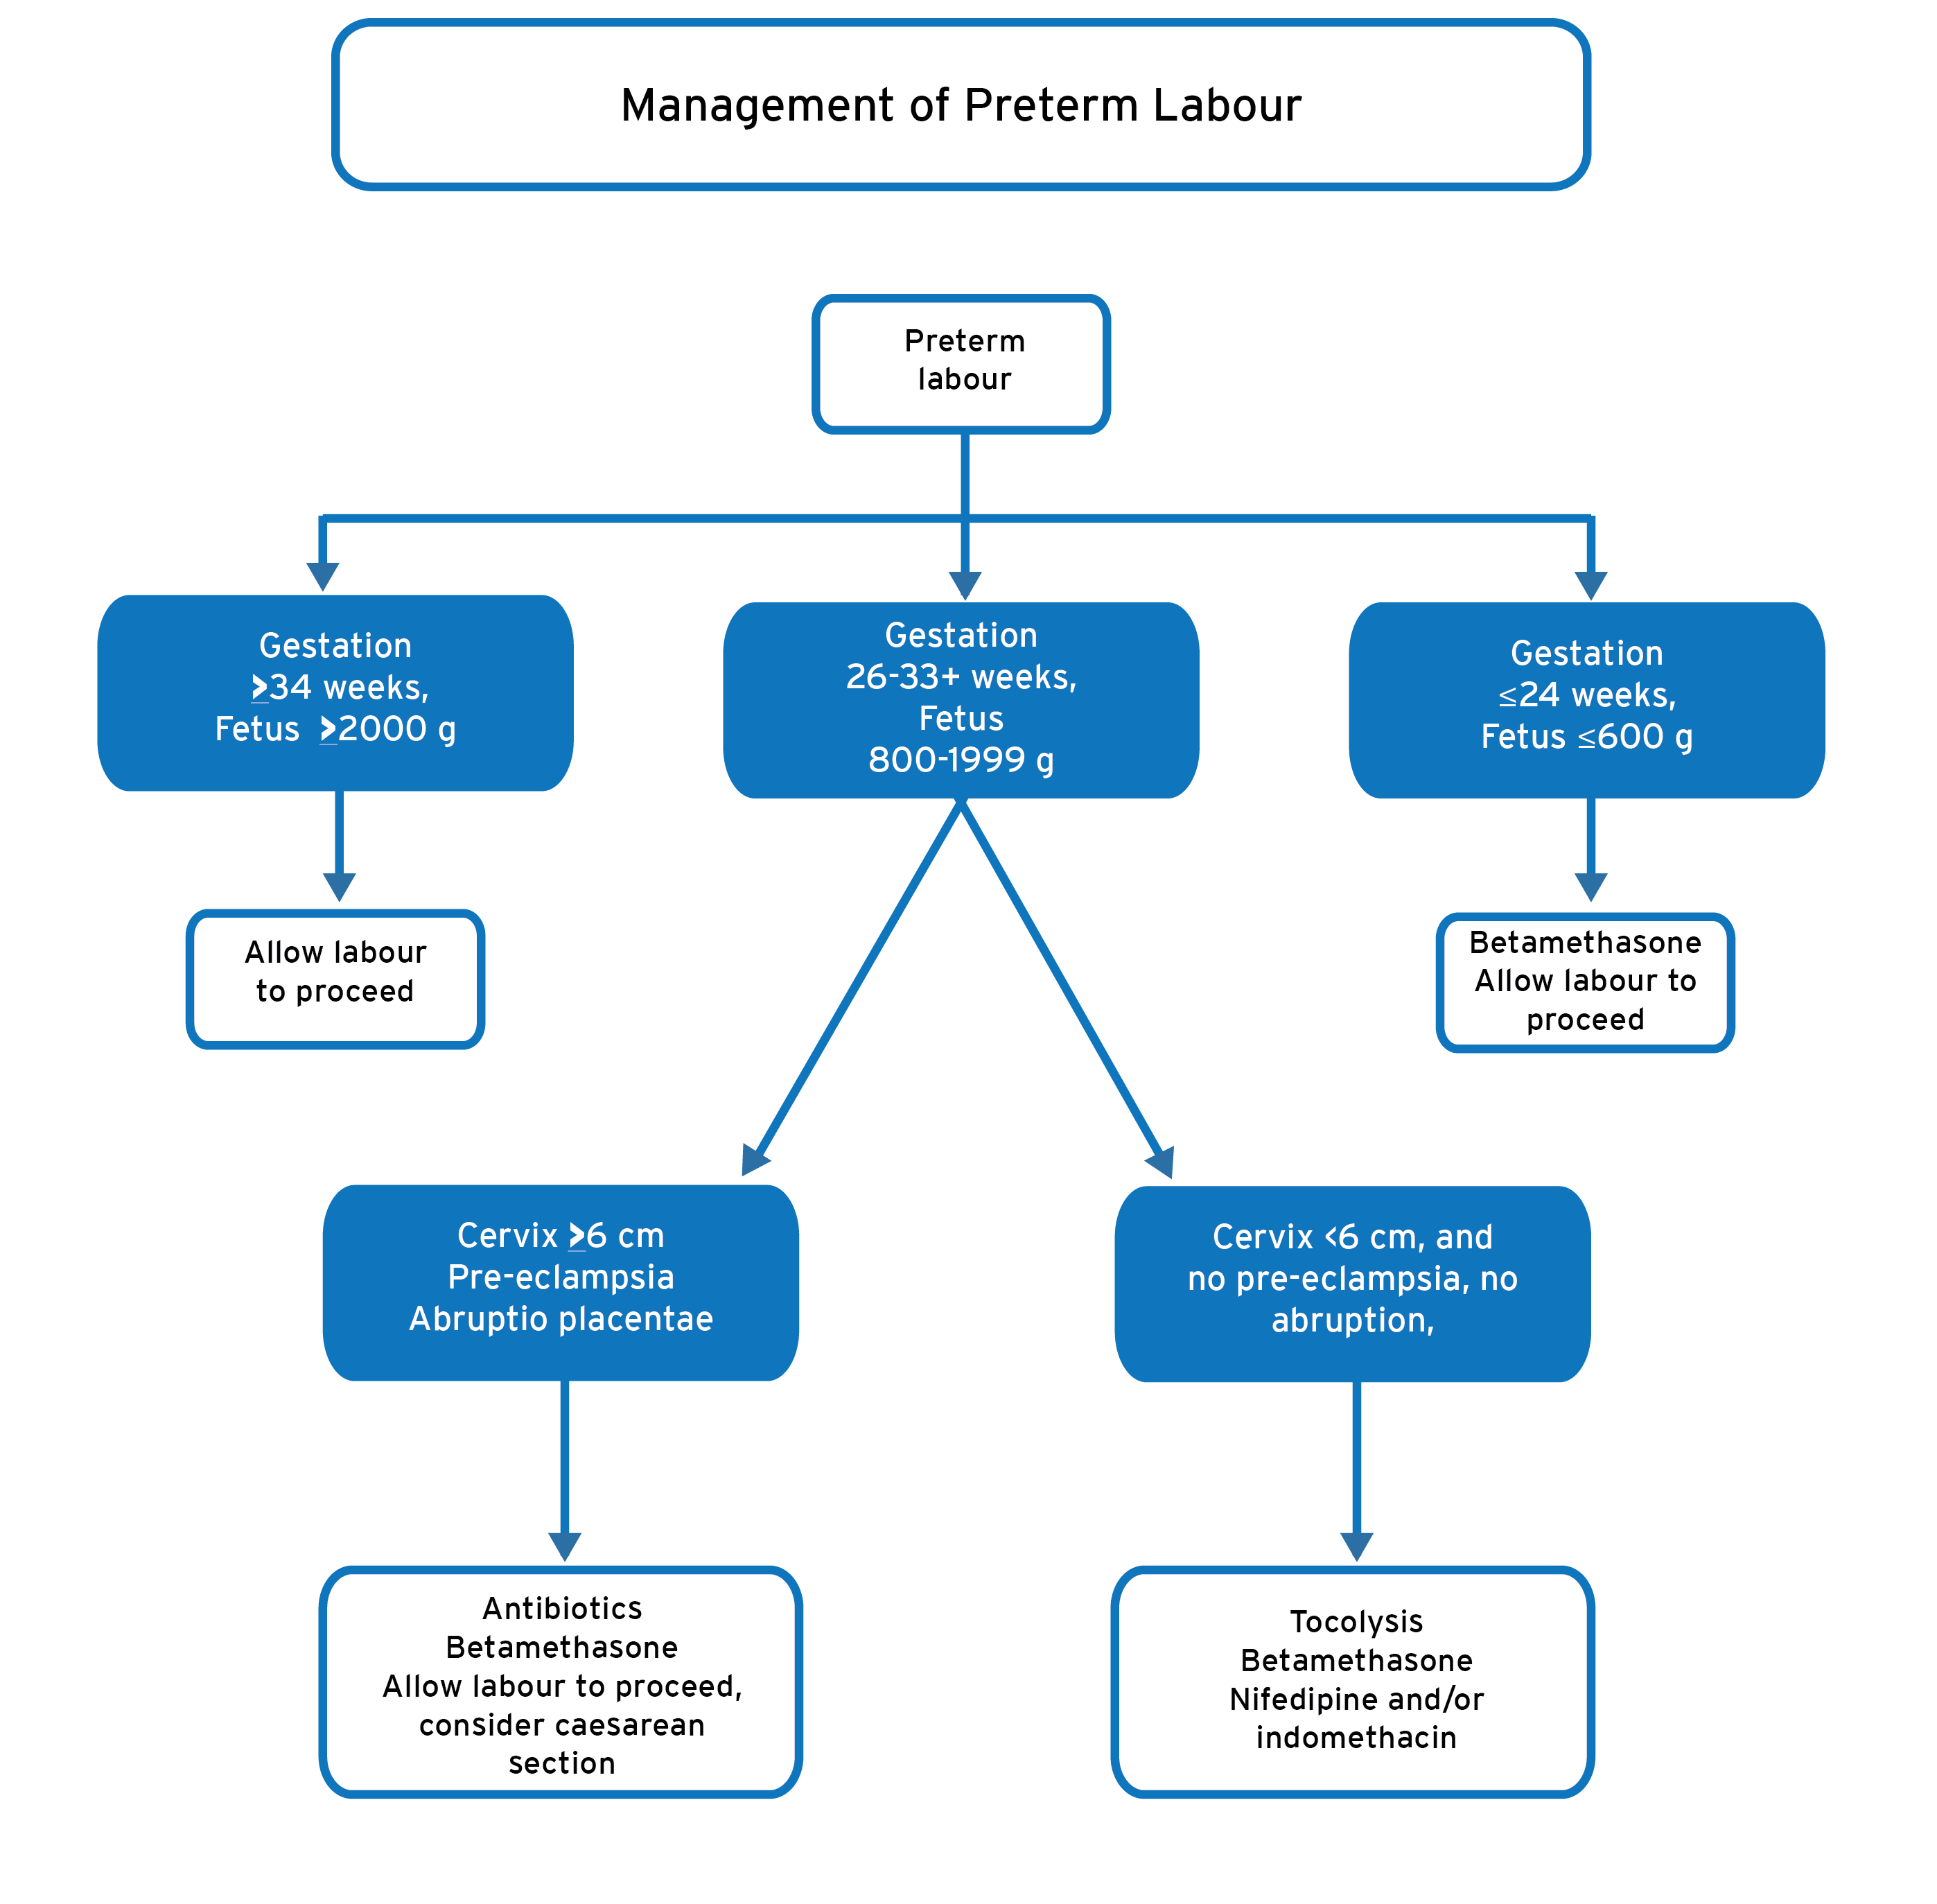
Management of preterm labour algorithm
This is defined as labour at <37 weeks. Management depends on the gestational age &/or estimated fetal weight. Most morbidity & mortality is related to delivery before 34 weeks. Ultrasound helps to assess fetal weight & normality.
Always consider & exclude underlying maternal illness, especially HIV related pneumonia, in women presenting with spontaneous preterm labour
Gestational age ≥34 weeks or estimated fetal weight ≥2 kg:
- Exclude & treat specific causes of preterm labour, e.g. chorioamnionitis or other infections (with fever & tachycardia), & abruptio placentae
- Admit to labour ward
- Manage labour as for term pregnancy
Gestational age 26-33+ weeks or estimated fetal weight 800 g – 1999 g:
- Admit to a high care area
- Give betamethasone 12 mg IM 12 hourly for 2 doses
- Run a CTG tracing
- With evidence of pre-eclampsia, abruptio placentae or chorioamnionitis, allow labour to proceed with continuous CTG, or consider caesarean section
- If the cervix is ≥6 cm dilated, allow labour to proceed
- If the cervix is <6 cm dilated, give nifedipine tocolysis regimen or indomethacin (below). Consider precautions & contraindications
- Intravenous atosiban may be available for certain patients (e.g. cardiac disease, multiple pregnancy), with consultant motivation
- If nifedipine fails to stop contractions, consider adding indomethacin (at <32 weeks)
- Deliver the baby slowly & gently, with an episiotomy if the perineum is tight
Gestational age 24+ weeks or estimated fetal weight 600+ g:
- Admit to labour ward
- Allow labour to proceed
- Give betamethasone 12 mg IM 12 hourly for 2 doses
- If the baby is born alive, transfer to the nursery for resuscitation
Gestational age ≤24 weeks, or estimated fetal weight ≤600 g:
- Manage as an inevitable miscarriage
- Counsel the woman appropriately
NIFEDIPINE TOCOLYSIS REGIMEN
- Insert a drip with Ringer-Lactate, & run 200 mL fast followed by 125 mL/hour
- Give nifedipine 20 mg orally, then 10 mg orally after 30 minutes if painful contractions persist. Follow with 10 mg orally every 6 hours if there are painful contractions, up to a maximum of 48 hours. Then allow labour to proceed, or discharge the woman if she is not in labour
Precautions
- Give oral nifedipine only in a high care area under close supervision
- Do not give nifedipine to women with cardiac disease, hypertension, hyperthyroidism, or uncontrolled diabetes mellitus. Indomethacin may be used in these women
- Do not give nifedipine to women with a heart rate ≥120/minute
- Observe the heart rate ½ hourly, or connect to a cardiac monitor
- Measure the BP hourly
INDOMETHACIN REGIMEN
- Give indomethacin 50 mg stat, then 25 mg orally 4 hourly for a maximum duration of 48 hours
- Do not give indomethacin to women with renal dysfunction, asthma, or a history of peptic ulceration
- Do not give indomethacin at ≥32 weeks
MANAGEMENT OF PRETERM LABOUR ALGORITHM