Prophylaxis for the HIV-Exposed Infant at Birth
The VTP strategies include timely HIV diagnosis, ART initiation and VL suppression in the mother (either pre- or post-conception) and the provision of HIV post-exposure prophylaxis to the infant. The mother’s response to ART by the time of delivery is measured by the delivery VL, which will also determine the risk profile of the infant at birth and, subsequently, the infant’s ART prophylaxis regi
The VTP strategies include timely HIV diagnosis, ART initiation and VL suppression in the mother (either pre- or post-conception) and the provision of HIV post-exposure prophylaxis to the infant. The mother’s response to ART by the time of delivery is measured by the delivery VL, which will also determine the risk profile of the infant at birth and, subsequently, the infant’s ART prophylaxis regimen. While awaiting the delivery VL result, all infants should, in the meantime, receive dual prophylaxis (NVP & AZT) until the VL result can be reviewed. If the mother-baby pair have already been discharged, this may be at the 3-6 day postnatal visit at the clinic. Clinicians working in postnatal clinics should therefore check the results of delivery VL. If the baby is still admitted to hospital, ward staff should ensure that the results are checked. Once the result of the delivery VL is known, prophylaxis should be adjusted accordingly.
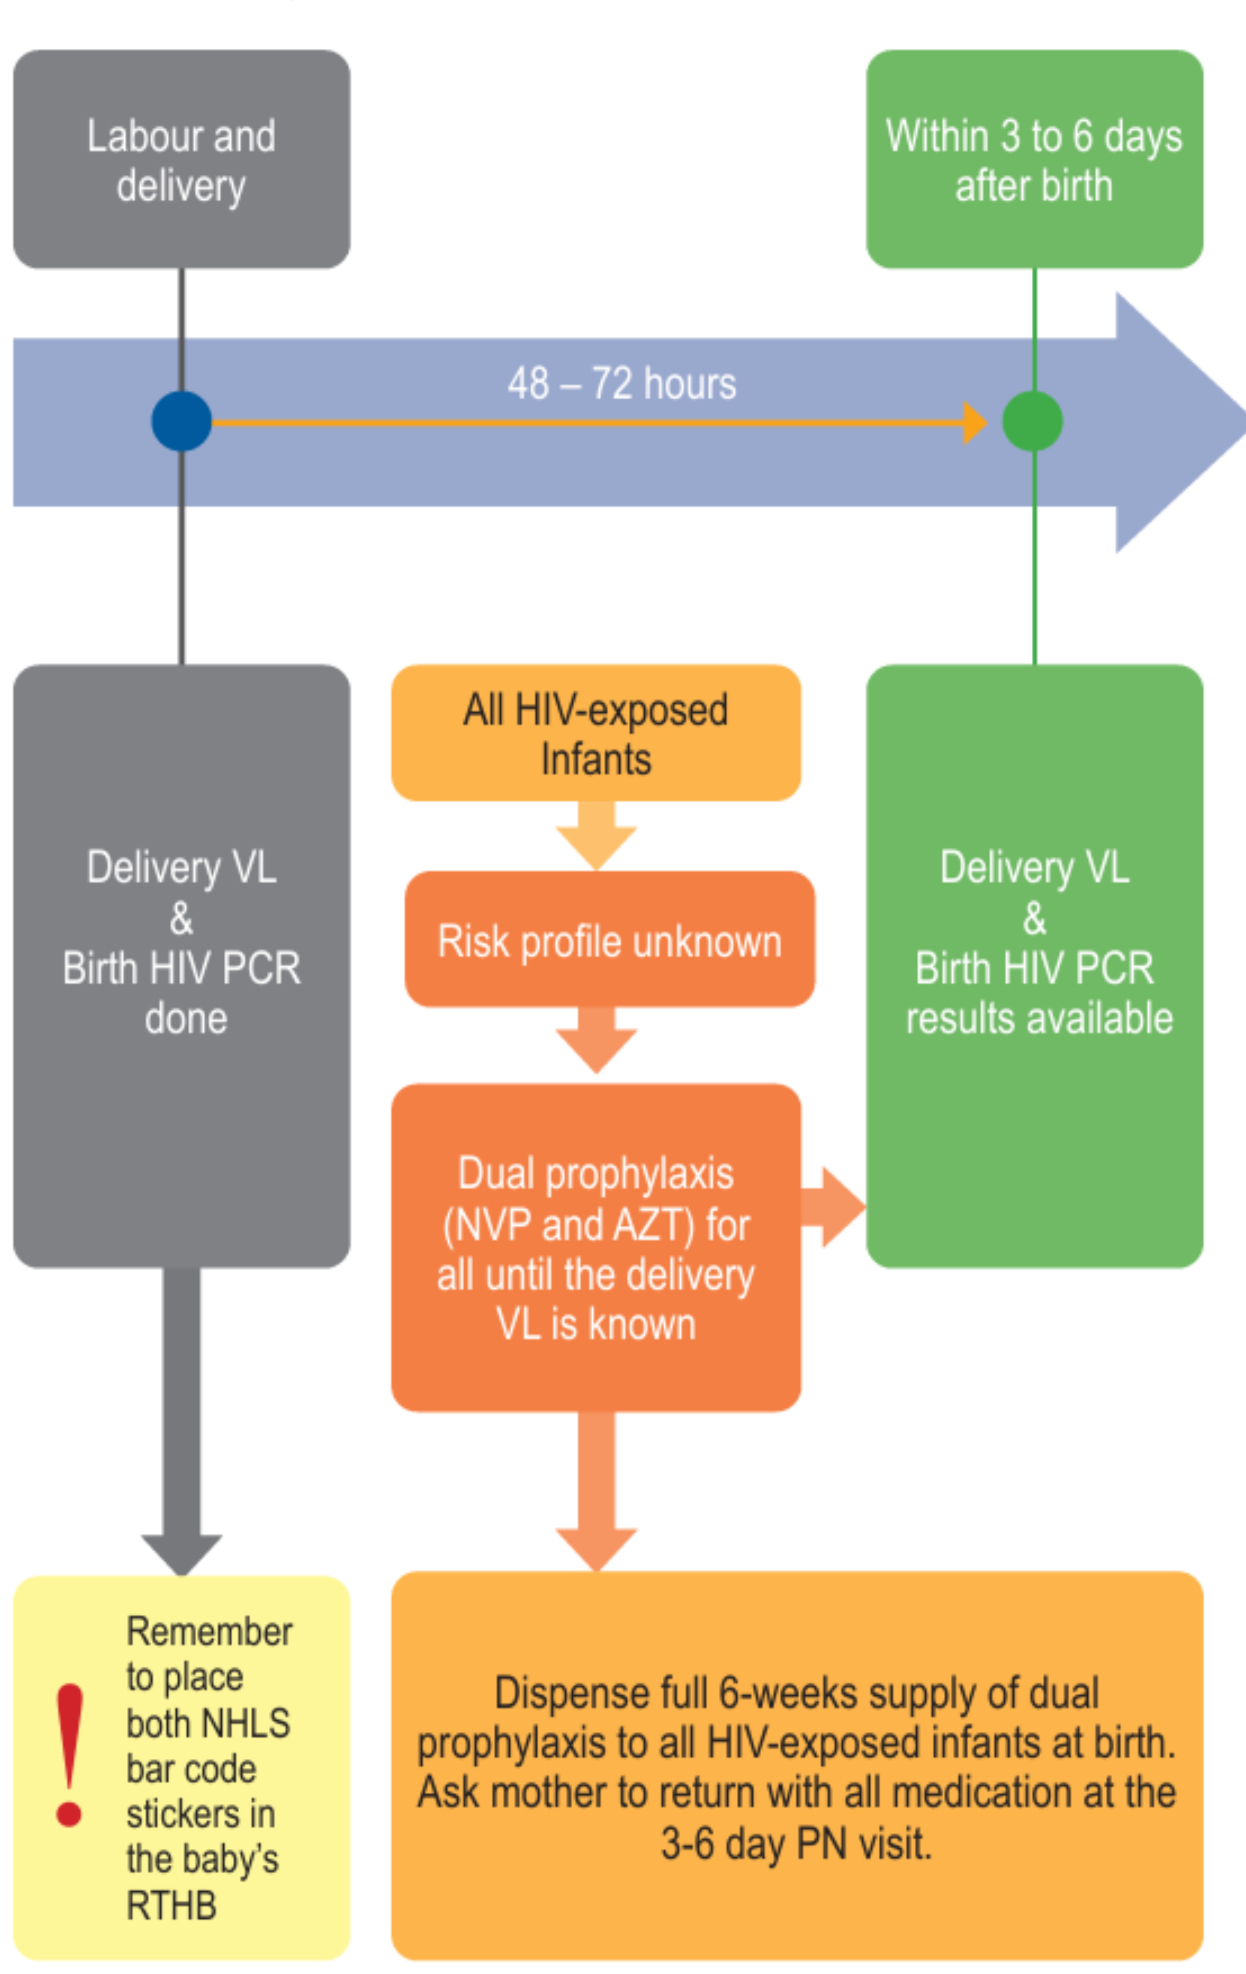
Click on the image you enlarge.
| Reclassify risk profile | |||
| Maternal Delivery VL * | Classification | Prophylaxis | Comment |
| Delivery VL< 50 copies/mL regardless of feeding choice | Low risk | Change to low-risk prophylaxis - Stop AZT - NVP daily for six weeks. |
- Affirm and encourage good adherence. - Repeat maternal VL 6 monthly during breastfeeding. - Do all routine HIV tests for HIVexposed infants as indicated on “HIV Testing For The HIV-Exposed Infant” |
| Delivery VL ≥ 50 copies/mL in a breastfeeding mother** | Higher risk | Continue dual prophylaxis: - AZT twice daily for six weeks. - NVP daily for a minimum of 12 weeks. |
- Do an ABCDE assessment and intervention as a matter of urgency to achieve a suppressed VL in the mother as soon as possible. Follow the “VL NonSuppression Algorithm”. - Stop infant NVP only after confirmation of maternal VL being less than 50 c/mL, or until four weeks after cessation of all breastfeeding. - Do all routine HIV tests for HIV exposed infants as indicated on “HIV Testing For The HIV-Exposed Infant". |
| Delivery VL ≥ 50 copies/mL in a mother who is exclusively formula feeding her infant from birth | Higher risk | Continue dual prophylaxis: - AZT twice daily for six weeks. - NVP daily for six weeks. |
- Do an ABCDE assessment and intervention as a matter of urgency to achieve a suppressed VL in the mother as soon as possible. Follow the “VL Non-Suppression Algorithm”. - Do all routine HIV tests for HIV-exposed infants as indicated on “HIV Testing For The HIV-Exposed Infant”. |
| Birth PCR positive | HIV infected | Stop any NVP and AZT prophylaxis. Initiate ART. Confirm the positive result with a 2nd PCR on a new sample. Start cotrimoxazole prophylaxis therapy (CPT) at 6 weeks of age. |
|
* All women known to be living with HIV should have a VL at delivery. This includes women who are newly diagnosed during labour, newly initiating ART, or re-initiating ART
** Breastfeeding includes exclusive breastfeeding or mixed feeding
South African National Department of Health, Guideline for Vertical Transmission Prevention of Communicable Infections, Version 2_August 2023