Protocol for Management of a Small for Gestational Age (SGA) Fetus with Normal Umbilical Artery Doppler (UAD)
Protocol for Small for Gestational Age (SGA) Fetus with Normal Umbilical Artery Doppler (UAD)
Verify SGA diagnosis and appropriate protocol application
Advice and Ongoing surveillance
Recommended biometry reference charts
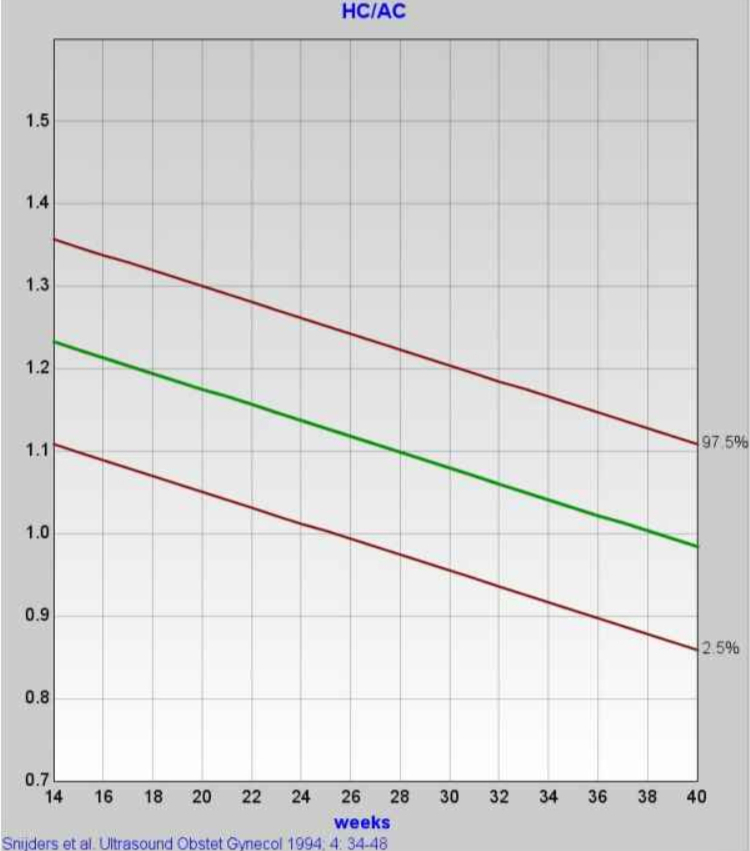
Recommended HC/AC ratio reference chart
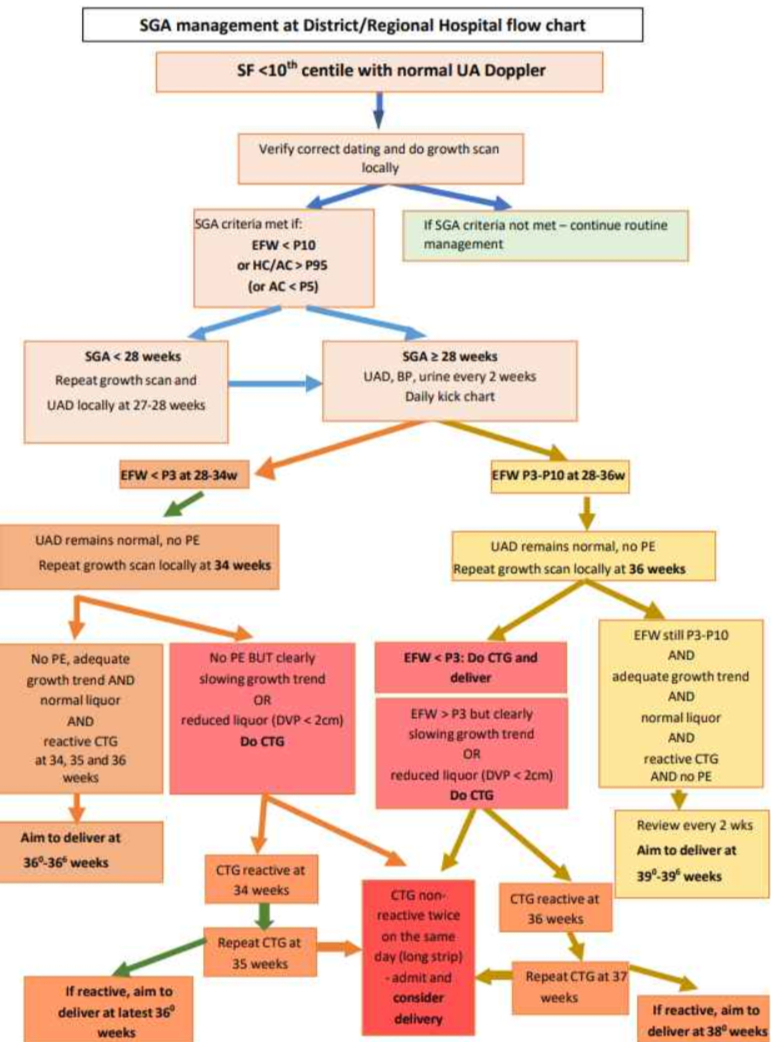
SGA management at District/Regional Hospital flow chart
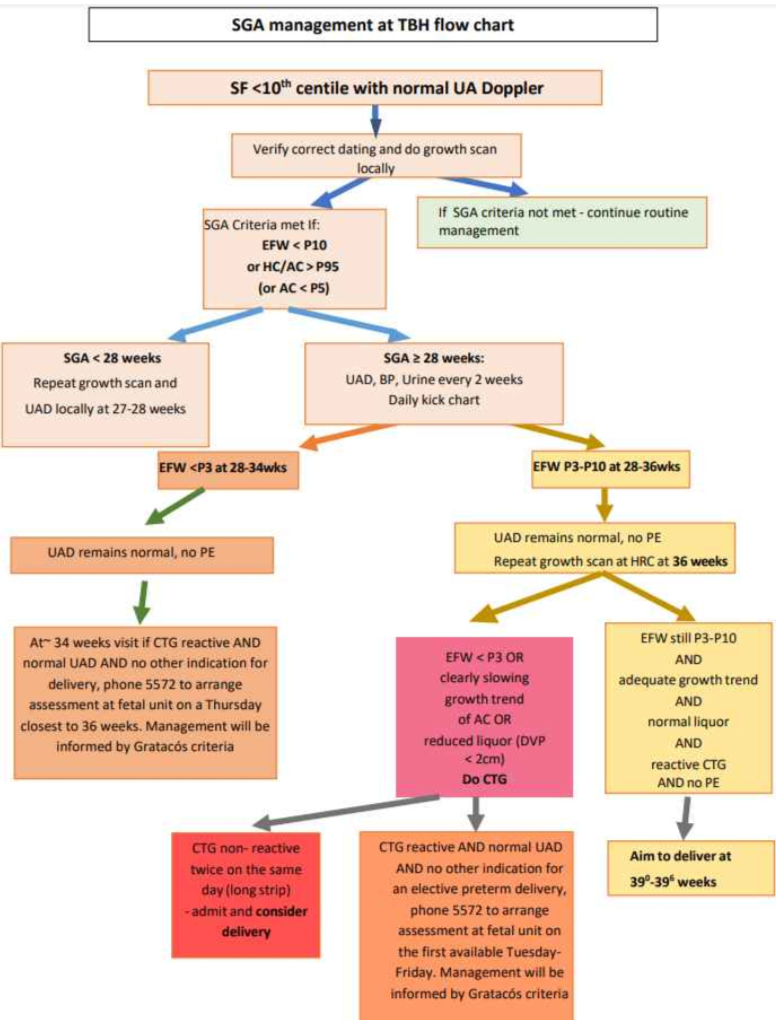
SGA management at TBH flow chart
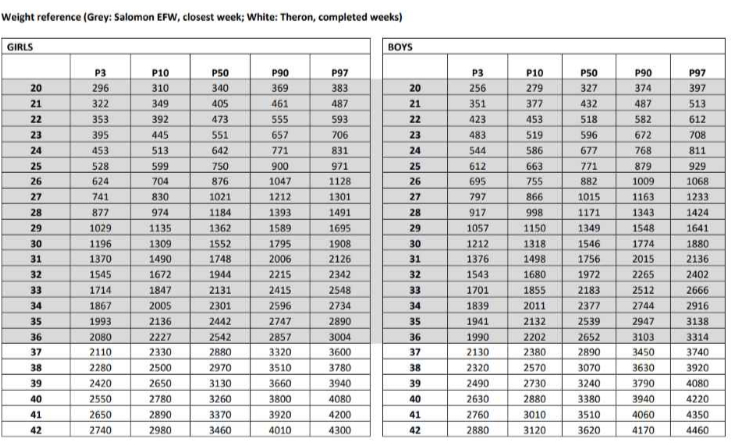
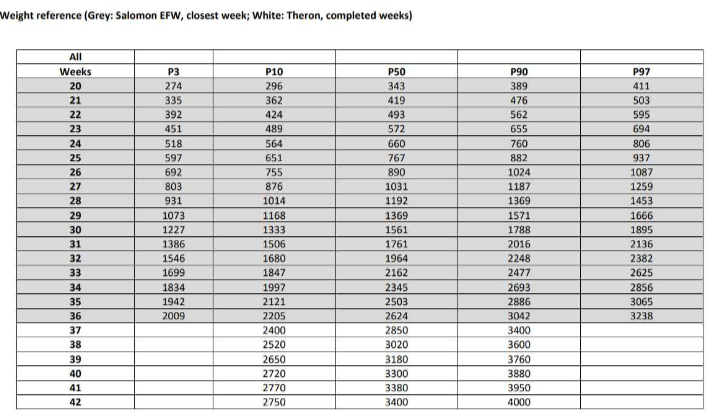
Weight reference (Grey: Salomon EFW, closest week; White: Theron, completed weeks)
Weight reference (Grey: Salomon EFW, closest week; White: Theron, completed weeks)
*SGA: small for gestational age; UAD: umbilical artery doppler
Clinical problem: SF growth <10th centile (with previously normal growth) and/or plateau of growth and/or growth crossing centiles in otherwise uncomplicated pregnancy
If clinical suspicion of SGA at community clinic (MOU/BANC+): refer to closest ultrasound service/district/regional hospital doctor’s clinic
A. Verify SGA diagnosis and appropriate protocol application
- Verify correct dating (correlate with history, first scan)
- Perform growth scan including liquor volume [deepest vertical pool (DVP)] and UAD
- Plot ultrasound biometry, estimated fetal weight and UAD on graphs for correct gestation
- If the ultrasound findings are in keeping with a definition of SGA (current EFW < P10 OR HC/AC* >2 standard deviations (P>97.5); OR AC < P5 if head measurements difficult for the correct gestation), further management must remain at the district/regional hospital and this protocol applies
- Biometry and weight reference ranges: recommended table and graphs attached *HC/AC ratio is increased with asymmetrical growth, which is the more concerning form of SGA
B. Protocol Exclusions
- If not SGA on ultrasound as defined above, this protocol does not apply, and the patient can be referred back to her clinic. An UAD between P75 and P95 needs to be repeated 2 weeks later.
- If UAD > 95th centile, this protocol does NOT apply. Kindly follow the protocol for abnormal UAD (regardless of growth centile).
C. Advice and Ongoing surveillance
- Advise on cessation of smoking, alcohol, etc.
- Rule out pre-eclampsia (PE) at least every two weeks
- Once viable, instruct mother on daily kick count chart
- SGA pregnancies are at risk of term (rarely preterm) intra-uterine fetal demise (IUFD), fetal distress in labour and pre-eclampsia
- These risks are not contra-indications to vaginal delivery, but requires continuous CTG monitoring throughout labour
Management:
- SGA < 28 weeks:
- Repeat growth scan + UAD at 27-28 weeks (unless done in last 3 weeks)
- SGA ≥ 28 weeks:
- Repeat UAD and vitals every two weeks [TBH-patients at Fetal Evaluation clinic (FEC)] and manage accordingly if it becomes abnormal
- If EFW < P3 at 28-34 wks and UAD remains normal AND no PE:
- Repeat growth scan locally at 34 weeks (if at least two weeks from previous EFW), incl. EFW, DVP (Plot Size and UAD on graphs for correct gestation) continue with visits as below:
Assessment at/after 34 weeks: management at district/regional hospitals:
- No PE AND adequate growth trend AND normal liquor AND reactive CTG (at 34, 35 and 36 weeks) aim to deliver at 360-366 weeks
- No PE but clearly slowing growth trend OR reduced liquor (DVP < 2cm) BUT CTG reactive – repeat CTG at 35 weeks – aim to deliver no later than 360 weeks
- No PE but CTG non-reactive twice on same day (long strip at least 40-50 minutes) – admit and consider delivery unless the CTG becomes reactive. Make sure patient is at the correct level of care for the anticipated GA at delivery and anticipated birthweight.
Assessment at/after 34 weeks: management at TBH:
- Follow up weekly at HRC to exclude PE and for CTG at FEC
- If weekly CTG reactive AND no other indication for delivery: Phone 5572 at the ~34 week visit to arrange a formal fetal medicine reassessment on a Thursday closest to 36 weeks – management will be planned according to Gratacós criteria.
- If EFW P3-10 at 28-36wks and UAD remains normal AND no PE
- Repeat growth scan and CTG at 36 weeks, incl. EFW, DVP
Management at district/regional hospitals:
- If EFW at 36 weeks remains > P3 AND adequate growth trend AND normal liquor AND reactive CTG AND no PE – aim to deliver at 390-396 weeks (the diagnosis is SGA and not fetal growth restriction (FGR)).
- If no PE but EFW at 36 weeks is clearly showing slowing growth trend (but still above P3) OR reduced liquor (DVP < 2cm):
- CTG reactive – repeat CTG at 37 weeks – aim to deliver at 380 weeks
- CTG non-reactive twice on same day – admit and consider delivery
- If EFW at 36 weeks is < P3: admit and consider delivery.
Management at TBH:
- If no PE AND EFW at 36 weeks remains > P3 AND adequate growth trend of AC AND normal liquor AND reactive CTG – aim to deliver at 390-396 weeks (this is SGA and not FGR).
- If no PE but EFW at 36 weeks is < P3 OR clearly slowing growth trend of AC OR reduced liquor (DVP < 2cm): perform CTG
- CTG persistently non-reactive – consider delivery
- CTG reactive AND no other indication for an elective preterm delivery: Phone 5572 to arrange a formal reassessment on the first available Tuesday-Friday. Management will be informed by the Gratacós criteria.
Recommended biometry reference charts
Biparietal diameter graph:
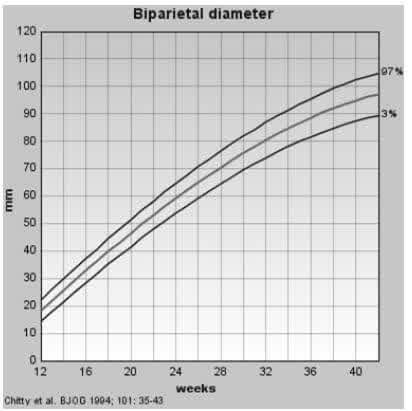
Click on the image to enlarge
Head Circumference Graph:
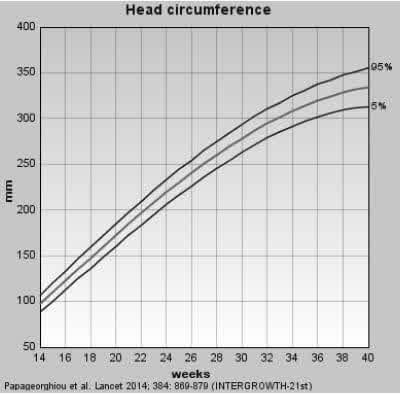
Click on the image to enlarge
Femur Length Graph:
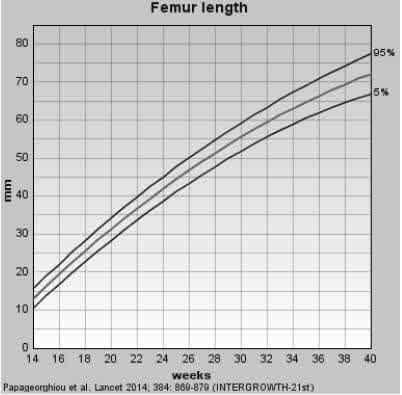
Click on the image to enlarge
Abdominal Circumference Graph:
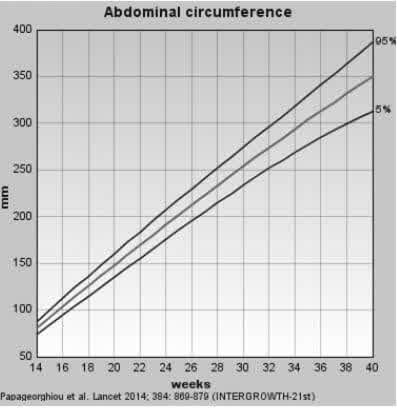
Click on the image to enlarge
Recommended HC/AC ratio reference chart
Click on the image to enlarge
SGA management at District/Regional Hospital flow chart
Click on the image to enlarge
SGA management at TBH flow chart
Click on the image to enlarge
Weight reference (Grey: Salomon EFW, closest week; White: Theron, completed weeks)
Click on the image to enlarge
Weight reference (Grey: Salomon EFW, closest week; White: Theron, completed weeks)
Click on the image to enlarge
Click here to open the above content in the original PDF view
Tygerberg Hospital, Department of Obstetrics and Gynaecology; Protocol for management of an SGA fetus with normal UAD at TBH and District/Regional Hospitals; Version: October 2022; Last checked for updates by EMGuidance: Oct 2023