Termination of Pregnancy (TOP)
Summary of Choice of Termination of Pregnancy Act of 1996 TOP: Management of pregnancies up to the twelfth week of gestation (12 weeks and 0 days) TOP: From the thirteenth week (12 weeks and 1 day) up to the the twentieth week (20 weeks and 0 days) Referral Early ultrasound examination is more accurate than last normal menstrual period at determining gestational age and is also useful in identify
Summary of Choice of Termination of Pregnancy Act of 1996
TOP: Management of pregnancies up to the twelfth week of gestation (12 weeks and 0 days)
Early ultrasound examination is more accurate than last normal menstrual period at determining gestational age and is also useful in identifying ectopic-, molar-, or twin pregnancies.
The clinical management for all pregnancies up to 14 weeks can be done as outpatient procedures. From 14 weeks onwards, TOP should be done in a medical facility. Note that the gestational ages used for clinical management differ from the legal cut-offs, e.g. a patient at 12 weeks and 1 day will meet the legal requirements as described in the act for TOP after 12 weeks, but the clinical management is the same as for a pregnancy from day one up to 14 weeks (see below). The legal criteria for TOP follow below.
Summary of Choice of Termination of Pregnancy Act of 1996
Women eligibility
Up to 12 completed weeks and 0 days: On request.
From the thirteenth week (12 weeks and 1 day) up to the twentieth week (20 weeks and 0 days): “If the doctor is of the opinion that i) the pregnancy resulted from rape or incest, ii) there is substantial risk of severe fetal physical or mental abnormality, iii) the continued pregnancy poses a risk to mother's physical or mental health, or social/economic circumstances".
More than 20 weeks (≥ 20 weeks 1 day): “If the doctor, after consulting with a second doctor or registered midwife, is of the opinion that continued pregnancy i) would endanger the mother's life, or ii) would result in risk of injury or severe malformation to the fetus"
Venue
An accredited facility with staff trained in performing TOP, designated by the Member of Executive Council at provincial level. A facility with a 24-hour maternity service does not require specific designation - The Choice on Termination of Pregnancy Act, 1996 (as amended by Act 38 of 2004), expands access to TOP services, allowing registered nurses, as well as registered midwives, to perform TOPs up to the twelfth week of pregnancy.
Practitioner
Up to 12 weeks and 0 days: Doctor, midwife, or registered nurse with appropriate training.
From the thirteenth week (12 weeks and 1 day) up to the twentieth week (20 weeks and 0 days): Doctor responsible for decision and prescription of medication; registered nurse/midwife may administer medication according to prescription.
Note:
- Pre-and post-termination counselling and contraceptive counselling is essential.
- Consent of spouse/partner is not necessary.
- Consent for TOP and related procedures e.g. laparotomy may be given by minors. Minors are encouraged to consult parents or others, but consent is not mandatory.
TOP: MANAGEMENT OF PREGNANCIES UP TO THE TWELFTH WEEK OF GESTATION (12 WEEKS AND 0 DAYS)
ICD-10 code: O04.9/O06.9
GENERAL MEASURES
- Counselling.
- Outpatient procedure by nursing staff with specific training.
- Discuss TOP options with patient: Medical TOP or manual vacuum aspiration of the uterus.
MEDICINE TREATMENT
Medical TOP:
(Up to 12 weeks and 0 days)
- Mifepristone, oral, 200 mg, immediately as a single dose.
Followed 1-2 days later by:
- Misoprostol, PV/SL/buccal, 800 mcg by self-administration
- If expulsion has not occurred 4 hours after misoprostol administration, a second dose of misoprostol 400 mcg may be given.
Note:
Bleeding may persist for up to 1 week. If there is no bleeding after the second dose of misoprostol, the woman must return to the facility as soon as possible as there is a possibility of an incomplete procedure or ectopic pregnancy.
For pain:
- Paracetamol, oral, 500mg-1 g, 4–6 hourly as required (to a maximum of 4g in 24 hours).
- Maximum dose: 15 mg/kg/dose.
ADD
After expulsion is complete:
- NSAID, e.g.:
- Ibuprofen, oral, 400 mg 8 hourly with or after a meal.
Manual vacuum aspiration:
- Misoprostol, PV, 400 mcg 3 hours before routine vacuum aspiration of the uterus.
Routine analgesia for vacuum aspiration:
- Morphine, IM, 0.1 mg/kg 30 minutes before aspiration procedure, to a maximum of 10 mg.
Do not give intravenous benzodiazepines and parenteral opioid analgesics concurrently.
Alternatively, consider a paracervical block:
- Use Lidocaine 1%. (Without adrenaline)
- Draw up lidocaine 1% in a 20 mL syringe.
- Attach a 20-gauge spinal needle. Inject 2 mL superficially in the cervix at 12h00 and immediately grab the cervix with a tenaculum at 12h00 to stabilise cervix.
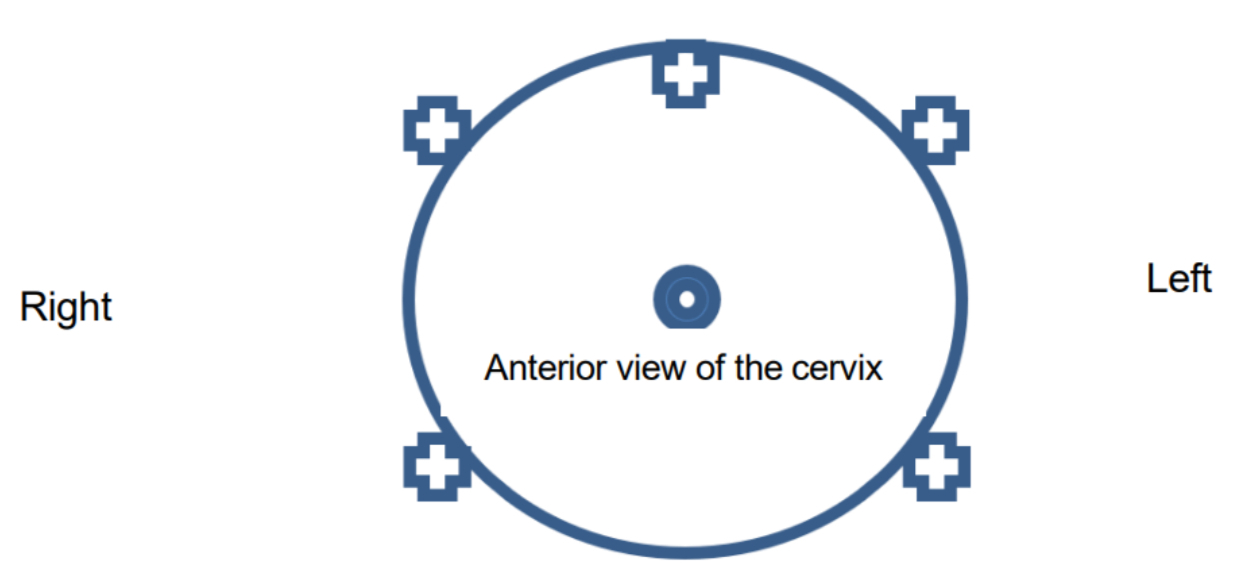
- Inject remaining 18 mL slowly over 60 seconds into the cervicovaginal junction in four equal doses of 4–5mL at 2, 4, 8, and 10 o’clock (see Figure 5.1: Anterior view of the cervix).
- This injection is continuous from superficial to deep (a depth of 3 cm) and again to superficial (injecting with insertion and withdrawal).
- Manual vacuum aspiration can start after 3 minutes.
Figure 5.1: Anterior view of the cervix
Click on image to enlarge
Oral analgesia as required for 48 hours:
- Paracetamol, oral, 500mg-1 g, 4–6 hourly as required (to a maximum of 4g in 24 hours).
- Maximum dose: 15 mg/kg/dose.
AND
- NSAID, e.g.:
- Ibuprofen, oral, 400 mg 8 hourly with or after a meal.
TOP: FROM THE THIRTEENTH WEEK (12 WEEKS AND 1 DAY) UP TO THE TWENTIETH WEEK (20 WEEKS AND 0 DAYS)
ICD-10 code: O04.9/O06.9
GENERAL MEASURES
- Medical TOP: From 12 weeks onwards, this should be performed as an inpatient with 24-hour services and facilities for general anaesthesia, as there is a greater risk for bleeding or a need for surgical completion of the procedure.
- Manual vacuum aspiration can be performed up to 14 weeks. Dilation and sharp curettage (D&C) are not recommended and should preferably be replaced by vacuum aspiration.
- Surgical TOP (Dilatation and Evacuation procedure after cervical preparation) can be done by specially trained providers as a day theatre procedure after 14 weeks.
MEDICINE TREATMENT
Medical TOP:
- Mifepristone, oral, 200 mg, oral, immediately as a single dose.
Follow 1-2 days later with:
- Misoprostol, PV/SL/buccal, 400 mcg, every 3 hours until TOP occurs.
Analgesia:
- Morphine, IM, 0.1 mg/kg 4 hourly or as needed, to a maximum of 10 mg.
If Rh-negative:
ICD-10 code: O36.0
- Anti-D immunoglobulin, IM, 100 mcg as a single dose.
Contraception:
Counsel all women on effective contraception, especially long-acting reversible methods. All methods can be given at the time of the procedure, except for an IUCD after a medical TOP. IUCD may be inserted after medical TOP if reasonably certain that individual is no longer pregnant.
Note:
Medical TOP should be followed by manual vacuum aspiration of the uterus if expulsion of products of conception is not complete.
Cervical preparation for manual vacuum aspiration or surgical TOP:
- Misoprostol PV/SL, 400 mcg, 2 to 3 hours prior to the procedure.
REFERRAL
- Complicating medical conditions, e.g. cardiac failure, etc.
- Failed procedure.
- Ectopic pregnancy.
Standard Treatment Guidelines and Essential Medicines List for South Africa Adult Hospital _Chapter 5: Gynaecology; Version 1.0, 2020-4_June 2024