Aggressive Disruptive Behaviour in Adults
Description General Measures Medicine Treatment Referral ICD-10 code: R45.1/R45.4-6 Description Agitation may escalate to overt aggression and often manifests with restlessness, pacing, and loud or demanding speech. Aggressive behaviour includes verbally abusive language, specific verbal threats, intimidating physical behaviour, and/or actual physical violence to self, others, or property. All ag
ICD-10 code: R45.1/R45.4-6
Description
Agitation may escalate to overt aggression and often manifests with restlessness, pacing, and loud or demanding speech. Aggressive behaviour includes verbally abusive language, specific verbal threats, intimidating physical behaviour, and/or actual physical violence to self, others, or property. All agitation and aggression must be considered an emergency, and violence should be prevented or minimised wherever possible. Causes for aggressive, disruptive behaviour include:
- Physical: acute medical illness, delirium and its causes (See: Delirium), epilepsy (pre-, intra-, and post-ictal), intracerebral lesions, traumatic brain injury.
- Psychiatric: psychosis, mania, agitated depression, neurocognitive disorders (e.g. dementias, traumatic brain injury), developmental disorders (e.g. intellectual disability and autistic spectrum disorder – See: Special considerations - Intellectual disability), severe anxiety.
- Substance misuse: alcohol, cannabis, methaqualone (mandrax) intoxication or withdrawal, stimulant (cocaine, methamphetamine [tik], methcaninone [cat] intoxication, benzodiazepine withdrawal.
- Psychological factors: high levels of impulsivity and antagonism, hypersensitivity to rejection or insult, poor frustration tolerance, and maladaptive coping skills may contribute to aggression and rage.
CAUTION
- Psychiatric and intellectually disabled patients often have medical conditions, trauma, and substance misuse.
- Do not assume aggressive behaviour is due to mental illness or psychological factors.
General Measures
- Be prepared:
- Be aware of high-risk patients e.g. those known with previous violence, substance misuse, State patients.
- Have a step-wise protocol available to ensure safety of the patient and all in the clinic.
- Establish clear roles for all staff members.
- Have a triage plan for early signs of aggression.
- Have available backup – security, SAPS, and Emergency Medical Service (EMS).
- Prepare a designated calming area – suitable for regular monitoring.
- De-escalate and contain:
- Be calm, confident, kind and reassuring. Listen to the patient.
- Maintain a submissive posture with open hands; do NOT turn your back.
- Do NOT argue, confront delusions, or attempt to touch the patient.
- Be vigilant for delirium, medical, and other causes while calming the patient.
- Manual restraint:
- Manual restraint refers to interventions done with hands or bodies without the use of any device, to limit a user's movement of body or limb. It is sometimes called “holding”.
- May be necessary to administer medication – must be respectful, controlled, kept to a minimum, and should preferably be applied by personnel of the same sex as the patient.
- Report any injuries or death associated with the restraint to the Mental Health Review Board and health facility quality assurance department.
- Mechanical restraint:
- Only use when absolutely necessary to protect the patient and others in an acute setting for as short a period of time as possible and as prescribed by a doctor. See national policy guidelines: https://www.knowledgehub.org.za/elibrary/policyguidelines-seclusion-and-restraint-mental-health-care-users-2012
- Record type, sites, and duration of any restraints used, with 15-minute monitoring of vital signs, mental state, restraint sites, and reasons for use.
- For people managed under the MHCA, complete and submit MHCA Form 48, along with reports of any injuries or death incurred, to the Mental Health Review Board and health facility quality assurance department.
- Pregnant women:
- Never leave unattended.
- Use restraint sparingly and with care, with mother in a supported, semi-seated position (not supine or prone).
- Counsel the family/friend/patient escort regarding:
- Possible causes for the behaviour.
- Reasons for restraints if used.
- Importance of their continued support of the patient after hospital discharge.
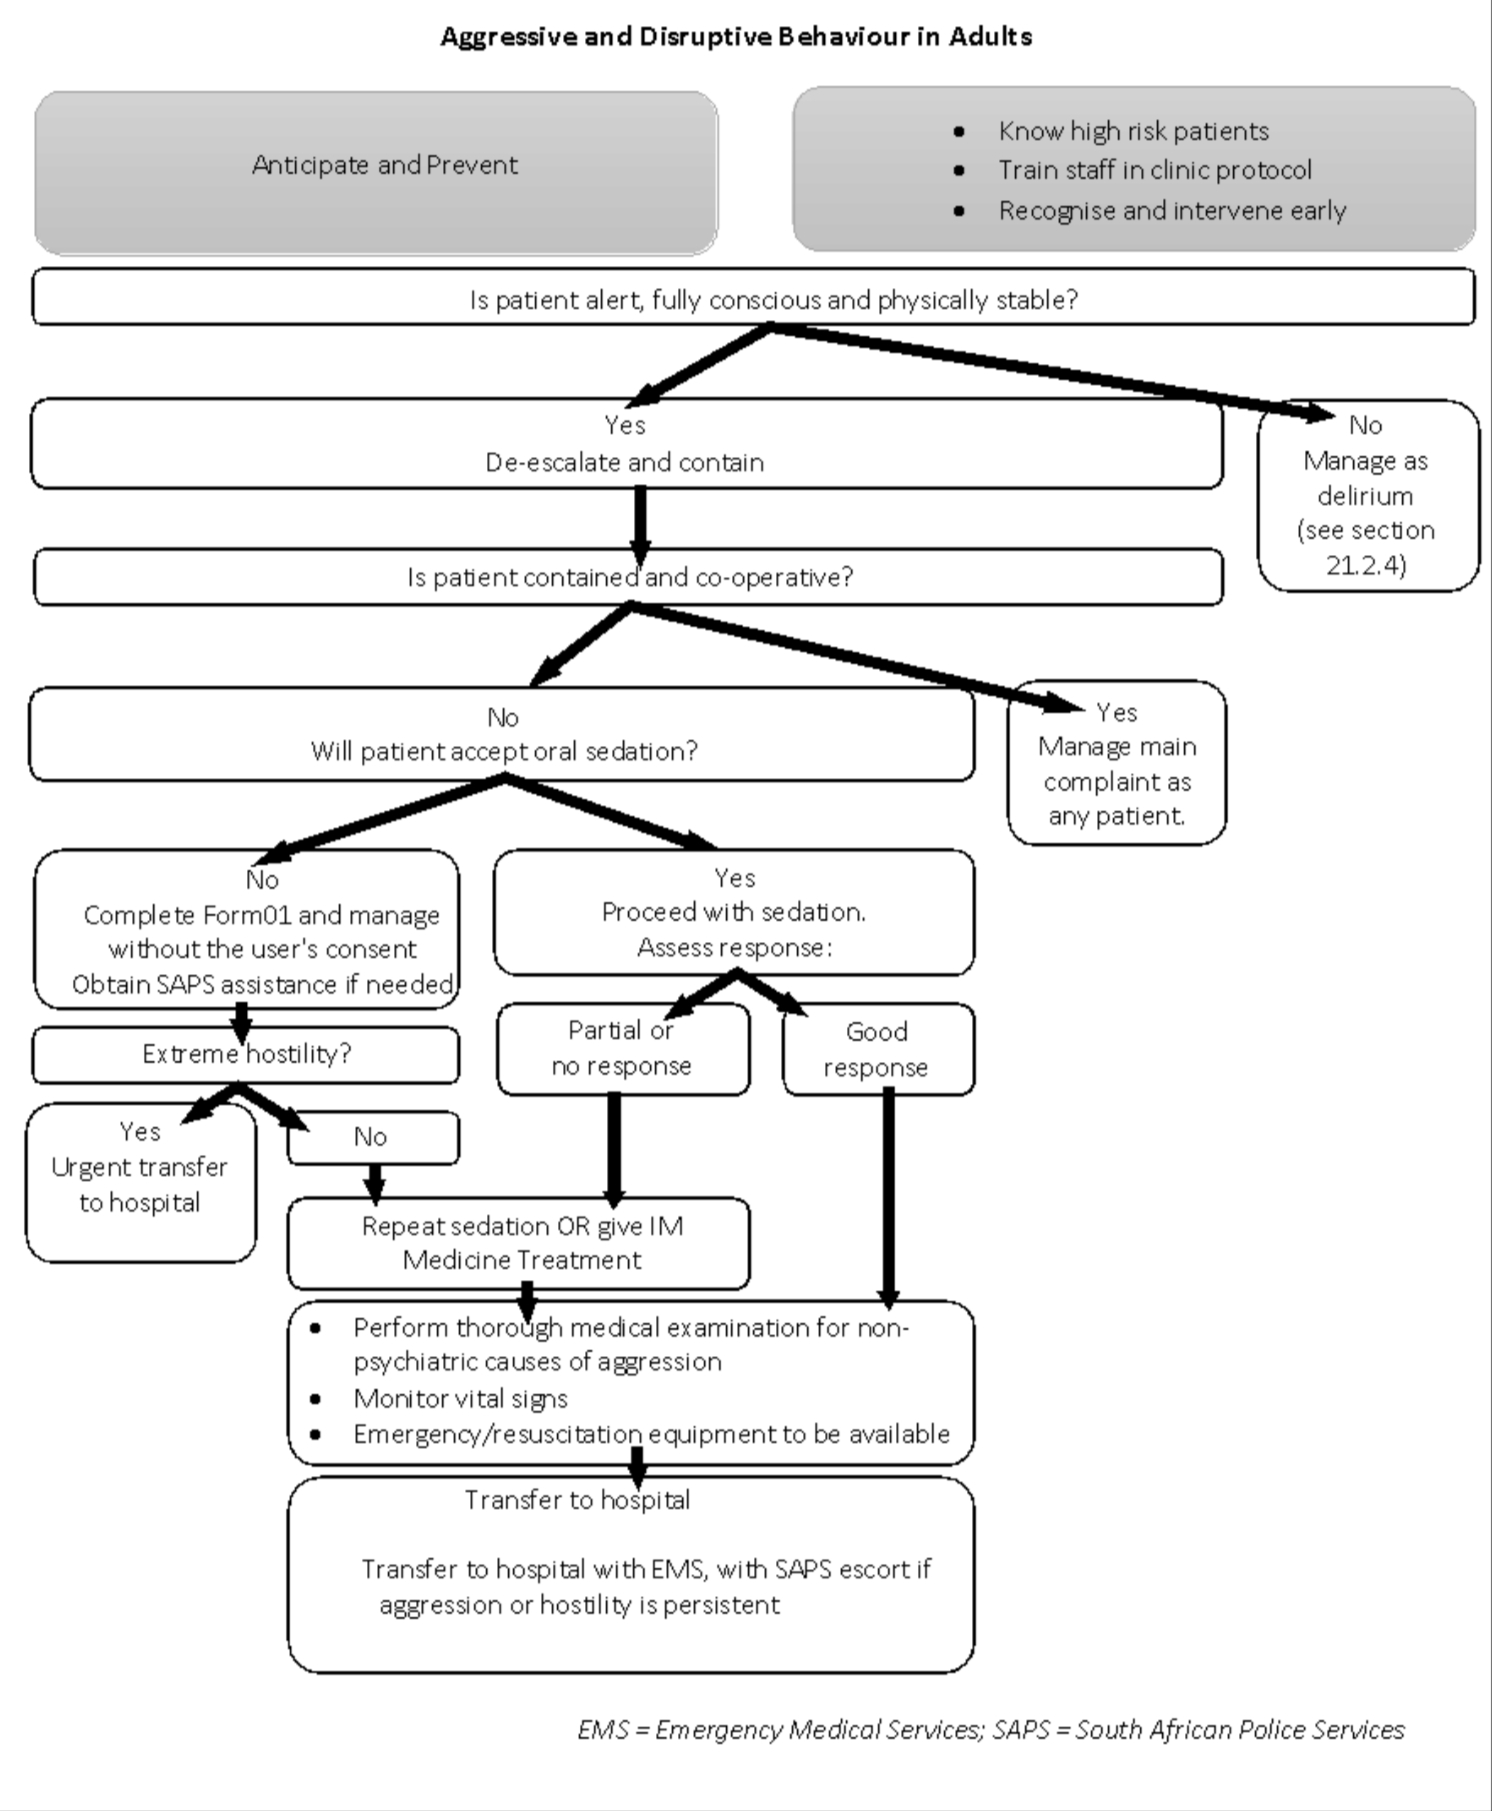
Click on the image to enlarge
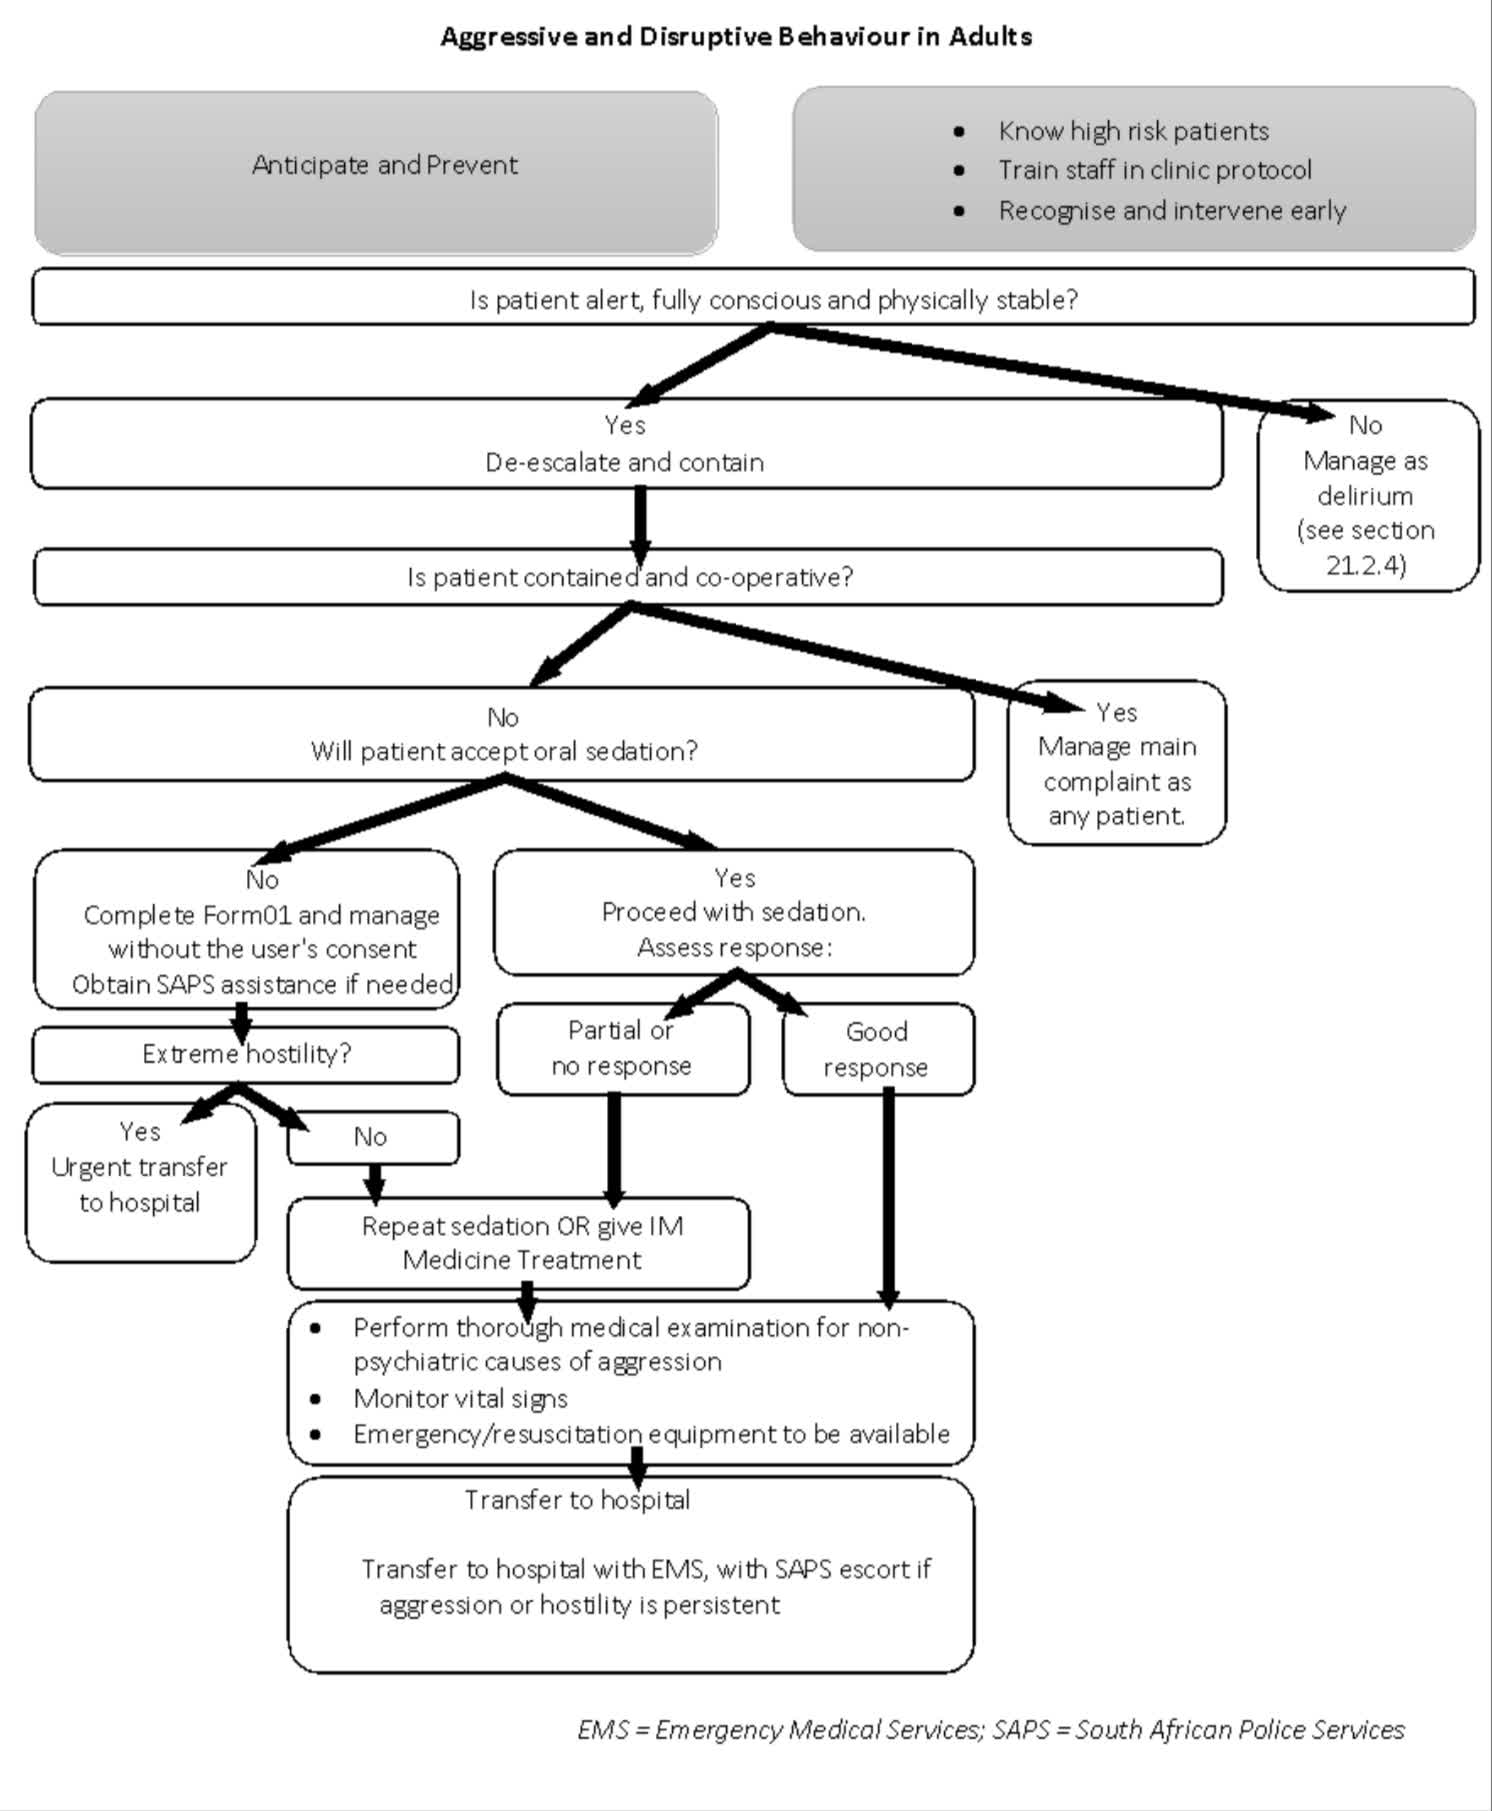
Medicine Treatment
Oral treatment:
- Benzodiazepines, e.g.: (Doctor prescribed)
- Diazepam, oral, 5 mg immediately.
OR
- Midazolam, buccal, 7.5–15 mg, immediately, using the parenteral formulation
If response to oral benzodiazepine (after 30–60 minutes) is inadequate, or oral treatment refused, administer parenteral or orodispersible olanzapine:
- Olanzapine, orodispersible tablet or IM, 5–10 mg immediately (Doctor prescribed)
- Repeat after 30–60 minutes if needed.
Note:
- Use lower doses of olanzapine (2.5–5mg) in elderly, frail, or medically unwell patients.
- Repeated doses may result in excessive sedation.
If previous intolerability to olanzapine (e.g., previous neuro-malignant syndrome), administer parenteral benzodiazepine:
- Short-acting benzodiazepines, e.g.: (Doctor prescribed)
- Midazolam, IM, 7.5–15 mg immediately.
- Repeat after 30–60 minutes if needed.
Note:
- To avoid inappropriate repeat dosing allow at least 30 minutes for the medication to take effect.
- Do not administer IM olanzapine and IM benzodiazepines at the same time.
- Midazolam IM has a rapid onset of action (10–20 minutes) and very short duration of sedation (approximately 1 hour and 20 minutes).
Note:
Long acting injectable antipsychotics e.g., flupenthixol decanoate and zuclopenthixol decanoate have no role in rapid tranquillisation.
CAUTION
- Rapid tranquillisation may cause cardiovascular collapse, respiratory depression, neuroleptic malignant syndrome, and acute dystonic reactions.
- The elderly, children, intellectually disabled and those with comorbid medical conditions and substance users are at highest risk.
- An emergency trolley, airway, bag, oxygen, and intravenous line equipment must be available.
If alcohol use is suspected:
ADD
- Thiamine, oral, 300 mg immediately and daily for 14 days.
Note:
- Always monitor vital signs of sedated patient:
- Vital signs: pulse, respiratory rate, blood pressure, temperature, level of consciousness and hydration.
- Monitor particularly for respiratory depression: if respiratory rate drops to < 12 breaths/minute, call doctor urgently and ventilate with bag-valve mask (1 breath/3-5 seconds) attached to oxygen at 15 L/minute.
Referral
- All cases.
Standard Treatment Guidelines and Essential Medicines List for South Africa Primary Healthcare Level_Chapter 16: Mental Health Conditions_NEMLC Recommendations for Medicine Amendments 2020_2023