Anaemia, Iron Deficiency
Description General Measures Medicine Treatment Referral/Consultation D50.0-1/D50.8-9 DESCRIPTION Anaemia due to iron deficiency. Common causes of iron deficiency are chronic blood loss, poor iron absorption or poor nutritional intake. Investigations Low MCV and low MCH (mean corpuscular hemoglobin <26 pg) – note that these are often normal in early stages. Full blood count (FBC) and periphera
D50.0-1/D50.8-9
DESCRIPTION
Anaemia due to iron deficiency. Common causes of iron deficiency are chronic blood loss, poor iron absorption or poor nutritional intake.
Investigations
- Low MCV and low MCH (mean corpuscular hemoglobin <26 pg) – note that these are often normal in early stages.
- Full blood count (FBC) and peripheral smear: Hypochromic (low MCH) microcytic anaemia, and pencil cells often reported.
- Confirm with low ferritin.
- Investigate for cause of iron deficiency.
- Consider upper and lower gastrointestinal endoscopies in high risk patients (all males and postmenopausal female patients) and patients not responding to treatment.
GENERAL MEASURES
- Identify and treat the underlying cause.
- Dietary adjustment if this is the underlying cause.
MEDICINE TREATMENT
Iron supplementation for treatment:
Oral iron preparation
- Ferrous sulfate compound BPC (dried), oral, 170 mg (± 55 mg elemental iron) 12 hourly.
OR
LoE:IIIbi
- Ferrous fumarate, oral, 200 mg (± 65 mg elemental iron) 12 hourly.
- Do not ingest with tea, antacids or calcium supplements/milk.
- Doses should be taken on an empty stomach, but if gastrointestinal side effects occur, doses may be taken with meals.
- Continue with treatment for 3 months once Hb has normalised to replace iron stores.
- If daily iron is poorly tolerated (e.g. epigastric pain, nausea, vomiting and constipation), administer oral iron on alternate days with meals.
LoE:IIIbii
Monitor patient response after one month of treatment: Hb should rise by at least 2 g/dL in the adherent patient without ongoing blood loss.
Consider the following if there is failure to respond to iron therapy:
- non-adherence,
- continued blood loss,
- alternate diagnosis,
- malabsorption, or
- mixed deficiency; concurrent folate or vitamin B12 deficiency.
Consult a specialist for further workup and/or intravenous iron supplementation if patient is not responding to oral iron supplementation despite adherence and no ongoing losses.
Parenteral iron preparation
Parenteral iron is seldomly required and may very rarely be associated with anaphylaxis. Hypotensive episodes may occur if the injection is administered too rapidly.
LoE:IVbiii
Parenteral iron is only indicated in the following scenarios:
- oral iron is ineffective (defined as lack of response after three months of oral iron therapy);
- oral iron is not tolerated.
- oral iron is not expected to be effective, e.g. malabsorption, patients on haemodialysis and erythropoietin therapy; or
- iron deficiency anaemia from 36 weeks of pregnancy;
In people who require repeated therapy, the intravenous route is preferred.
Note:
Use in consultation with a specialist.
The total iron dose to be administered is determined by haemoglobin and body weight (advisable to also reference product information):
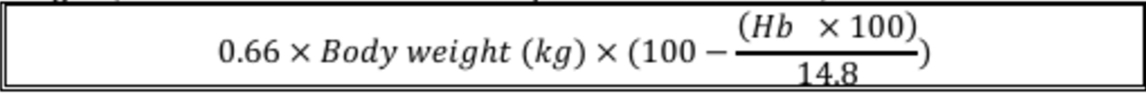
- Iron, IV, e.g.:
- Iron sucrose, slow IV infusion, 200 mg in 200 mL sodium chloride 0.9%, over 30 minutes.
- This preparation can be administered to a maximum frequency of 3 times a week until the total calculated iron dose has been given.
- Test dose is not required, however, caution is advised with every dose of IV iron, even if previously well tolerated.
- An initial total dose of 600 mg (administered in three divided doses) is usually adequate to raise the Hb to acceptable levels.
LoE:IVbiv
OR
- Low molecular weight iron dextran, slow IV infusion,
100–200 mg, diluted in 100 mL 0.9% sodium chloride or 5% glucose solution.- Maximum infusion rate: 100 mL over 30 minutes (200 ml per hour).
- Administer 2–3 times per week until calculated total iron requirements have been given.
- If patient requires rapid delivery of iron to replenish iron stores, iron dextran may be administered as a total dose infusion up to a total replacement dose of 20 mg/kg body weight. Dilute dose in 500 mL 0.9% sodium chloride or 5% glucose solution and give over 4–6 hours.
- Test dose is not required, however, caution is needed with every dose of IV iron, even if previously well tolerated.
LoE:IIIbv
Resuscitation equipment should be readily available to manage anaphylaxis.
Red cell concentrate transfusion
Indicated in patients with:
- severe anaemia leading to cardiac failure or severe dyspnoea;
- active, ongoing bleeding; or
- where correction of anaemia is required prior to performing an urgent invasive procedure or surgery.
Iron supplementation for prophylaxis:
O99.0/D50.0-1/D50.8-9/Z29.2
For example during pregnancy:
- Ferrous sulfate compound BPC (dried), oral, 170 mg (± 55 mg elemental iron) daily.
LoE:IIIbvi
OR
- Ferrous fumarate, oral, 200 mg (± 65 mg elemental iron) daily.
Note:
- Do not ingest oral iron with tea, antacids or calcium supplements/milk.
- Doses should be taken on an empty stomach, but if gastrointestinal side effects occur, doses should be taken with meals.
If daily iron is poorly tolerated:
- Features of intolerance: epigastric pain, nausea, vomiting, and/or constipation.
- Oral iron preparations may be prescribed on alternate days. If still poorly tolerated, dosing may be modified and taken once weekly (See table below for dosing).
Table 2.1: Alternative oral iron supplementation dosing regimens
| Iron preparation | Alternate day dosing | Once weekly dosing |
| Ferrous sulphate compound BPC (dried) | 170 mg (±55 mg elemental iron), once on alternate days | 340 mg (±110 mg elemental iron), once weekly |
| Ferrous fumarate | 200 mg (±65 mg elemental iron), once on alternate days | 400 mg (±130 mg elemental iron), once weekly |
LoE:IIbvii
REFERRAL/CONSULTATION
- Ongoing anaemia despite reported adherence and optimal therapy.
Standard Treatment Guidelines And Essential Medicines List For South Africa, Adult Hospital level_Version 1_30 March 2026
Chapter 2: Blood and Blood Forming Organs; 2.1.1 Anaemia, Iron Deficiency