Shock
Description Emergency Treatment Referral ICD-10 code: R57.0-2/R57.8-9/T79.4/T78.2/Y57.9 DESCRIPTION Shock is a life-threatening condition characterised by any evidence of inadequate organ perfusion. Signs and symptoms of shock in adults Low blood pressure (systolic BP < 80 mmHg) is the key sign of shock Weak and rapid pulse Rapid shallow breathing Low urine output Restlessness and altered ment
ICD-10 code: R57.0-2/R57.8-9/T79.4/T78.2/Y57.9
DESCRIPTION
Shock is a life-threatening condition characterised by any evidence of inadequate organ perfusion.
Signs and symptoms of shock in adults
- Low blood pressure (systolic BP < 80 mmHg) is the key sign of shock
- Weak and rapid pulse
- Rapid shallow breathing
- Low urine output
- Restlessness and altered mental state
- Weakness
Signs and symptoms of shock in children
Shock must be recognised while still in the compensated state to avoid irreversible deterioration. Therefore, the following are primarily assessed in children:
- Prolonged capillary filling (> 3 seconds)
- Decreased pulse volume (weak thready pulse)
- Increased heart rate (> 160 beats/minute in infants, > 120 beats/minute in children)
- Decreased level of consciousness (poor eye contact)
- Rapid breathing
- The signs mentioned above are more sensitive in detecting shock before it is irreversible. Decreased blood pressure and decreased urine output are late signs of shock and can be monitored.
Table 21.4: Normal ranges in children:
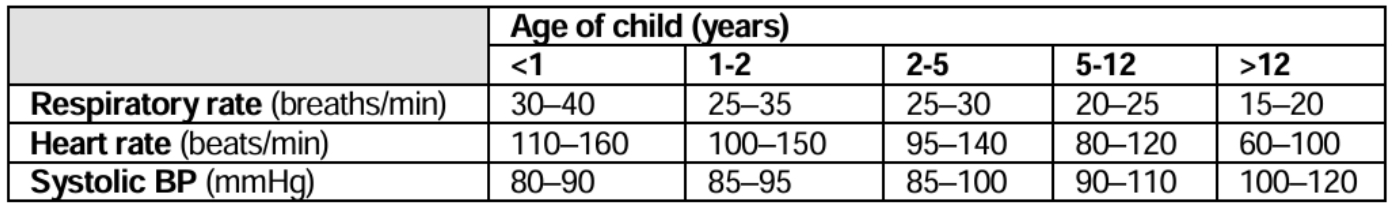 Source: The Hands-on Guide to Practical Paediatrics, First Edition. Rebecca Hewitson and Caroline Fertleman. © 2014 John Wiley & Sons, Ltd. Published 2014 by John Wiley & Sons, Ltd. Companion Website: www.wileyhandsonguides.com/paediatrics
Types of shock:
- Hypovolaemic shock: Most common type of shock. Primary cause is loss of fluid from circulation due to haemorrhage, burns, diarrhoea, etc.
- Cardiogenic shock: Caused by the failure of the heart to pump effectively e.g. in myocardial infarction, cardiac failure, etc.
- Septic shock: Caused by an overwhelming infection, leading to vasodilation.
- Anaphylactic shock: Caused by severe allergic reaction to an allergen, or medicine.
EMERGENCY TREATMENT
- Maintain open airway.
- Administer face mask oxygen, if saturation < 94%.
- Consider the need for intubation and seek advice from referral centre.
- Check for and manage hypoglycaemia
- If anaphylactic shock suspected, See: Anaphylaxis.
Intravenous fluid therapy is important in the treatment of all types of shock, except for cardiogenic shock and septic shock (as fluid-overloaded patients do not need fluid replacement) – these patients should receive a fluid challenge as detailed below. Prompt diagnosis of the underlying cause is essential to ensure optimal treatment.
Fluid replacement (avoid in cardiogenic and septic shock):
Adults
- Sodium chloride 0.9%, IV, 1 L as a rapid bolus.
- Repeat bolus until haemodynamic status is improved.
- Once stable, maintain IV fluids with careful monitoring of haemodynamic status; adjust infusion rate as needed to maintain stability pending transfer.
Children
- Sodium chloride 0.9% or ringers lactate, IV, 10 mL/kg as over 20 minutes.
- Repeat bolus until haemodynamic status is improved.
- Once stable, maintain IV fluids with careful monitoring of haemodynamic status; adjust infusion rate as needed to maintain stability pending transfer.
Note:
If patient develops respiratory distress, recheck airway and breathing and discontinue fluids.
In adults with suspected cardiogenic or septic shock: give a fluid challenge:
- Sodium chloride 0.9%, IV, 500 mL over 30 minutes.
- Assess blood pressure and pulse rate response. Response is defined by improvements in blood pressure, pulse rate and mental status (adequate cerebral perfusion) in addition to a good urine output, rather than an absolute blood pressure value.
- If response is positive, then continue with intravenous fluid. Monitor the patient and stop fluids if patient is breathless. Avoid over hydrating as this could exacerbate hypoxia associated with adult respiratory distress syndrome.
- If no adequate response to fluid challenge (as described above), suspect septic shock and repeat fluid challenge.
Septicaemia in children:
All children with shock, which is not obviously due to trauma or simple watery diarrhoea, should in addition to fluid resuscitation, receive antibiotic cover for probable septicaemia.
- Ceftriaxone, IM, 80 mg/kg/dose immediately as a single dose. See: dosing table.
- Do not inject more than 1 g at one injection site.
CAUTION: USE OF CEFTRIAXONE IN NEONATES AND CHILDREN
- If SUSPECTING SERIOUS BACTERIAL INFECTION in neonate, give ceftriaxone, even if jaundiced.
- Avoid giving calcium-containing IV fluids (e.g. Ringer Lactate) together with ceftriaxone:
- If ≤ 28 days old, avoid calcium-containing IV fluids for 48 hours after ceftriaxone administered.
- If > 28 days old, ceftriaxone and calcium-containing IV fluids may be given sequentially provided the giving set is flushed thoroughly with sodium chloride 0.9% before and after.
- Preferably administer IV fluids without calcium contents.
- Always include the dose and route of administration of ceftriaxone in the referral letter.
REFERRAL
Urgent
- All patients, after resuscitation.
Click here for the NEMLC Recommendations for medicine amendments (2020-4 review cycle).
Standard Treatment Guidelines and Essential Medicines List for South Africa, Primary Healthcare, 2020-4_Version 1.1_October 2024
Chapter 21: Emergencies and Injuries